WARNING - FDA records indicate that this drug has been recalled.
Atorvastatin Calcium label

Atorvastatin Calcium

Atorvastatin Calcium Recall

Get an alert when a recall is issued.

Shire Human Genetic Therapies, Inc.
Product Description: VPRIV (velaglucerase alfa for injection) , Lyophilized Powder, 400 Units/vial, Rx Only. Shire Human Genetic Therapies, Inc. 300 Shire Way, Lexington, MA 02421. NDC: 54092-701-04.
Status: Ongoing
City: Lexington
State: MA
Country: US
Voluntary/Mandated: Voluntary: Firm Initiated
Initial Firm Notification: Letter
Distribution Pattern: US Nationwide including Puerto Rico; Mexico, Columbia
Classification: Class I
Product Quantity: 8359 vials
Reason For Recall: Presence of Particulate Matter; Particulates identified as stainless steel and barium sulfate.
Recall Initiation Date: 20140314
Report Date: 20140430

Side Effects & Adverse Reactions

There is currently no warning information available for this product. We apologize for any inconvenience.

FDA Safety Alerts

There are currently no FDA safety alerts available for this drug.

Manufacturer Warnings

There is currently no manufacturer warning information available for this drug.

FDA Labeling Changes

There are currently no FDA labeling changes available for this drug.

Uses

Therapy with lipid-altering agents should be only one component of multiple risk factor intervention in individuals at significantly increased risk for atherosclerotic vascular disease due to hypercholesterolemia. Drug therapy is recommended as an adjunct to diet when the response to a diet restricted in saturated fat and cholesterol and other nonpharmacologic measures alone has been inadequate. In patients with CHD or multiple risk factors for CHD, atorvastatin calcium tablets can be started simultaneously with diet.

In adult patients without clinically evident coronary heart disease, but with multiple risk factors for coronary heart disease such as age, smoking, hypertension, low HDL-C, or a family history of early coronary heart disease, atorvastatin calcium tablets are indicated to: 

  • Reduce the risk of myocardial infarction    
  • Reduce the risk of stroke    
  • Reduce the risk for revascularization procedures and angina

In patients with type 2 diabetes, and without clinically evident coronary heart disease, but with multiple risk factors for coronary heart disease such as retinopathy, albuminuria, smoking, or hypertension, atorvastatin calcium tablets are indicated to:

  • Reduce the risk of myocardial infarction    
  • Reduce the risk of stroke

In patients with clinically evident coronary heart disease, atorvastatin calcium tablets are indicated to:

  • Reduce the risk of non-fatal myocardial infarction    
  • Reduce the risk of fatal and non-fatal stroke    
  • Reduce the risk for revascularization procedures    
  • Reduce the risk of hospitalization for CHF    
  • Reduce the risk of angina

Atorvastatin calcium tablets are indicated:

  • As an adjunct to diet to reduce elevated total-C, LDL-C, apo B, and TG levels and to increase HDL-C in patients with primary hypercholesterolemia (heterozygous familial and nonfamilial) and mixed dyslipidemia (Fredrickson Types IIa and IIb);
  • As an adjunct to diet for the treatment of patients with elevated serum TG levels (Fredrickson Type IV);
  • For the treatment of patients with primary dysbetalipoproteinemia (Fredrickson Type III) who do not respond adequately to diet;
  • To reduce total-C and LDL-C in patients with homozygous familial hypercholesterolemia as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) or if such treatments are unavailable;
  • As an adjunct to diet to reduce total-C, LDL-C, and apo B levels in boys and postmenarchal girls, 10 to 17 years of age, with heterozygous familial hypercholesterolemia if after an adequate trial of diet therapy the following findings are present:             

a. LDL-C remains ≥ 190 mg/dL or            

b. LDL-C remains ≥ 160 mg/dL and:

  • there is a positive family history of premature cardiovascular disease or
  • two or more other CVD risk factors are present in the pediatric patient  

Atorvastatin calcium tablets have not been studied in conditions where the major lipoprotein abnormality is elevation of chylomicrons (Fredrickson Types I and V).

History

There is currently no drug history available for this drug.

Other Information

Atorvastatin calcium is a synthetic lipid-lowering agent. Atorvastatin is an inhibitor of 3-hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase. This enzyme catalyzes the conversion of HMG-CoA to mevalonate, an early and rate-limiting step in cholesterol biosynthesis.

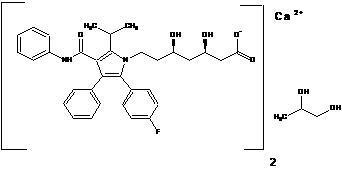
Atorvastatin calcium is [R-(R*, R*)]-2-(4-fluorophenyl)-ß, δ-dihydroxy-5-(1-methylethyl)-3-phenyl-4-[(phenylamino) carbonyl]-1H-pyrrole-1-heptanoic acid, calcium salt (2:1). The molecular formula of atorvastatin calcium is C66H68CaF2N4O10and its molecular weight is 1155.36.  Its structural formula is:

MM1

Atorvastatin calcium is a white to off-white colored powder free from visible extraneous matter. Atorvastatin calcium is soluble in dimethyl sulphoxide, slightly soluble in alcohol, very slightly soluble in water, in pH 7.4 phosphate buffer and in acetonitrile and practically insoluble in aqueous solutions of pH 4 and below.

Atorvastatin calcium tablets for oral administration contain 10, 20 and 40 mg atorvastatin and the following inactive ingredients: Basic butylated methacrylate copolymer, crospovidone, hydroxy propyl cellulose, lactose monohydrate, magnesium stearate, methanol, microcrystalline cellulose, sodium bicarbonate and sodium lauryl sulphate. The tablet coating contains isopropyl alcohol, methylene chloride and coloring agent opadry OY-58900 white contains polyethylene glycol, titanium dioxide and hypromellose.

Atorvastatin Calcium Manufacturers

  • Remedyrepack Inc.
    Atorvastatin Calcium | Remedyrepack Inc.
    No Recall

    Atorvastatin Calcium | Remedyrepack Inc.

    Atorvastatin Calcium | Remedyrepack Inc.


    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.


    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.


    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.


    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].


    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


  • Remedyrepack Inc.
    Atorvastatin Calcium | Remedyrepack Inc.
    No Recall

    Atorvastatin Calcium | Remedyrepack Inc.

    Atorvastatin Calcium | Remedyrepack Inc.


    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.


    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.


    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.


    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].


    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


  • Atorvastatin Calcium | Cardinal Health
    No Recall

    Atorvastatin Calcium | Cardinal Health

    Atorvastatin Calcium | Cardinal Health
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 mg to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 Years of Age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 mg to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients with Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Remedyrepack Inc.
    Atorvastatin Calcium | Remedyrepack Inc.
    No Recall

    Atorvastatin Calcium | Remedyrepack Inc.

    Atorvastatin Calcium | Remedyrepack Inc.


    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.


    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.


    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.


    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].


    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


  • Atorvastatin Calcium | Clinical Solutions Wholsesale
    No Recall

    Atorvastatin Calcium | Clinical Solutions Wholsesale

    Atorvastatin Calcium | Clinical Solutions Wholsesale

    For symptomatic relief of anxiety and tension associated with psychoneurosis and as an adjunct in organic disease states in which anxiety is manifested: in adults, 50 mg to 100 mg q.i.d.; children under 6 years, 50 mg daily in divided doses; and over 6 years, 50 mg to 100 mg daily in divided doses.

    For use in the management of pruritus due to allergic conditions such as chronic urticaria and atopic and contact dermatoses and in histamine-mediated pruritus: in adults: 25 mg t.i.d. or q.i.d.; children under 6 years, 50 mg daily in divided doses; and over 6 years, 50 mg to 100 mg daily in divided doses.

    As a sedative when used as a premedication and following general anesthesia: 50 mg to 100 mg in adults and 0.6 mg/kg in children. When treatment is initiated by the intramuscular route of administration, subsequent doses may be administered orally.

    As with all medications, the dosage should be adjusted according to the patient’s response to therapy.

  • Remedyrepack Inc.
    Atorvastatin Calcium | Remedyrepack Inc.
    No Recall

    Atorvastatin Calcium | Remedyrepack Inc.

    Atorvastatin Calcium | Remedyrepack Inc.


    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.


    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.


    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.


    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].


    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


  • Preferred Pharmaceuticals, Inc.
    Atorvastatin Calcium | Preferred Pharmaceuticals, Inc.
    No Recall

    Atorvastatin Calcium | Preferred Pharmaceuticals, Inc.

    Atorvastatin Calcium | Preferred Pharmaceuticals, Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10-17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients with Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • State Of Florida Doh Central Pharmacy
    Atorvastatin Calcium | Remedyrepack Inc.
    No Recall

    Atorvastatin Calcium | Remedyrepack Inc.

    Atorvastatin Calcium | Remedyrepack Inc.

    Promethazine Hydrochloride Tablets, USP are contraindicated for children under 2 years of age (see WARNINGS: Black Box Warning and Use in Pediatric Patients).

    Allergy: The average oral dose is 25 mg taken before retiring; however, 12.5 mg may be taken before meals and on retiring, if necessary. Single 25 mg doses at bedtime or 6.25 to 12.5 mg taken three times daily will usually suffice. After initiation of treatment, in children or adults, dosage should be adjusted to the smallest amount adequate to relieve symptoms. The administration of promethazine HCl in 25 mg doses will control minor transfusion reactions of an allergic nature.

    Motion Sickness: The average adult dose is 25 mg taken twice daily. The initial dose should be taken one-half to one hour before anticipated travel and be repeated eight to twelve hours later if necessary. On succeeding days of travel, it is recommended that 25 mg be given on arising and again before the evening meal. For children, promethazine hydrochloride tablets, syrup, or rectal suppositories, 12.5 to 25 mg, twice daily, may be administered.

    Nausea and Vomiting: Antiemetics should not be used in vomiting of unknown etiology in children and adolescents (see WARNINGS: Use in Pediatric Patients).

    The average effective dose of promethazine HCl for the active therapy of nausea and vomiting in children or adults is 25 mg. When oral medication cannot be tolerated, the dose should be given parenterally or by rectal suppository. 12.5 to 25 mg doses may be repeated, as necessary, at four- to six-hour intervals.

    For nausea and vomiting in children, the usual dose is 0.5 mg per pound of body weight, and the dose should be adjusted to the age and weight of the patient and the severity of the condition being treated.

    For prophylaxis of nausea and vomiting, as during surgery and the postoperative period, the average dose is 25 mg repeated at four- to six-hour intervals, as necessary.

    Sedation: This product relieves apprehension and induces a quiet sleep from which the patient can be easily aroused. Administration of 12.5 to 25 mg Promethazine HCl by the oral route or by rectal suppository at bedtime will provide sedation in children. Adults usually require 25 to 50 mg for nighttime, presurgical, or obstetrical sedation.

    Pre- and Postoperative Use: Promethazine HCl in 12.5 to 25 mg doses for children and 50 mg doses for adults the night before surgery relieves apprehension and produces a quiet sleep.

    For preoperative medication, children require doses of 0.5 mg per pound of body weight in combination with an appropriately reduced dose of narcotic or barbiturate and the appropriate dose of an atropine-like drug. Usual adult dosage is 50 mg Promethazine HCl with an appropriately reduced dose of narcotic or barbiturate and the required amount of a belladonna alkaloid.

    Postoperative sedation and adjunctive use with analgesics may be obtained by the administration of 12.5 to 25 mg in children and 25 to 50 mg doses in adults. Promethazine hydrochloride tablets are contraindicated for children under 2 years of age.


  • Major Pharmaceuticals
    Atorvastatin Calcium | Major Pharmaceuticals
    No Recall

    Atorvastatin Calcium | Major Pharmaceuticals

    Atorvastatin Calcium | Major Pharmaceuticals
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Northwind Pharmaceuticals, Llc
    Atorvastatin Calcium | Northwind Pharmaceuticals, Llc
    No Recall

    Atorvastatin Calcium | Northwind Pharmaceuticals, Llc

    Atorvastatin Calcium | Northwind Pharmaceuticals, Llc

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10-17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Rebel Distributors Corp
    No Recall

    Atorvastatin Calcium | Rebel Distributors Corp

    Atorvastatin Calcium | Rebel Distributors Corp
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or a Combination of Ritonavir plus Saquinavir or Lopinavir plus Ritonavir

    In patients taking cyclosporine, therapy should be limited to atorvastatin calcium tablets 10 mg once daily. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of ritonavir plus saquinavir or lopinavir plus ritonavir, for doses of atorvastatin calcium tablets exceeding 20 mg, appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Dispensing Solutions, Inc.
    Atorvastatin Calcium | Dispensing Solutions, Inc.
    No Recall

    Atorvastatin Calcium | Dispensing Solutions, Inc.

    Atorvastatin Calcium | Dispensing Solutions, Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or a Combination of Ritonavir plus Saquinavir or Lopinavir plus Ritonavir

    In patients taking cyclosporine, therapy should be limited to atorvastatin calcium tablets 10 mg once daily. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of ritonavir plus saquinavir or lopinavir plus ritonavir, for doses of atorvastatin calcium tablets exceeding 20 mg, appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Pd-rx Pharmaceuticals, Inc.
    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.
    No Recall

    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.

    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology(12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Watson Laboratories, Inc.
    Atorvastatin Calcium | Watson Laboratories, Inc.
    No Recall

    Atorvastatin Calcium | Watson Laboratories, Inc.

    Atorvastatin Calcium | Watson Laboratories, Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Legacy Pharmaceutical Packaging
    Atorvastatin Calcium | Legacy Pharmaceutical Packaging
    No Recall

    Atorvastatin Calcium | Legacy Pharmaceutical Packaging

    Atorvastatin Calcium | Legacy Pharmaceutical Packaging
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Rebel Distributors Corp
    No Recall

    Atorvastatin Calcium | Rebel Distributors Corp

    Atorvastatin Calcium | Rebel Distributors Corp
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or a Combination of Ritonavir plus Saquinavir or Lopinavir plus Ritonavir

    In patients taking cyclosporine, therapy should be limited to atorvastatin calcium tablets 10 mg once daily. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of ritonavir plus saquinavir or lopinavir plus ritonavir, for doses of atorvastatin calcium tablets exceeding 20 mg, appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Rebel Distributors Corp
    No Recall

    Atorvastatin Calcium | Rebel Distributors Corp

    Atorvastatin Calcium | Rebel Distributors Corp
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Rebel Distributors Corp
    No Recall

    Atorvastatin Calcium | Rebel Distributors Corp

    Atorvastatin Calcium | Rebel Distributors Corp
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Ranbaxy Pharmaceuticals Inc.
    No Recall

    Atorvastatin Calcium | Ranbaxy Pharmaceuticals Inc.

    Atorvastatin Calcium | Ranbaxy Pharmaceuticals Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology(12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Dr. Reddy’s Laboratories Limited
    Atorvastatin Calcium | Dr. Reddy's Laboratories Limited
    No Recall

    Atorvastatin Calcium | Dr. Reddy's Laboratories Limited

    Atorvastatin Calcium | Dr. Reddy's Laboratories Limited

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients with Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Mylan Institutional Inc.
    Atorvastatin Calcium | Mylan Institutional Inc.
    No Recall

    Atorvastatin Calcium | Mylan Institutional Inc.

    Atorvastatin Calcium | Mylan Institutional Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 mg to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 Years of Age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12) and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 mg to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients with Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Unit Dose Services
    No Recall

    Atorvastatin Calcium | Unit Dose Services

    Atorvastatin Calcium | Unit Dose Services

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia ( Types IIa and IIb)  Fredrickson

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current ). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.    NCEP Guidelines

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current , , and ]. Adjustments should be made at intervals of 4 weeks or more. NCEP Pediatric Panel GuidelinesClinical Pharmacology (12)Indications and Usage (1.2)

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see , ]. Warnings and Precautions, Skeletal Muscle (5.1)Drug Interactions (7)

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see , ]. Warnings and Precautions, Skeletal Muscle (5.1)Clinical Pharmacology, Pharmacokinetics (12.3)

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see , ]. Warnings and Precautions,Skeletal Muscle (5.1)Drug Interactions (7)

  • Atorvastatin Calcium | Unit Dose Services
    No Recall

    Atorvastatin Calcium | Unit Dose Services

    Atorvastatin Calcium | Unit Dose Services

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia ( Types IIa and IIb)  Fredrickson

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current ). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.    NCEP Guidelines

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current , , and ]. Adjustments should be made at intervals of 4 weeks or more. NCEP Pediatric Panel GuidelinesClinical Pharmacology (12)Indications and Usage (1.2)

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see , ]. Warnings and Precautions, Skeletal Muscle (5.1)Drug Interactions (7)

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see , ]. Warnings and Precautions, Skeletal Muscle (5.1)Clinical Pharmacology, Pharmacokinetics (12.3)

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see , ]. Warnings and Precautions,Skeletal Muscle (5.1)Drug Interactions (7)

  • Atorvastatin Calcium | Unit Dose Services
    No Recall

    Atorvastatin Calcium | Unit Dose Services

    Atorvastatin Calcium | Unit Dose Services

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia ( Types IIa and IIb)  Fredrickson

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current ). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.    NCEP Guidelines

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current , , and ]. Adjustments should be made at intervals of 4 weeks or more. NCEP Pediatric Panel GuidelinesClinical Pharmacology (12)Indications and Usage (1.2)

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see , ]. Warnings and Precautions, Skeletal Muscle (5.1)Drug Interactions (7)

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see , ]. Warnings and Precautions, Skeletal Muscle (5.1)Clinical Pharmacology, Pharmacokinetics (12.3)

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see , ]. Warnings and Precautions,Skeletal Muscle (5.1)Drug Interactions (7)

  • Atorvastatin Calcium | Unit Dose Services
    No Recall

    Atorvastatin Calcium | Unit Dose Services

    Atorvastatin Calcium | Unit Dose Services

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia ( Types IIa and IIb)  Fredrickson

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current ). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.    NCEP Guidelines

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current , , and ]. Adjustments should be made at intervals of 4 weeks or more. NCEP Pediatric Panel GuidelinesClinical Pharmacology (12)Indications and Usage (1.2)

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see , ]. Warnings and Precautions, Skeletal Muscle (5.1)Drug Interactions (7)

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see , ]. Warnings and Precautions, Skeletal Muscle (5.1)Clinical Pharmacology, Pharmacokinetics (12.3)

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see , ]. Warnings and Precautions,Skeletal Muscle (5.1)Drug Interactions (7)

  • Dispensing Solutions, Inc.
    Atorvastatin Calcium | Dispensing Solutions, Inc.
    No Recall

    Atorvastatin Calcium | Dispensing Solutions, Inc.

    Atorvastatin Calcium | Dispensing Solutions, Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or a Combination of Ritonavir plus Saquinavir or Lopinavir plus Ritonavir

    In patients taking cyclosporine, therapy should be limited to atorvastatin calcium tablets 10 mg once daily. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of ritonavir plus saquinavir or lopinavir plus ritonavir, for doses of atorvastatin calcium tablets exceeding 20 mg, appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Legacy Pharmaceutical Packaging
    Atorvastatin Calcium | Legacy Pharmaceutical Packaging
    No Recall

    Atorvastatin Calcium | Legacy Pharmaceutical Packaging

    Atorvastatin Calcium | Legacy Pharmaceutical Packaging
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Bryant Ranch Prepack
    Atorvastatin Calcium | Bryant Ranch Prepack
    No Recall

    Atorvastatin Calcium | Bryant Ranch Prepack

    Atorvastatin Calcium | Bryant Ranch Prepack

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Bryant Ranch Prepack
    Atorvastatin Calcium | Bryant Ranch Prepack
    No Recall

    Atorvastatin Calcium | Bryant Ranch Prepack

    Atorvastatin Calcium | Bryant Ranch Prepack

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Bryant Ranch Prepack
    Atorvastatin Calcium | Bryant Ranch Prepack
    No Recall

    Atorvastatin Calcium | Bryant Ranch Prepack

    Atorvastatin Calcium | Bryant Ranch Prepack

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Bryant Ranch Prepack
    Atorvastatin Calcium | Bryant Ranch Prepack
    No Recall

    Atorvastatin Calcium | Bryant Ranch Prepack

    Atorvastatin Calcium | Bryant Ranch Prepack
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology(12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Bryant Ranch Prepack
    Atorvastatin Calcium | Bryant Ranch Prepack
    No Recall

    Atorvastatin Calcium | Bryant Ranch Prepack

    Atorvastatin Calcium | Bryant Ranch Prepack
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Kremers Urban Pharmaceuticals Inc.
    Atorvastatin Calcium | Kremers Urban Pharmaceuticals Inc.
    No Recall

    Atorvastatin Calcium | Kremers Urban Pharmaceuticals Inc.

    Atorvastatin Calcium | Kremers Urban Pharmaceuticals Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10-17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Legacy Pharmaceutical Packaging
    Atorvastatin Calcium | Frontier Medical Equipment, Inc.
    No Recall

    Atorvastatin Calcium | Frontier Medical Equipment, Inc.

    Atorvastatin Calcium | Frontier Medical Equipment, Inc.

    There is currently no dosage information available for this product. We apologize for any inconvenience.

  • Pd-rx Pharmaceuticals, Inc.
    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.
    No Recall

    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.

    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Apotex Corp.
    No Recall

    Atorvastatin Calcium | Apotex Corp.

    Atorvastatin Calcium | Apotex Corp.

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | American Health Packaging
    No Recall

    Atorvastatin Calcium | American Health Packaging

    Atorvastatin Calcium | American Health Packaging
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Physicians Total Care, Inc.
    No Recall

    Atorvastatin Calcium | Physicians Total Care, Inc.

    Atorvastatin Calcium | Physicians Total Care, Inc.
    2.1 Dosing Information

    The recommended dose of sumatriptan tablets is 25 mg, 50 mg, or 100 mg. Doses of 50 mg and 100 mg may provide a greater effect than the 25 mg dose, but doses of 100 mg may not provide a greater effect than the 50 mg dose. Higher doses may have a greater risk of adverse reactions [see Clinical Studies (14)].

    If the migraine has not resolved by 2 hours after taking sumatriptan tablets, or returns after a transient improvement, a second dose may be administered at least 2 hours after the first dose. The maximum daily dose is 200 mg in a 24-hour period.

    Use after sumatriptan injection: If the migraine returns following an initial treatment with sumatriptan succinate injection, additional single sumatriptan tablets (up to 100 mg/day) may be given with an interval of at least 2 hours between tablet doses.

    The safety of treating an average of more than 4 headaches in a 30-day period has not been established.

    2.2 Dosing in Patients With Hepatic Impairment

    If treatment is deemed advisable in the presence of mild to moderate hepatic impairment, the maximum single dose should not exceed 50 mg [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3)].

  • Avkare, Inc.
    Atorvastatin Calcium | Avkare, Inc.
    No Recall

    Atorvastatin Calcium | Avkare, Inc.

    Atorvastatin Calcium | Avkare, Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10-17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Lake Erie Medical Dba Quality Care Products Llc
    Atorvastatin Calcium | Lake Erie Medical Dba Quality Care Products Llc
    No Recall

    Atorvastatin Calcium | Lake Erie Medical Dba Quality Care Products Llc

    Atorvastatin Calcium | Lake Erie Medical Dba Quality Care Products Llc
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of _RefINDICATIONS_AND_USAGEatorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Medvantx, Inc.
    Atorvastatin Calcium | Medvantx, Inc.
    No Recall

    Atorvastatin Calcium | Medvantx, Inc.

    Atorvastatin Calcium | Medvantx, Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of _RefINDICATIONS_AND_USAGEatorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Remedyrepack Inc.
    Atorvastatin Calcium | Remedyrepack Inc.
    No Recall

    Atorvastatin Calcium | Remedyrepack Inc.

    Atorvastatin Calcium | Remedyrepack Inc.


    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   


    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.


    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.


    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].


    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


  • Dr. Reddy’s Laboratories Limited
    Atorvastatin Calcium | Celgene Corporation
    No Recall

    Atorvastatin Calcium | Celgene Corporation

    Atorvastatin Calcium | Celgene Corporation

    THALOMID® (THALIDOMIDE) MUST ONLY BE ADMINISTERED IN COMPLIANCE WITH ALL OF THE TERMS OUTLINED IN THE THALOMID REMS PROGRAM. THALOMID® (THALIDOMIDE) MAY ONLY BE PRESCRIBED BY PRESCRIBERS CERTIFIED WITH THE THALOMID REMS PROGRAM AND MAY ONLY BE DISPENSED BY PHARMACISTS CERTIFIED WITH THE THALOMID REMS PROGRAM.

    Drug prescribing to females of reproductive potential should be contingent upon initial and continued confirmed negative results of pregnancy testing.

    Consider dose reduction, delay, or discontinuation in patients who develop NCI CTC (National Cancer Institute Common Toxicity Criteria) Grade 3 or 4 adverse reactions and/or based on clinical judgment.

    2.1 Multiple Myeloma

    THALOMID is administered in combination with dexamethasone in 28-day treatment cycles. The dose of THALOMID is 200 mg administered orally once daily with water, preferably at bedtime and at least 1 hour after the evening meal. The dose of dexamethasone is 40 mg daily administered orally on days 1-4, 9-12, and 17-20 every 28 days.

    Patients who develop adverse reactions such as constipation, somnolence, or peripheral neuropathy may benefit by either temporarily discontinuing the drug or continuing at a lower dose. With the abatement of these adverse reactions, the drug may be started at a lower dose or at the previous dose based on clinical judgment.

    2.2 Erythema Nodosum Leprosum

    For an episode of cutaneous ENL, THALOMID dosing should be initiated at 100 to 300 mg/day, administered once daily with water, preferably at bedtime and at least 1 hour after the evening meal. Patients weighing less than 50 kilograms should be started at the low end of the dose range.

    In patients with a severe cutaneous ENL reaction, or in those who have previously required higher doses to control the reaction, THALOMID dosing may be initiated at higher doses up to 400 mg/day once daily at bedtime or in divided doses with water, at least 1 hour after meals.

    In patients with moderate to severe neuritis associated with a severe ENL reaction, corticosteroids may be started concomitantly with THALOMID. Steroid usage can be tapered and discontinued when the neuritis has ameliorated.

    Dosing with THALOMID should usually continue until signs and symptoms of active reaction have subsided, usually a period of at least 2 weeks. Patients may then be tapered off medication in 50 mg decrements every 2 to 4 weeks.

    Patients who have a documented history of requiring prolonged maintenance treatment to prevent the recurrence of cutaneous ENL or who flare during tapering should be maintained on the minimum dose necessary to control the reaction. Tapering off medication should be attempted every 3 to 6 months, in decrements of 50 mg every 2 to 4 weeks.

  • Preferred Pharmaceuticals, Inc.
    Atorvastatin Calcium | Preferred Pharmaceuticals, Inc.
    No Recall

    Atorvastatin Calcium | Preferred Pharmaceuticals, Inc.

    Atorvastatin Calcium | Preferred Pharmaceuticals, Inc.


    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Remedyrepack Inc.
    Atorvastatin Calcium | Remedyrepack Inc.
    No Recall

    Atorvastatin Calcium | Remedyrepack Inc.

    Atorvastatin Calcium | Remedyrepack Inc.


    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   


    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.


    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.


    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].


    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


  • Pd-rx Pharmaceuticals, Inc.
    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.
    No Recall

    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.

    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets are 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets are 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Kaiser Foundation Hospitals
    No Recall

    Atorvastatin Calcium | Kaiser Foundation Hospitals

    Atorvastatin Calcium | Kaiser Foundation Hospitals
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12) , and Indications and Usage (1.2) ]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7) ].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3) ].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7) ].

  • Pd-rx Pharmaceuticals, Inc.
    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.
    No Recall

    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.

    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10-17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Major Pharmaceuticals
    Atorvastatin Calcium | Major Pharmaceuticals
    No Recall

    Atorvastatin Calcium | Major Pharmaceuticals

    Atorvastatin Calcium | Major Pharmaceuticals
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)]

  • Remedyrepack Inc.
    Atorvastatin Calcium | Remedyrepack Inc.
    No Recall

    Atorvastatin Calcium | Remedyrepack Inc.

    Atorvastatin Calcium | Remedyrepack Inc.


    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.


    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.


    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.


    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].


    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


  • Aidarex Pharmaceuticals Llc
    Atorvastatin Calcium | Aidarex Pharmaceuticals Llc
    No Recall

    Atorvastatin Calcium | Aidarex Pharmaceuticals Llc

    Atorvastatin Calcium | Aidarex Pharmaceuticals Llc
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology(12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • New Horizon Rx Group, Llc
    Atorvastatin Calcium | New Horizon Rx Group, Llc
    No Recall

    Atorvastatin Calcium | New Horizon Rx Group, Llc

    Atorvastatin Calcium | New Horizon Rx Group, Llc

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • St Marys Medical Park Pharmacy
    Atorvastatin Calcium | Mckesson
    No Recall

    Atorvastatin Calcium | Mckesson

    Atorvastatin Calcium | Mckesson
    • if you are under 18 years of age, ask a doctor before use • before using this product, read the enclosed User’s Guide for complete directions and other important information • begin using the gum on your quit day • if you smoke your first cigarette more than 30 minutes after waking up, use Nicotine Polacrilex Gum, 2 mg • if you smoke your first cigarette within 30 minutes of waking up, use Nicotine Polacrilex Gum, 4 mg according to the following 12 week schedule:

    Weeks 1 to 6

    Weeks 7 to 9

    Weeks 10 to 12

    1 piece every

    1 to 2 hours

    1 piece every

    2 to 4 hours

    1 piece every

    4 to 8 hours

    • nicotine gum is a medicine and must be used a certain way to get the best results • chew the gum slowly until it tingles. Then park it between your cheek and gum. When the tingle is gone, begin chewing again, until the tingle returns. • repeat this process until most of the tingle is gone (about 30 minutes) • do not eat or drink for 15 minutes before chewing the nicotine gum, or while chewing a piece • to improve your chances of quitting, use at least 9 pieces per day for the first 6 weeks • if you experience strong or frequent cravings, you may use a second piece within the hour. However, do not continuously use one piece after another since this may cause you hiccups, heartburn, nausea or other side effects. • do not use more than 24 pieces a day • it is important to complete treatment. If you feel you need to use the gum for a longer period to keep from smoking, talk to your health care provider.
  • Atorvastatin Calcium | Quality Choice (chain Drug Marketing Association)
    No Recall

    Atorvastatin Calcium | Quality Choice (chain Drug Marketing Association)

    Atorvastatin Calcium | Quality Choice (chain Drug Marketing Association)
    shake well before using do not take more than 6 doses in any 24-hour period measure only with dosing cup provided keep dosing cup with product mL = milliliter this adult product is not intended for use in children under 12 years of age adults and children 12years and over: 10 mL every 4 hours children under 12 years: do not use
  • Pd-rx Pharmaceuticals, Inc.
    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.
    No Recall

    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.

    Atorvastatin Calcium | Pd-rx Pharmaceuticals, Inc.

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Legacy Pharmaceutical Packaging
    Atorvastatin Calcium | Legacy Pharmaceutical Packaging
    No Recall

    Atorvastatin Calcium | Legacy Pharmaceutical Packaging

    Atorvastatin Calcium | Legacy Pharmaceutical Packaging
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Legacy Pharmaceutical Packaging
    Atorvastatin Calcium | Major Pharmaceuticals
    No Recall

    Atorvastatin Calcium | Major Pharmaceuticals

    Atorvastatin Calcium | Major Pharmaceuticals
    do not give more than directed (see overdose warning) this product does not contain directions or complete warnings for adult use find the right dose on chart below. If possible, use weight to dose; otherwise, use age. chew before swallowing; this product will soften in mouth for ease of chewing repeat dose every 4 hours while symptoms last do not give more than 5 times in 24 hours do not give for more than 5 days unless directed by a doctor

    Weight (lb)

    Age (yr)

    Dose (tablets)*

    Under 48

    Under 6

    Ask a doctor

    48-59

    6-8

    2

    60-71

    9-10

    2 1/2

    72-95

    11

    3

    *or as directed by a doctor

  • Mylan Institutional Inc.
    Atorvastatin Calcium | Mylan Institutional Inc.
    No Recall

    Atorvastatin Calcium | Mylan Institutional Inc.

    Atorvastatin Calcium | Mylan Institutional Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 mg to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 Years of Age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 mg to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients with Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Aidarex Pharmaceuticals Llc
    Atorvastatin Calcium | Aidarex Pharmaceuticals Llc
    No Recall

    Atorvastatin Calcium | Aidarex Pharmaceuticals Llc

    Atorvastatin Calcium | Aidarex Pharmaceuticals Llc
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Mylan Pharmaceuticals Inc.
    Atorvastatin Calcium | Shire Us Manufacturing Inc.
    No Recall

    Atorvastatin Calcium | Shire Us Manufacturing Inc.

    Atorvastatin Calcium | Shire Us Manufacturing Inc.
    2.1 Recommended Starting Dosage in Patients Naïve to Enzyme Replacement Therapy

    VPRIV should be administered under the supervision of a healthcare professional. The recommended starting VPRIV dosage in naïve adults and naïve pediatric patients 4 years of age and older is 60 Units/kg administered every other week as a 60-minute intravenous infusion. The dosage can be adjusted based on achievement and maintenance of each patient's therapeutic goals.

    2.2 Switching from Imiglucerase to VPRIV

    Adults and pediatric patients 4 years of age and older currently being treated on a stable dosage of imiglucerase for type 1 Gaucher disease may be switched to VPRIV by starting treatment with VPRIV at the previous imiglucerase dosage two weeks after the last imiglucerase dose. VPRIV should be administered under the supervision of a healthcare professional as a 60-minute intravenous infusion. The dosage can be adjusted based on achievement and maintenance of each patient's therapeutic goals.

    2.3 Reconstitution of the VPRIV Lyophilized Powder

    VPRIV is a lyophilized powder, which requires reconstitution and dilution, using sterile technique, prior to intravenous infusion. VPRIV should be prepared as follows:

    (a) Determine the number of vials to be reconstituted based on the individual patient's weight and the prescribed dose. (b) Inject 4.3 mL of Sterile Water for Injection, USP into a vial containing VPRIV lyophilized powder. (c) Mix gently. DO NOT SHAKE. The reconstituted VPRIV solution will have a 100 Units/mL concentration (400 Units VPRIV in 4 mL of solution). (d) If additional vials are needed, repeat steps (b) and (c) (e) Visually inspect the reconstituted VPRIV solution in the vials. The solution should be clear to slightly opalescent and colorless. Do not use if the solution is discolored or if foreign particulate matter is present. (f) With a single syringe, withdraw the calculated dose of drug from the appropriate number of vials. Using a separate syringe, withdraw air from a bag of 100 mL of 0.9% sodium chloride solution suitable for intravenous administration. Then dilute the calculated dose of VPRIV directly into the sodium chloride solution. Mix gently. DO NOT SHAKE. Slight flocculation (described as white irregular shaped particles) may occasionally occur. Diluted solution with slight flocculation is acceptable for administration. (g) Because VPRIV contains no preservatives, use the reconstituted VPRIV solution and the diluted VPRIV solution immediately. If immediate use is not possible, the reconstituted VPRIV solution or the diluted VPRIV solution may be stored for up to 24 hours at 2 °C to 8°C (36 °F to 46°F). Do not freeze and protect from light. Complete the infusion within 24 hours of reconstitution of vials. (h) Vials are for single use only. Discard any unused solution. 2.4 Important Administration Instructions

    Administer the diluted VPRIV solution through an in-line low protein-binding 0.2μm filter over 60 minutes. Do not infuse VPRIV with other products in the same infusion tubing because the compatibility of a VPRIV solution with other products has not been evaluated.

    2.5 Premedication to Reduce Risk of Subsequent Hypersensitivity Reactions

    Consider pre-treatment with antihistamines and/or corticosteroids in patients who exhibited symptoms of hypersensitivity associated with prior VPRIV infusions. Appropriate medical support should be readily available when VPRIV is administered [see Warnings and Precautions (5.1)].

  • Northwind Pharmaceuticals
    Atorvastatin Calcium | Northwind Pharmaceuticals
    No Recall

    Atorvastatin Calcium | Northwind Pharmaceuticals

    Atorvastatin Calcium | Northwind Pharmaceuticals

    There is currently no dosage information available for this product. We apologize for any inconvenience.

  • Physicians Total Care, Inc.
    Atorvastatin Calcium | Physicians Total Care, Inc.
    No Recall

    Atorvastatin Calcium | Physicians Total Care, Inc.

    Atorvastatin Calcium | Physicians Total Care, Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology(12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Blenheim Pharmacal, Inc.
    Atorvastatin Calcium | Blenheim Pharmacal, Inc.
    No Recall

    Atorvastatin Calcium | Blenheim Pharmacal, Inc.

    Atorvastatin Calcium | Blenheim Pharmacal, Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Golden State Medical Supply, Inc.
    No Recall

    Atorvastatin Calcium | Golden State Medical Supply, Inc.

    Atorvastatin Calcium | Golden State Medical Supply, Inc.

    Dosage should be adjusted according to the severity of the pain and the response of the patient. However, it should be kept in mind that tolerance to hydrocodone can develop with continued use and that the incidence of untoward effects is dose related.

    The usual adult dosage for Hydrocodone Bitartrate and Acetaminophen Tablets USP is:

    Product Strength Usual Adult Dosage as needed for pain The total 24-hour dosage should not exceed

    5 mg/325 mg

    One to two tablets every four to six hours

    12 tablets

    7.5 mg/325 mg

    One tablet every four to six hours

    8 tablets

  • Northwind Pharmaceuticals
    Atorvastatin Calcium | Northwind Pharmaceuticals
    No Recall

    Atorvastatin Calcium | Northwind Pharmaceuticals

    Atorvastatin Calcium | Northwind Pharmaceuticals

    There is currently no dosage information available for this product. We apologize for any inconvenience.

  • Northwind Pharmaceuticals
    Atorvastatin Calcium | Northwind Pharmaceuticals
    No Recall

    Atorvastatin Calcium | Northwind Pharmaceuticals

    Atorvastatin Calcium | Northwind Pharmaceuticals

    There is currently no dosage information available for this product. We apologize for any inconvenience.

  • Northwind Pharmaceuticals
    Atorvastatin Calcium | Northwind Pharmaceuticals
    No Recall

    Atorvastatin Calcium | Northwind Pharmaceuticals

    Atorvastatin Calcium | Northwind Pharmaceuticals

    There is currently no dosage information available for this product. We apologize for any inconvenience.

  • Atorvastatin Calcium | Cardinal Health
    No Recall

    Atorvastatin Calcium | Cardinal Health

    Atorvastatin Calcium | Cardinal Health
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Aphena Pharma Solutions – Tennessee, Llc
    Atorvastatin Calcium | Aphena Pharma Solutions - Tennessee, Llc
    No Recall

    Atorvastatin Calcium | Aphena Pharma Solutions - Tennessee, Llc

    Atorvastatin Calcium | Aphena Pharma Solutions - Tennessee, Llc
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients with HIV taking nelfinavir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Aphena Pharma Solutions – Tennessee, Llc
    Atorvastatin Calcium | Aphena Pharma Solutions - Tennessee, Llc
    No Recall

    Atorvastatin Calcium | Aphena Pharma Solutions - Tennessee, Llc

    Atorvastatin Calcium | Aphena Pharma Solutions - Tennessee, Llc
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | G&w Laboratories, Inc.
    No Recall

    Atorvastatin Calcium | G&w Laboratories, Inc.

    Atorvastatin Calcium | G&w Laboratories, Inc.

    Apply a thin layer of clobetasol propionate cream to the affected skin areas twice daily and rub in gently and completely. Clobetasol propionate cream is a superhigh potency topical corticosteroid; therefore, treatment should be limited to 2 consecutive weeks, and amounts greater than 50 g per week should not be used.

    As with other highly active corticosteroids, therapy should be discontinued when control has been achieved. If no improvement is seen within 2 weeks, reassessment of diagnosis may be necessary.

    Clobetasol propionate cream should not be used with occlusive dressings.

  • Atorvastatin Calcium | Amylin Pharmaceuticals, Llc
    No Recall

    Atorvastatin Calcium | Amylin Pharmaceuticals, Llc

    Atorvastatin Calcium | Amylin Pharmaceuticals, Llc
    2.1 Recommended Dosing

    BYDUREON (2 mg per dose) should be administered once every 7 days (weekly). The dose can be administered at any time of day, with or without meals.

    Missed Dose

    If a dose is missed, it should be administered as soon as noticed, provided the next regularly scheduled dose is due at least 3 days later. Thereafter, patients can resume their usual dosing schedule of once every 7 days (weekly).

    If a dose is missed and the next regularly scheduled dose is due 1 or 2 days later, the patient should not administer the missed dose and instead resume BYDUREON with the next regularly scheduled dose.

    Changing Weekly Dosing Schedule

    The day of weekly administration can be changed if necessary as long as the last dose was administered 3 or more days before.

    2.2 Administration

    BYDUREON must be injected immediately after the dose is prepared. BYDUREON is administered as a subcutaneous (SC) injection in the abdomen, thigh, or upper arm region. Advise patients to use a different injection site each week when injecting in the same region. BYDUREON must not be administered intravenously or intramuscularly. BYDUREON is intended for patient self-administration.

    Prior to initiation of BYDUREON, patients should be trained by their healthcare professional. For the BYDUREON Pen, study data demonstrated that training reduced the risk of administration errors such as inadequate mixing or incomplete dosing. Patients using the BYDUREON Pen should be trained on proper mixing and injection technique to ensure the product is adequately mixed and a full dose is delivered. Refer to the accompanying Instructions for Use for complete administration instructions with illustrations. The instructions can also be found at www.bydureon.com.

    2.3 Changing from BYETTA to BYDUREON

    Prior treatment with BYETTA is not required when initiating BYDUREON therapy. If the decision is made to start BYDUREON in an appropriate patient already taking BYETTA, BYETTA should be discontinued. Patients changing from BYETTA to BYDUREON may experience transient (approximately 2 weeks) elevations in blood glucose concentrations.

    2.1 Recommended Dosing

    BYDUREON (2 mg per dose) should be administered once every 7 days (weekly). The dose can be administered at any time of day, with or without meals.

    Missed Dose

    If a dose is missed, it should be administered as soon as noticed, provided the next regularly scheduled dose is due at least 3 days later. Thereafter, patients can resume their usual dosing schedule of once every 7 days (weekly).

    If a dose is missed and the next regularly scheduled dose is due 1 or 2 days later, the patient should not administer the missed dose and instead resume BYDUREON with the next regularly scheduled dose.

    Changing Weekly Dosing Schedule

    The day of weekly administration can be changed if necessary as long as the last dose was administered 3 or more days before.

    Missed Dose

    If a dose is missed, it should be administered as soon as noticed, provided the next regularly scheduled dose is due at least 3 days later. Thereafter, patients can resume their usual dosing schedule of once every 7 days (weekly).

    If a dose is missed and the next regularly scheduled dose is due 1 or 2 days later, the patient should not administer the missed dose and instead resume BYDUREON with the next regularly scheduled dose.

    Changing Weekly Dosing Schedule

    The day of weekly administration can be changed if necessary as long as the last dose was administered 3 or more days before.

    2.2 Administration

    BYDUREON must be injected immediately after the dose is prepared. BYDUREON is administered as a subcutaneous (SC) injection in the abdomen, thigh, or upper arm region. Advise patients to use a different injection site each week when injecting in the same region. BYDUREON must not be administered intravenously or intramuscularly. BYDUREON is intended for patient self-administration.

    Prior to initiation of BYDUREON, patients should be trained by their healthcare professional. For the BYDUREON Pen, study data demonstrated that training reduced the risk of administration errors such as inadequate mixing or incomplete dosing. Patients using the BYDUREON Pen should be trained on proper mixing and injection technique to ensure the product is adequately mixed and a full dose is delivered. Refer to the accompanying Instructions for Use for complete administration instructions with illustrations. The instructions can also be found at www.bydureon.com.

    2.3 Changing from BYETTA to BYDUREON

    Prior treatment with BYETTA is not required when initiating BYDUREON therapy. If the decision is made to start BYDUREON in an appropriate patient already taking BYETTA, BYETTA should be discontinued. Patients changing from BYETTA to BYDUREON may experience transient (approximately 2 weeks) elevations in blood glucose concentrations.

  • Sandoz Inc
    Atorvastatin Calcium | Mylan Institutional Inc.
    No Recall

    Atorvastatin Calcium | Mylan Institutional Inc.

    Atorvastatin Calcium | Mylan Institutional Inc.

    Divalproex sodium extended-release tablets are an extended-release product intended for once-a-day oral administration. Divalproex sodium extended-release tablets should be swallowed whole and should not be crushed or chewed.

    2.1 Mania

    Divalproex sodium extended-release tablets are administered orally. The recommended initial dose is 25 mg/kg/day given once daily. The dose should be increased as rapidly as possible to achieve the lowest therapeutic dose which produces the desired clinical effect or the desired range of plasma concentrations. In a placebo-controlled clinical trial of acute mania or mixed type, patients were dosed to a clinical response with a trough plasma concentration between 85 and 125 mcg/mL. The maximum recommended dosage is 60 mg/kg/day.

    There is no body of evidence available from controlled trials to guide a clinician in the longer term management of a patient who improves during divalproex sodium extended-release tablet treatment of an acute manic episode. While it is generally agreed that pharmacological treatment beyond an acute response in mania is desirable, both for maintenance of the initial response and for prevention of new manic episodes, there are no data to support the benefits of divalproex sodium extended-release tablets in such longer-term treatment (i.e., beyond 3 weeks).

    2.2 Epilepsy

    Divalproex sodium extended-release tablets are administered orally, and must be swallowed whole. As divalproex sodium extended-release tablets dosage is titrated upward, concentrations of clonazepam, diazepam, ethosuximide, lamotrigine, tolbutamide, phenobarbital, carbamazepine, and/or phenytoin may be affected [see Drug Interactions (7.2)].

    Complex Partial Seizures

    For adults and children 10 years of age or older.

    Monotherapy (Initial Therapy)

    Divalproex sodium extended-release tablets have not been systematically studied as initial therapy. Patients should initiate therapy at 10 to 15 mg/kg/day. The dosage should be increased by 5 to 10 mg/kg/week to achieve optimal clinical response. Ordinarily, optimal clinical response is achieved at daily doses below 60 mg/kg/day. If satisfactory clinical response has not been achieved, plasma levels should be measured to determine whether or not they are in the usually accepted therapeutic range (50 to 100 mcg/mL). No recommendation regarding the safety of valproate for use at doses above 60 mg/kg/day can be made.

    The probability of thrombocytopenia increases significantly at total trough valproate plasma concentrations above 110 mcg/mL in females and 135 mcg/mL in males. The benefit of improved seizure control with higher doses should be weighed against the possibility of a greater incidence of adverse reactions.

    Conversion to Monotherapy

    Patients should initiate therapy at 10 to 15 mg/kg/day. The dosage should be increased by 5 to 10 mg/kg/week to achieve optimal clinical response. Ordinarily, optimal clinical response is achieved at daily doses below 60 mg/kg/day. If satisfactory clinical response has not been achieved, plasma levels should be measured to determine whether or not they are in the usually accepted therapeutic range (50 to 100 mcg/mL). No recommendation regarding the safety of valproate for use at doses above 60 mg/kg/day can be made.

    Concomitant antiepilepsy drug (AED) dosage can ordinarily be reduced by approximately 25% every 2 weeks. This reduction may be started at initiation of divalproex sodium extended-release tablets therapy, or delayed by 1 to 2 weeks if there is a concern that seizures are likely to occur with a reduction. The speed and duration of withdrawal of the concomitant AED can be highly variable, and patients should be monitored closely during this period for increased seizure frequency.

    Adjunctive Therapy

    Divalproex sodium extended-release tablets may be added to the patient's regimen at a dosage of 10 to 15 mg/kg/day. The dosage may be increased by 5 to 10 mg/kg/week to achieve optimal clinical response. Ordinarily, optimal clinical response is achieved at daily doses below 60 mg/kg/day. If satisfactory clinical response has not been achieved, plasma levels should be measured to determine whether or not they are in the usually accepted therapeutic range (50 to 100 mcg/mL). No recommendation regarding the safety of valproate for use at doses above 60 mg/kg/day can be made.

    In a study of adjunctive therapy for complex partial seizures in which patients were receiving either carbamazepine or phenytoin in addition to valproate, no adjustment of carbamazepine or phenytoin dosage was needed [see Clinical Studies (14.2)]. However, since valproate may interact with these or other concurrently administered AEDs as well as other drugs, periodic plasma concentration determinations of concomitant AEDs are recommended during the early course of therapy [see Drug Interactions (7)].

    Simple and Complex Absence Seizures

    The recommended initial dose is 15 mg/kg/day, increasing at one week intervals by 5 to 10 mg/kg/day until seizures are controlled or side effects preclude further increases. The maximum recommended dosage is 60 mg/kg/day.

    A good correlation has not been established between daily dose, serum concentrations, and therapeutic effect. However, therapeutic valproate serum concentration for most patients with absence seizures is considered to range from 50 to 100 mcg/mL. Some patients may be controlled with lower or higher serum concentrations [see Clinical Pharmacology (12.3)].

    As divalproex sodium extended-release tablets dosage is titrated upward, blood concentrations of phenobarbital and/or phenytoin may be affected [see Drug Interactions (7.2)].

    Antiepilepsy drugs should not be abruptly discontinued in patients in whom the drug is administered to prevent major seizures because of the strong possibility of precipitating status epilepticus with attendant hypoxia and threat to life.

    2.3 Migraine

    Divalproex sodium extended-release tablets are indicated for prophylaxis of migraine headaches in adults.

    The recommended starting dose is 500 mg once daily for one week, thereafter increasing to 1000 mg once daily. Although doses other than 1000 mg once daily of divalproex sodium extended-release tablets have not been evaluated in patients with migraine, the effective dose range of divalproex sodium delayed-release tablets in these patients is 500 to 1000 mg/day. As with other valproate products, doses of divalproex sodium extended-release tablets should be individualized and dose adjustment may be necessary. If a patient requires smaller dose adjustments than that available with divalproex sodium extended-release tablets, divalproex sodium delayed-release tablets should be used instead.

    2.4 Conversion from Divalproex Sodium Delayed-release Tablets to Divalproex Sodium Extended-release Tablets

    In adult patients and pediatric patients 10 years of age or older with epilepsy previously receiving divalproex sodium delayed-release tablets, divalproex sodium extended-release tablets should be administered once daily using a dose 8% to 20% higher than the total daily dose of divalproex sodium delayed-release tablets (Table 1). For patients whose divalproex sodium delayed-release tablets total daily dose cannot be directly converted to divalproex sodium extended-release tablets, consideration may be given at the clinician’s discretion to increase the patient’s divalproex sodium delayed-release tablets total daily dose to the next higher dosage before converting to the appropriate total daily dose of divalproex sodium extended-release tablets.

    Table 1. Dose Conversion * These total daily doses of divalproex sodium delayed-release tablets cannot be directly converted to an 8% to 20% higher total daily dose of divalproex sodium extended-release tablets because the required dosing strengths of divalproex sodium extended-release tablets are not available. Consideration may be given at the clinician’s discretion to increase the patient’s divalproex sodium delayed-release tablets total daily dose to the next higher dosage before converting to the appropriate total daily dose of divalproex sodium extended-release tablets.

    Divalproex Sodium Delayed-release Tablets
    Total Daily Dose (mg)

    Divalproex Sodium Extended-release Tablets
    (mg)

    500* to 625

    750

    750* to 875

    1000

    1000* to 1125

    1250

    1250 to 1375

    1500

    1500 to 1625

    1750

    1750

    2000

    1875 to 2000

    2250

    2125 to 2250

    2500

    2375

    2750

    2500 to 2750

    3000

    2875

    3250

    3000 to 3125

    3500

    There is insufficient data to allow a conversion factor recommendation for patients with divalproex sodium delayed-release tablets doses above 3125 mg/day. Plasma valproate Cmin concentrations for divalproex sodium extended-release tablets on average are equivalent to divalproex sodium delayed-release tablets, but may vary across patients after conversion. If satisfactory clinical response has not been achieved, plasma levels should be measured to determine whether or not they are in the usually accepted therapeutic range (50 to 100 mcg/mL) [see Clinical Pharmacology (12.2)].

    2.5 General Dosing Advice Dosing in Elderly Patients

    Due to a decrease in unbound clearance of valproate and possibly a greater sensitivity to somnolence in the elderly, the starting dose should be reduced in these patients. Starting doses in the elderly lower than 250 mg can only be achieved by the use of divalproex sodium delayed-release tablets. Dosage should be increased more slowly and with regular monitoring for fluid and nutritional intake, dehydration, somnolence, and other adverse reactions. Dose reductions or discontinuation of valproate should be considered in patients with decreased food or fluid intake and in patients with excessive somnolence. The ultimate therapeutic dose should be achieved on the basis of both tolerability and clinical response [see Warnings and Precautions (5.14), Use in Specific Populations (8.5) and Clinical Pharmacology (12.3)].

    Dose Related Adverse Reactions

    The frequency of adverse effects (particularly elevated liver enzymes and thrombocytopenia) may be dose related. The probability of thrombocytopenia appears to increase significantly at total valproate concentrations of ≥ 110 mcg/mL (females) or ≥ 135 mcg/mL (males) [see Warnings and Precautions (5.8)]. The benefit of improved therapeutic effect with higher doses should be weighed against the possibility of a greater incidence of adverse reactions.

    G.I. Irritation

    Patients who experience G.I. irritation may benefit from administration of the drug with food or by slowly building up the dose from an initial low level.

    Compliance

    Patients should be informed to take divalproex sodium extended-release tablets every day as prescribed. If a dose is missed it should be taken as soon as possible, unless it is almost time for the next dose. If a dose is skipped, the patient should not double the next dose.

  • Atorvastatin Calcium | Carilion Materials Management
    No Recall

    Atorvastatin Calcium | Carilion Materials Management

    Atorvastatin Calcium | Carilion Materials Management

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia ( Types IIa and IIb)  Fredrickson

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current ). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.    NCEP Guidelines

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current , , and ]. Adjustments should be made at intervals of 4 weeks or more. NCEP Pediatric Panel GuidelinesClinical Pharmacology (12)Indications and Usage (1.2)

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see , ]. Warnings and Precautions, Skeletal Muscle (5.1)Drug Interactions (7)

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see , ]. Warnings and Precautions, Skeletal Muscle (5.1)Clinical Pharmacology, Pharmacokinetics (12.3)

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see , ]. Warnings and Precautions,Skeletal Muscle (5.1)Drug Interactions (7)

  • Mylan Pharmaceuticals Inc.
    Atorvastatin Calcium | Mylan Pharmaceuticals Inc.
    No Recall

    Atorvastatin Calcium | Mylan Pharmaceuticals Inc.

    Atorvastatin Calcium | Mylan Pharmaceuticals Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 mg to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 Years of Age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 mg to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients with Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Atorvastatin Calcium | Ranbaxy Pharmaceuticals Inc.
    No Recall

    Atorvastatin Calcium | Ranbaxy Pharmaceuticals Inc.

    Atorvastatin Calcium | Ranbaxy Pharmaceuticals Inc.
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology(12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • St Marys Medical Park Pharmacy
    Atorvastatin Calcium | St Marys Medical Park Pharmacy
    No Recall

    Atorvastatin Calcium | St Marys Medical Park Pharmacy

    Atorvastatin Calcium | St Marys Medical Park Pharmacy

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb) 

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)  

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • State Of Florida Doh Central Pharmacy
    Atorvastatin Calcium | State Of Florida Doh Central Pharmacy
    No Recall

    Atorvastatin Calcium | State Of Florida Doh Central Pharmacy

    Atorvastatin Calcium | State Of Florida Doh Central Pharmacy
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10–17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Proficient Rx Lp
    Atorvastatin Calcium | Proficient Rx Lp
    No Recall

    Atorvastatin Calcium | Proficient Rx Lp

    Atorvastatin Calcium | Proficient Rx Lp
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets are 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets are 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.   

    2.2  Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia  

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy 

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors 

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin and the lowest dose necessary employed.  In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin should be limited to  20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

  • Northwind Pharmaceuticals
    Atorvastatin Calcium | Northwind Pharmaceuticals
    No Recall

    Atorvastatin Calcium | Northwind Pharmaceuticals

    Atorvastatin Calcium | Northwind Pharmaceuticals

    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10-17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients With Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].


    Please review the manufacturer's complete drug information available from the FDA at www.fda.gov
    Permanent Link: http://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=9d6a052b-b032-4d72-9bd1-e6c895b12472

  • Atorvastatin Calcium | Directrx
    No Recall

    Atorvastatin Calcium | Directrx

    Atorvastatin Calcium | Directrx
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients with Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)]. 

  • Atorvastatin Calcium | Directrx
    No Recall

    Atorvastatin Calcium | Directrx

    Atorvastatin Calcium | Directrx
    2.1 Hyperlipidemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia (Fredrickson Types IIa and IIb)

    The recommended starting dose of atorvastatin calcium tablets is 10 or 20 mg once daily. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of atorvastatin calcium tablets is 10 to 80 mg once daily. Atorvastatin calcium tablets can be administered as a single dose at any time of the day, with or without food. The starting dose and maintenance doses of atorvastatin calcium tablets should be individualized according to patient characteristics such as goal of therapy and response (see current NCEP Guidelines). After initiation and/or upon titration of atorvastatin calcium tablets, lipid levels should be analyzed within 2 to 4 weeks and dosage adjusted accordingly.

    2.2 Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to 17 years of age)

    The recommended starting dose of atorvastatin calcium tablets is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy [see current NCEP Pediatric Panel Guidelines, Clinical Pharmacology (12), and Indications and Usage (1.2)]. Adjustments should be made at intervals of 4 weeks or more.

    2.3 Homozygous Familial Hypercholesterolemia

    The dosage of atorvastatin calcium tablets in patients with homozygous FH is 10 to 80 mg daily. Atorvastatin calcium tablets should be used as an adjunct to other lipid-lowering treatments (e.g., LDL apheresis) in these patients or if such treatments are unavailable.

    2.4 Concomitant Lipid-Lowering Therapy

    Atorvastatin calcium tablets may be used with bile acid resins. The combination of HMG-CoA reductase inhibitors (statins) and fibrates should generally be used with caution [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].

    2.5 Dosage in Patients with Renal Impairment

    Renal disease does not affect the plasma concentrations nor LDL-C reduction of atorvastatin calcium tablets; thus, dosage adjustment in patients with renal dysfunction is not necessary [see Warnings and Precautions, Skeletal Muscle (5.1), Clinical Pharmacology, Pharmacokinetics (12.3)].

    2.6 Dosage in Patients Taking Cyclosporine, Clarithromycin, Itraconazole, or Certain Protease Inhibitors

    In patients taking cyclosporine or the HIV protease inhibitors (tipranavir plus ritonavir) or the hepatitis C protease inhibitor (telaprevir), therapy with atorvastatin calcium tablets should be avoided. In patients with HIV taking lopinavir plus ritonavir, caution should be used when prescribing atorvastatin calcium tablets and the lowest dose necessary employed. In patients taking clarithromycin, itraconazole, or in patients with HIV taking a combination of saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, or fosamprenavir plus ritonavir, therapy with atorvastatin calcium tablets should be limited to 20 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium is employed. In patients taking the HIV protease inhibitor nelfinavir or the hepatitis C protease inhibitor boceprevir, therapy with atorvastatin calcium tablets should be limited to 40 mg, and appropriate clinical assessment is recommended to ensure that the lowest dose necessary of atorvastatin calcium tablets is employed [see Warnings and Precautions, Skeletal Muscle (5.1), Drug Interactions (7)].