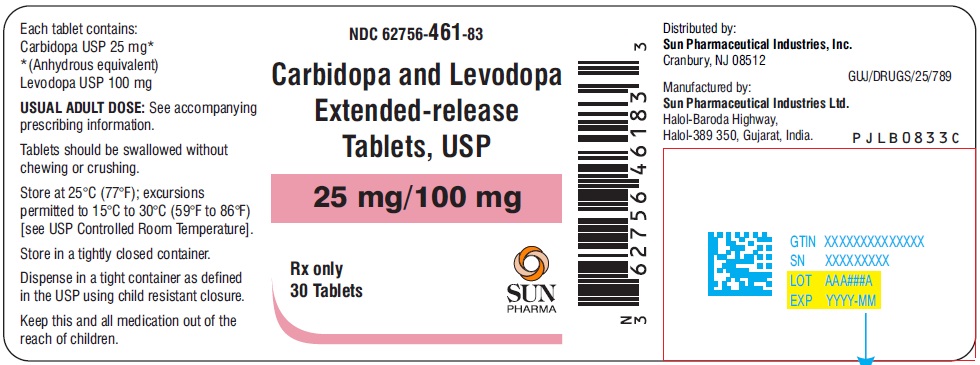
Carbidopa and levodopa extended release tablets contain carbidopa and levodopa in a 1:4 ratio as either the 50 mg/200 mg tablet or the 25 mg/100 mg tablet. The daily dosage of carbidopa and levodopa extended release tablets must be determined by careful titration. Patients should be monitored closely during the dose adjustment period, particularly with regard to appearance or worsening of involuntary movements, dyskinesias or nausea. Carbidopa and levodopa extended release tablets 50 mg/200 mg may be administered as whole or as half-tablets which should not be chewed or crushed. Carbidopa and levodopa extended release tablets 25 mg/100 mg may be used in combination with carbidopa and levodopa extended release tablets 50 mg/200 mg to titrate to the optimum dosage, or as an alternative to the 50 mg/200 mg half-tablet.
Standard drugs for Parkinson’s disease, other than levodopa without a decarboxylase inhibitor, may be used concomitantly while carbidopa and levodopa extended release tablet is being administered, although their dosage may have to be adjusted.
Since carbidopa prevents the reversal of levodopa effects caused by pyridoxine, carbidopa and levodopa extended release tablets can be given to patients receiving supplemental pyridoxine (vitamin B6).
Initial Dosage
Patients currently treated with conventional carbidopa and levodopa preparations: Studies show that peripheral dopa-decarboxylase is saturated by the bioavailable carbidopa at doses of 70 mg a day and greater. Because the bioavailabilities of carbidopa and levodopa in carbidopa and levodopa tablets and carbidopa and levodopa extended release tablets are different, appropriate adjustments should be made, as shown in Table II.
Table II Approximate Bioavailabilities at Steady State*
Tablet
Amount of Levodopa (mg) in
Each Tablet
Approximate Bioavailability
Approximate Amount of Bioavailable
Levodopa (mg) in Each Tablet
Carbidopa and levodopa
50 mg/200 mg
extended release tablets
200
0.70-0.75†
140-150
Carbidopa and levodopa tablets
25 mg/100 mg
100
0.99‡
99
* This table is only a guide to bioavailabilities since other factors such as food, drugs, and inter-patient variabilities may affect the bioavailability of carbidopa and levodopa.
† The extent of availability of levodopa from carbidopa and levodopa extended release tablets was about 70-75% relative to intravenous levodopa or standard carbidopa and levodopa tablets in the elderly.
‡
The extent of availability of levodopa from carbidopa and levodopa tablets was 99% relative to intravenous levodopa in the healthy elderly.
Dosage with carbidopa and levodopa extended release tablets should be substituted at an amount that provides approximately 10% more levodopa per day, although this may need to be increased to a dosage that provides up to 30% more levodopa per day depending on clinical response (see DOSAGE AND ADMINISTRATION, Titration). The interval between doses of carbidopa and levodopa extended release tablets should be 4-8 hours during the waking day (See CLINICAL PHARMACOLOGY, Pharmacodynamics).
A guideline for initiation of carbidopa and levodopa extended release tablets is shown in Table III.
Table III Guidelines for Initial Conversion From Carbidopa and Levodopa Tablets To Carbidopa and Levodopa Extended Release Tablets
carbidopa and levodopa tablets
Total Daily Dose*
Levodopa (mg)
carbidopa and levodopa extended release tablets
Suggested
Dosage Regimen
300-400
200 mg b.i.d.
500-600
300 mg b.i.d. -or- 200 mg t.i.d.
700-800
A total of 800 mg in 3 or more divided doses (e.g., 300 mg a.m., 300 mg early p.m., and
200 mg later p.m.)
900-1000
A total of 1000 mg in 3 or more divided doses (e.g., 400 mg a.m., 400 mg early p.m., and
200 mg later p.m.)
* For dosing ranges not shown in the table, see
DOSAGE AND ADMINISTRATION, Initial Dosage, Patients currently treated with conventional carbidopa and levodopa preparations.
Patients currently treated with levodopa without a decarboxylase inhibitor
Levodopa must be discontinued at least twelve hours before therapy with carbidopa and levodopa extended release tablets is started. Carbidopa and levodopa extended release tablets should be substituted at a dosage that will provide approximately 25% of the previous levodopa dosage. In patients with mild to moderate disease, the initial dose is usually 1 tablet of carbidopa and levodopa extended release tablets 50 mg/200 mg b.i.d.
Patients not receiving levodopa
In patients with mild to moderate disease, the initial recommended dose is 1 tablet of carbidopa and levodopa extended release tablets 50 mg/200 mg b.i.d. Initial dosage should not be given at intervals of less than 6 hours.
Titration with Carbidopa and Levodopa Extended Release Tablets
Following initiation of therapy, doses and dosing intervals may be increased or decreased depending upon therapeutic response. Most patients have been adequately treated with doses of carbidopa and levodopa extended release tablets that provide 400 to 1600 mg of levodopa per day, administered as divided doses at intervals ranging from 4 to 8 hours during the waking day. Higher doses of carbidopa and levodopa extended release tablets (2400 mg or more of levodopa per day) and shorter intervals (less than 4 hours) have been used, but are not usually recommended.
When doses of carbidopa and levodopa extended release tablets are given at intervals of less than 4 hours, and/or if the divided doses are not equal, it is recommended that the smaller doses be given at the end of the day.
An interval of at least 3 days between dosage adjustments is recommended.
Maintenance
Because Parkinson’s disease is progressive, periodic clinical evaluations are recommended; adjustment of the dosage regimen of carbidopa and levodopa extended release tablets may be required.
Addition of Other Antiparkinson Medications
Anticholinergic agents, dopamine agonists, and amantadine can be given with carbidopa and levodopa extended release tablets. Dosage adjustment of carbidopa and levodopa extended release tablets may be necessary when these agents are added.
A dose of carbidopa and levodopa tablets 25 mg/100 mg or 10 mg/100 mg (one half or a whole tablet) can be added to the dosage regimen of carbidopa and levodopa extended release tablets in selected patients with advanced disease who need additional immediate-release levodopa for a brief time during daytime hours.
Interruption of Therapy
Sporadic cases of a symptom complex resembling Neuroleptic Malignant Syndrome (NMS) have been associated with dose reductions and withdrawal of carbidopa and levodopa tablets or carbidopa and levodopa extended release tablets.
Patients should be observed carefully if abrupt reduction or discontinuation of carbidopa and levodopa extended release tablets is required, especially if the patient is receiving neuroleptics (See WARNINGS).
If general anesthesia is required, carbidopa and levodopa extended release tablets may be continued as long as the patient is permitted to take oral medication. If therapy is interrupted temporarily, the patient should be observed for symptoms resembling NMS, and the usual dosage should be administered as soon as the patient is able to take oral medication.