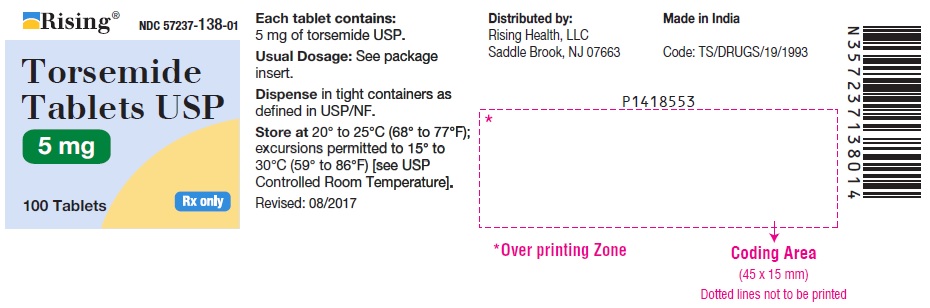
Torsemide label

Torsemide

Torsemide Recall

Get an alert when a recall is issued.

Side Effects & Adverse Reactions

Hepatic Disease With Cirrhosis and Ascites

Torsemide should be used with caution in patients with hepatic disease with cirrhosis and ascites, since sudden alterations of fluid and electrolyte balance may precipitate hepatic coma. In these patients, diuresis with torsemide (or any other diuretic) is best initiated in the hospital. To prevent hypokalemia and metabolic alkalosis, an aldosterone antagonist or potassium-sparing drug should be used concomitantly with torsemide.

Ototoxicity

Tinnitus and hearing loss (usually reversible) have been observed after rapid intravenous injection of other loop diuretics and have also been observed after oral torsemide. It is not certain that these events were attributable to torsemide. Ototoxicity has also been seen in animal studies when very high plasma levels of torsemide were induced.

 
Volume and Electrolyte Depletion

Patients receiving diuretics should be observed for clinical evidence of electrolyte imbalance, hypovolemia, or prerenal azotemia. Symptoms of these disturbances may include one or more of the following: dryness of the mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, nausea, and vomiting. Excessive diuresis may cause dehydration, blood-volume reduction, and possibly thrombosis and embolism, especially in elderly patients. In patients who develop fluid and electrolyte imbalances, hypovolemia, or prerenal azotemia, the observed laboratory changes may include hyper- or hyponatremia, hyper- or hypochloremia, hyper- or hypokalemia, acid-base abnormalities, and increased blood urea nitrogen (BUN). If any of these occur, torsemide should be discontinued until the situation is corrected; torsemide may be restarted at a lower dose.

In controlled studies in the United States, torsemide was administered to hypertensive patients at doses of 5 mg or 10 mg daily. After 6 weeks at these doses, the mean decrease in serum potassium was approximately 0.1 mEq/L. The percentage of patients who had a serum potassium level below 3.5 mEq/L at any time during the studies was essentially the same in patients who received torsemide (1.5%) as in those who received placebo (3%). In patients followed for 1 year, there was no further change in mean serum potassium levels. In patients with congestive heart failure, hepatic cirrhosis, or renal disease treated with torsemide at doses higher than those studied in United States antihypertensive trials, hypokalemia was observed with greater frequency, in a dose-related manner.

In patients with cardiovascular disease, especially those receiving digitalis glycosides, diuretic-induced hypokalemia may be a risk factor for the development of arrhythmias. The risk of hypokalemia is greatest in patients with cirrhosis of the liver, in patients experiencing a brisk diuresis, in patients who are receiving inadequate oral intake of electrolytes, and in patients receiving concomitant therapy with corticosteroids or ACTH.

Periodic monitoring of serum potassium and other electrolytes is advised in patients treated with torsemide.

FDA Safety Alerts

There are currently no FDA safety alerts available for this drug.

Manufacturer Warnings

There is currently no manufacturer warning information available for this drug.

FDA Labeling Changes

There are currently no FDA labeling changes available for this drug.

Uses

Torsemide tablet is indicated for the treatment of edema associated with congestive heart failure, renal disease, or hepatic disease. Use of torsemide has been found to be effective for the treatment of edema associated with chronic renal failure. Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

Torsemide tablets are indicated for the treatment of hypertension alone or in combination with other antihypertensive agents.

History

There is currently no drug history available for this drug.

Other Information

Torsemide is a diuretic of the pyridine-sulfonylurea class. Its chemical name is 1-isopropyl-3-[(4-m-toluidino-3-pyridyl) sulfonyl]urea and its structural formula is:

Structure.jpg

C16H20N4O3S          M.W. 348.43

Its pKa is 7.1.

Torsemide is a white to off-white crystalline powder. Each torsemide tablet, for oral administration contains 5 mg, 10 mg, 20 mg or 100 mg of torsemide, USP. In addition, each tablet contains the following inactive ingredients: colloidal silicon dioxide, corn starch, lactose monohydrate, magnesium stearate and sodium starch glycolate.

Torsemide Manufacturers

  • Avkare, Inc.
    Torsemide | Avkare, Inc.
    No Recall

    Torsemide | Avkare, Inc.

    Torsemide | Avkare, Inc.

    General
    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis
    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide tablets, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Par Pharmaceutical Inc
    Torsemide | Par Pharmaceutical Inc
    No Recall

    Torsemide | Par Pharmaceutical Inc

    Torsemide | Par Pharmaceutical Inc
    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Because of the high bioavailability of torsemide, oral and intravenous doses are therapeutically equivalent, so patients may be switched to and from the intravenous form with no change in dose.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • General Injectables And Vaccines, Inc.
    Torsemide | General Injectables And Vaccines, Inc.
    No Recall

    Torsemide | General Injectables And Vaccines, Inc.

    Torsemide | General Injectables And Vaccines, Inc.

    General: Special dosage adjustment in the elderly is not necessary.
    Because of the high bioavailability of torsemide, oral and intravenous doses are therapeutically
    equivalent, so patients may be switched to and from the intravenous form with no change in dose.
    Torsemide injection should be administered either slowly as a bolus over a period of 2 minutes or
    administered as a continuous infusion.
    If torsemide is administered through an IV line, it is recommended that, as with other IV injections,
    the IV line be flushed with Normal Saline (Sodium Chloride Injection) before and after administration.
    Torsemide injection is formulated above pH 8.3. Flushing the line is recommended to avoid the potential
    for incompatibilities caused by differences in pH which could be indicated by color change, haziness or
    the formation of a precipitate in the solution.
    If torsemide injection is administered as a continuous infusion, stability has been demonstrated through
    24 hours at room temperature in plastic containers for the following fluids and concentrations:
    200 mg torsemide (10 mg/mL) added to:
    250 mL Dextrose 5% in water
    250 mL 0.9% Sodium Chloride
    500 mL 0.45% Sodium Chloride
    50 mg torsemide (10 mg/mL) added to:
    500 mL Dextrose 5% in water
    500 mL 0.9% Sodium Chloride
    500 mL 0.45% Sodium Chloride
    Before administration, the solution of torsemide injection should be visually inspected for discoloration
    and particulate matter. If either is found, the vial should not be used.
    Congestive Heart Failure
    The usual initial dose is 10 mg or 20 mg of intravenous torsemide. II the diuretic response is inadequate,
    the dose should be titrated upward by approximately doubling until the desired diuretic response is
    obtained. Single doses higher than 200 mg have not been adequately studied.
    Chronic Renal Failure
    The usual initial dose of torsemide is 20 mg of intravenous torsemide. If the diuretic response is
    inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic
    response is obtained. Single doses higher than 200 mg have not been adequately studied.
    Hepatic Cirrhosis
    The usual initial dose is 5 mg or 10 mg of intravenous torsemide, administered together with an
    aldosterone antagonist or a potassium·sparing diuretic. If the diuretic response is inadequate, the dose
    should be titrated upward by approximately doubling until the desired diuretic response is obtained.
    Single doses higher than 40 mg have not been adequately studied.
    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled
    trials.
    HypertenSion
    The usual initial dose is 5 mg daily. If the 5 mg dose does not provide adequate reduction in blood
    pressure within 4 to 6 weeks, the dose may be increased to 10 mg daily. If the response to 10 mg is
    insufficient, an additional anti-hypertensive agent should be added to the treatment regimen.

  • General Injectables And Vaccines, Inc.
    Torsemide | General Injectables And Vaccines, Inc.
    No Recall

    Torsemide | General Injectables And Vaccines, Inc.

    Torsemide | General Injectables And Vaccines, Inc.

    General: Special dosage adjustment in the elderly is not necessary.
    Because of the high bioavailability of torsemide, oral and intravenous doses are therapeutically
    equivalent, so patients may be switched to and from the intravenous form with no change in dose.
    Torsemide injection should be administered either slowly as a bolus over a period of 2 minutes or
    administered as a continuous infusion.
    If torsemide is administered through an IV line, it is recommended that, as with other IV injections,
    the IV line be flushed with Normal Saline (Sodium Chloride Injection) before and after administration.
    Torsemide injection is formulated above pH 8.3. Flushing the line is recommended to avoid the potential
    for incompatibilities caused by differences in pH which could be indicated by color change, haziness or
    the formation of a precipitate in the solution.
    If torsemide injection is administered as a continuous infusion, stability has been demonstrated through
    24 hours at room temperature in plastic containers for the following fluids and concentrations:
    200 mg torsemide (10 mg/mL) added to:
    250 mL Dextrose 5% in water
    250 mL 0.9% Sodium Chloride
    500 mL 0.45% Sodium Chloride
    50 mg torsemide (10 mg/mL) added to:
    500 mL Dextrose 5% in water
    500 mL 0.9% Sodium Chloride
    500 mL 0.45% Sodium Chloride
    Before administration, the solution of torsemide injection should be visually inspected for discoloration
    and particulate matter. If either is found, the vial should not be used.
    Congestive Heart Failure
    The usual initial dose is 10 mg or 20 mg of intravenous torsemide. II the diuretic response is inadequate,
    the dose should be titrated upward by approximately doubling until the desired diuretic response is
    obtained. Single doses higher than 200 mg have not been adequately studied.
    Chronic Renal Failure
    The usual initial dose of torsemide is 20 mg of intravenous torsemide. If the diuretic response is
    inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic
    response is obtained. Single doses higher than 200 mg have not been adequately studied.
    Hepatic Cirrhosis
    The usual initial dose is 5 mg or 10 mg of intravenous torsemide, administered together with an
    aldosterone antagonist or a potassium·sparing diuretic. If the diuretic response is inadequate, the dose
    should be titrated upward by approximately doubling until the desired diuretic response is obtained.
    Single doses higher than 40 mg have not been adequately studied.
    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled
    trials.
    HypertenSion
    The usual initial dose is 5 mg daily. If the 5 mg dose does not provide adequate reduction in blood
    pressure within 4 to 6 weeks, the dose may be increased to 10 mg daily. If the response to 10 mg is
    insufficient, an additional anti-hypertensive agent should be added to the treatment regimen.

  • Torsemide | Cardinal Health
    No Recall

    Torsemide | Cardinal Health

    Torsemide | Cardinal Health
    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Because of the high bioavailability of torsemide, oral and intravenous doses are therapeutically equivalent, so patients may be switched to and from the intravenous form with no change in dose.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Ncs Healthcare Of Ky, Inc Dba Vangard Labs
    Torsemide | Ncs Healthcare Of Ky, Inc Dba Vangard Labs
    No Recall

    Torsemide | Ncs Healthcare Of Ky, Inc Dba Vangard Labs

    Torsemide | Ncs Healthcare Of Ky, Inc Dba Vangard Labs

    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once-daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once-daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Physicians Total Care, Inc.
    Torsemide | Physicians Total Care, Inc.
    No Recall

    Torsemide | Physicians Total Care, Inc.

    Torsemide | Physicians Total Care, Inc.
    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Because of the high bioavailability of torsemide, oral and intravenous doses are therapeutically equivalent, so patients may be switched to and from the intravenous form with no change in dose.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Qualitest Pharmaceuticals
    Torsemide | Qualitest Pharmaceuticals
    No Recall

    Torsemide | Qualitest Pharmaceuticals

    Torsemide | Qualitest Pharmaceuticals
    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Roxane Laboratories, Inc
    Torsemide | Roxane Laboratories, Inc
    No Recall

    Torsemide | Roxane Laboratories, Inc

    Torsemide | Roxane Laboratories, Inc
    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Bryant Ranch Prepack
    Torsemide | Bryant Ranch Prepack
    No Recall

    Torsemide | Bryant Ranch Prepack

    Torsemide | Bryant Ranch Prepack
  • Pliva, Inc
    Torsemide | Pliva, Inc
    No Recall

    Torsemide | Pliva, Inc

    Torsemide | Pliva, Inc
    General

     Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

     The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide tablets. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

     The usual initial dose of torsemide is 20 mg of once-daily oral torsemide tablets. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

     The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide tablets, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

     The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Aurobindo Pharma Limited
    Torsemide | Aurobindo Pharma Limited
    No Recall

    Torsemide | Aurobindo Pharma Limited

    Torsemide | Aurobindo Pharma Limited

    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension
     
    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Bryant Ranch Prepack
    Torsemide | Bryant Ranch Prepack
    No Recall

    Torsemide | Bryant Ranch Prepack

    Torsemide | Bryant Ranch Prepack

    General
    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis
    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.
  • Camber Pharmaceuticals, Inc.
    Torsemide | Camber Pharmaceuticals, Inc.
    No Recall

    Torsemide | Camber Pharmaceuticals, Inc.

    Torsemide | Camber Pharmaceuticals, Inc.

    General
    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis
    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.
  • Torsemide | Apotex Corp.
    No Recall

    Torsemide | Apotex Corp.

    Torsemide | Apotex Corp.
    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Torsemide | Citron Pharma Llc
    No Recall

    Torsemide | Citron Pharma Llc

    Torsemide | Citron Pharma Llc

    Swallow duloxetine delayed-release capsules whole. Do not chew or crush. Do not open the capsule and sprinkle its contents on food or mix with liquids. All of these might affect the enteric coating. Duloxetine delayed-release capsules can be given without regard to meals. If a dose of duloxetine delayed-release capsules is missed, take the missed dose as soon as it is remembered. If it is almost time for the next dose, skip the missed dose and take the next dose at the regular time. Do not take two doses of duloxetine delayed-release capsules at the same time.

    2.1 Dosage for Treatment of Major Depressive Disorder

    Administer duloxetine delayed-release capsules at a total dose of 40 mg/day (given as 20 mg twice daily) to 60 mg/day (given either once daily or as 30 mg twice daily). For some patients, it may be desirable to start at 30 mg once daily for 1 week, to allow patients to adjust to the medication before increasing to 60 mg once daily. While a 120 mg/day dose was shown to be effective, there is no evidence that doses greater than 60 mg/day confer any additional benefits. The safety of doses above 120 mg/day has not been adequately evaluated. Periodically reassess to determine the need for maintenance treatment and the appropriate dose for such treatment [see Clinical Studies (14.1)].

    2.2 Dosage for Treatment of Generalized Anxiety Disorder

    Adults — For most patients, initiate duloxetine delayed-release capsules 60 mg once daily. For some patients, it may be desirable to start at 30 mg once daily for 1 week, to allow patients to adjust to the medication before increasing to 60 mg once daily. While a 120 mg once daily dose was shown to be effective, there is no evidence that doses greater than 60 mg/day confer additional benefit. Nevertheless, if a decision is made to increase the dose beyond 60 mg once daily, increase dose in increments of 30 mg once daily. The safety of doses above 120 mg once daily has not been adequately evaluated. Periodically reassess to determine the continued need for maintenance treatment and the appropriate dose for such treatment [see Clinical Studies (14.2)].


    Pediatric use information for patients ages 7 to 17 years is approved for Eli Lilly and Company, Inc.'s duloxetine delayed-release capsules. However, due to Eli Lilly and Company, Inc.'s marketing exclusivity rights, this drug product is not labeled with that pediatric information.

    2.3 Dosage for Treatment of Diabetic Peripheral Neuropathic Pain

    Administer duloxetine delayed-release capsules 60 mg once daily. There is no evidence that doses higher than 60 mg confer additional significant benefit and the higher dose is clearly less well tolerated [see Clinical Studies (14.3)]. For patients for whom tolerability is a concern, a lower starting dose may be considered.


    Since diabetes is frequently complicated by renal disease, consider a lower starting dose and gradual increase in dose for patients with renal impairment [see Dosage and Administration (2.6), Use in Specific Populations (8.10), and Clinical Pharmacology (12.3)].

    2.5 Dosage for Treatment of Chronic Musculoskeletal Pain

    Administer duloxetine delayed-release capsules 60 mg once daily. Begin treatment at 30 mg for one week, to allow patients to adjust to the medication before increasing to 60 mg once daily. There is no evidence that higher doses confer additional benefit, even in patients who do not respond to a 60 mg dose, and higher doses are associated with a higher rate of adverse reactions [see Clinical Studies (14.5)].

    2.6 Dosing in Special Populations

    Hepatic Impairment — Avoid use in patients with chronic liver disease or cirrhosis [see Warnings and Precautions (5.14) and Use in Specific Populations (8.9)].


    Severe Renal Impairment — Avoid use in patients with severe renal impairment, GFR      <30 mL/min [see Warnings and Precautions (5.14)and Use in Specific Populations (8.10)].

    2.7 Discontinuing Duloxetine Delayed-Release Capsules

    Adverse reactions after discontinuation of duloxetine delayed-release capsules, after abrupt or tapered discontinuation, include: dizziness, headache, nausea, diarrhea, paresthesia, irritability, vomiting, insomnia, anxiety, hyperhidrosis, and fatigue. A gradual reduction in dosage rather than abrupt cessation is recommended whenever possible [see Warnings and Precautions (5.7)].

    2.8 Switching a Patient to or from a Monoamine Oxidase Inhibitor (MAOI) Intended to Treat Psychiatric Disorders

    At least 14 days should elapse between discontinuation of an MAOI intended to treat psychiatric disorders and initiation of therapy with duloxetine delayed-release capsules. Conversely, at least 5 days should be allowed after stopping duloxetine delayed-release capsules before starting an MAOI intended to treat psychiatric disorders [see Contraindications (4)].

    2.9 Use of Duloxetine Delayed-Release Capsules with Other MAOIs such as Linezolid or Methylene Blue

    Do not start duloxetine delayed-release capsules in a patient who is being treated with linezolid or intravenous methylene blue because there is an increased risk of serotonin syndrome. In a patient who requires more urgent treatment of a psychiatric condition, other interventions, including hospitalization, should be considered [see Contraindications (4)].


    In some cases, a patient already receiving duloxetine delayed-release capsules therapy may require urgent treatment with linezolid or intravenous methylene blue. If acceptable alternatives to linezolid or intravenous methylene blue treatment are not available and the potential benefits of linezolid or intravenous methylene blue treatment are judged to outweigh the risks of serotonin syndrome in a particular patient, duloxetine delayed-release capsules should be stopped promptly, and linezolid or intravenous methylene blue can be administered. The patient should be monitored for symptoms of serotonin syndrome for 5 days or until 24 hours after the last dose of linezolid or intravenous methylene blue, whichever comes first. Therapy with duloxetine delayed-release capsules may be resumed 24 hours after the last dose of linezolid or intravenous methylene blue [see Warnings and Precautions (5.4)].


    The risk of administering methylene blue by non-intravenous routes (such as oral tablets or by local injection) or in intravenous doses much lower than 1 mg/kg with duloxetine delayed-release capsules is unclear. The clinician should, nevertheless, be aware of the possibility of emergent symptoms of serotonin syndrome with such use [see Warnings and Precautions (5.4)].


  • Torsemide | Cardinal Health
    No Recall

    Torsemide | Cardinal Health

    Torsemide | Cardinal Health
    General

     Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

     The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide tablets. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

     The usual initial dose of torsemide is 20 mg of once-daily oral torsemide tablets. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

     The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide tablets, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

     The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Torsemide | Greenstone Llc
    No Recall

    Torsemide | Greenstone Llc

    Torsemide | Greenstone Llc

    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied. 

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied. 

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials. 

    Hypertension
     
    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Torsemide | American Regent, Inc.
    No Recall

    Torsemide | American Regent, Inc.

    Torsemide | American Regent, Inc.
    General

    Special dosage adjustment in the elderly is not necessary.

    Because of the high bioavailability of torsemide, oral and intravenous doses are therapeutically equivalent, so patients may be switched to and from the intravenous form with no change in dose.  Torsemide injection should be administered either slowly as a bolus over a period of 2 minutes or administered as a continuous infusion.

    If torsemide is administered through an IV line, it is recommended that, as with other IV injections, the IV line be flushed with Normal Saline (Sodium Chloride Injection) before and after administration.  Torsemide injection is formulated above pH 8.3. Flushing the line is recommended to avoid the potential for incompatibilities caused by differences in pH which could be indicated by color change, haziness or the formation of a precipitate in the solution.

    If torsemide injection is administered as a continuous infusion, stability has been demonstrated through 24 hours at room temperature in plastic containers for the following fluids and concentrations:

    200 mg torsemide (10 mg/mL) added to:
        250 mL Dextrose 5% in Water
        250 mL 0.9% Sodium Chloride
        500 mL 0.45% Sodium Chloride

    50 mg torsemide (10 mg/mL) added to:
        500 mL Dextrose 5% in Water
        500 mL 0.9% Sodium Chloride
        500 mL 0.45% Sodium Chloride

    Before administration, the solution of torsemide injection should be visually inspected for discoloration and particulate matter.  If either is found, the vial should not be used.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once daily intravenous torsemide.  If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained.  Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once daily intravenous torsemide.  If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained.  Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once daily intravenous torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic.  If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained.  Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily.  If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg daily.  If the response to 10 mg is insufficient, an additional anti-hypertensive agent should be added to the treatment regimen.

  • Torsemide | Carilion Materials Management
    No Recall

    Torsemide | Carilion Materials Management

    Torsemide | Carilion Materials Management

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary. The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied. The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied. The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied. Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials. The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.


    General


    Congestive Heart Failure


    Chronic Renal Failure


    Hepatic Cirrhosis


    Hypertension


  • Torsemide | Carilion Materials Management
    No Recall

    Torsemide | Carilion Materials Management

    Torsemide | Carilion Materials Management

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary. The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied. The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied. The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied. Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials. The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.


    General


    Congestive Heart Failure


    Chronic Renal Failure


    Hepatic Cirrhosis


    Hypertension


  • Torsemide | Cardinal Health
    No Recall

    Torsemide | Cardinal Health

    Torsemide | Cardinal Health
    General

     Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

     The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide tablets. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

     The usual initial dose of torsemide is 20 mg of once-daily oral torsemide tablets. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

     The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide tablets, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

     The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Torsemide | Avpak
    No Recall

    Torsemide | Avpak

    Torsemide | Avpak

    General
    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis
    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension

    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.

  • Citron Pharma Llc
    Torsemide | Citron Pharma Llc
    No Recall

    Torsemide | Citron Pharma Llc

    Torsemide | Citron Pharma Llc

    General

    Torsemide tablets may be given at any time in relation to a meal, as convenient. Special dosage adjustment in the elderly is not necessary.

    Congestive Heart Failure

    The usual initial dose is 10 mg or 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Chronic Renal Failure

    The usual initial dose of torsemide is 20 mg of once-daily oral torsemide. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 200 mg have not been adequately studied.

    Hepatic Cirrhosis

    The usual initial dose is 5 mg or 10 mg of once-daily oral torsemide, administered together with an aldosterone antagonist or a potassium-sparing diuretic. If the diuretic response is inadequate, the dose should be titrated upward by approximately doubling until the desired diuretic response is obtained. Single doses higher than 40 mg have not been adequately studied.

    Chronic use of any diuretic in hepatic disease has not been studied in adequate and well-controlled trials.

    Hypertension
     
    The usual initial dose is 5 mg once daily. If the 5 mg dose does not provide adequate reduction in blood pressure within 4 to 6 weeks, the dose may be increased to 10 mg once daily. If the response to 10 mg is insufficient, an additional antihypertensive agent should be added to the treatment regimen.