Glaxosmithkline Llc

Manufacturer Details

There are currently no manufacturer details available.

Share This Page

Glaxosmithkline Llc Drugs

  • Breo Ellipta (Fluticasone Furoate And Vilanterol Trifenatate) Powder [Glaxosmithkline Llc]

    Breo Ellipta

    Breo Ellipta (Fluticasone Furoate And Vilanterol Trifenatate) Powder [Glaxosmithkline Llc]

    BREO ELLIPTA should be administered once daily every day by the orally inhaled route only.

    BREO ELLIPTA should be taken at the same time every day. Do not use BREO ELLIPTA more than 1 time every 24 hours.

    After inhalation, the patient should rinse his/her mouth with water without swallowing to help reduce the risk of oropharyngeal candidiasis.

    More frequent administration or a greater number of inhalations (more than 1 inhalation daily) of the prescribed strength of BREO ELLIPTA is not recommended as some patients are more likely to experience adverse effects with higher doses. Patients using BREO ELLIPTA should not use additional LABA for any reason. [See Warnings and Precautions (5.3, 5.5, 5.8, 5.12).]

    2.1 Chronic Obstructive Pulmonary Disease

    BREO ELLIPTA 100/25 should be administered as 1 inhalation once daily. The maximum recommended dosage is 1 inhalation of BREO ELLIPTA 100/25 once daily, the only strength indicated for the treatment of COPD.

    If shortness of breath occurs in the period between doses, an inhaled, short-acting beta2-agonist (rescue medicine, e.g., albuterol) should be taken for immediate relief.

    2.2 Asthma

    If asthma symptoms arise in the period between doses, an inhaled, short-acting beta2-agonist (rescue medicine, e.g., albuterol) should be taken for immediate relief.

    The recommended starting dosage is BREO ELLIPTA 100/25 or BREO ELLIPTA 200/25 administered as 1 inhalation once daily. The maximum recommended dosage is 1 inhalation of BREO ELLIPTA 200/25 once daily.

    The starting dosage is based on patients’ asthma severity. For patients previously treated with low- to mid-dose corticosteroid–containing treatment, BREO ELLIPTA 100/25 should be considered. For patients previously treated with mid- to high-dose corticosteroid–containing treatment, BREO ELLIPTA 200/25 should be considered.

    The median time to onset, defined as a 100-mL increase from baseline in mean forced expiratory volume in 1 second (FEV1), was approximately 15 minutes after beginning treatment. Individual patients will experience a variable time to onset and degree of symptom relief.

    For patients who do not respond adequately to BREO ELLIPTA 100/25, increasing the dose to BREO ELLIPTA 200/25 may provide additional improvement in asthma control.

    If a previously effective dosage regimen of BREO ELLIPTA fails to provide adequate improvement in asthma control, the therapeutic regimen should be reevaluated and additional therapeutic options (e.g., replacing the current strength of BREO ELLIPTA with a higher strength, adding additional inhaled corticosteroid, initiating oral corticosteroids) should be considered.

  • Dutasteride Capsule, Liquid Filled [Glaxosmithkline Llc]

    Dutasteride

    Dutasteride Capsule, Liquid Filled [Glaxosmithkline Llc]

    There is currently no dosage information available for this product. We apologize for any inconvenience.

  • Methylphenidate Hydrochloride Tablet [Qualitest Pharmaceuticals]

    Methylphenidate Hydrochloride

    Methylphenidate Hydrochloride Tablet [Qualitest Pharmaceuticals]

    Adults and Children 12 Years of Age and Older:

    The usual dosage is 1 or 2 nasal inhalations (42 to 84 mcg) in each nostril twice a day (total dose, 168 to 336 mcg/day).

    Children 6 to 12 Years of Age:

    Patients should be started with 1 nasal inhalation in each nostril twice daily; patients not adequately responding to 168 mcg or those with more severe symptoms may use 336 mcg (2 inhalations in each nostril). Once adequate control is achieved, the dosage should be decreased to 84 mcg (1 spray in each nostril) twice daily. BECONASE AQ Nasal Spray is not recommended for children below 6 years of age.

    The maximum total daily dosage should not exceed 2 sprays in each nostril twice daily (336 mcg/day).

    In patients who respond to BECONASE AQ Nasal Spray, an improvement of the symptoms of seasonal or perennial rhinitis usually becomes apparent within a few days after the start of therapy with BECONASE AQ Nasal Spray. However, symptomatic relief may not occur in some patients for as long as 2 weeks. BECONASE AQ Nasal Spray should not be continued beyond 3 weeks in the absence of significant symptomatic improvement.

    The therapeutic effects of corticosteroids, unlike those of decongestants, are not immediate. This should be explained to the patient in advance in order to ensure cooperation and continuation of treatment with the prescribed dosage regimen.

    In the presence of excessive nasal mucous secretion or edema of the nasal mucosa, the drug may fail to reach the site of intended action. In such cases it is advisable to use a nasal vasoconstrictor during the first 2 to 3 days of therapy with BECONASE AQ Nasal Spray.

    Directions for Use:

    Illustrated Patient’s Instructions for Use accompany each package of BECONASE AQ Nasal Spray.

  • Methylphenidate Hydrochloride Solution [Tris Pharma, Inc.]

    Methylphenidate Hydrochloride Solution

    Methylphenidate Hydrochloride Solution [Tris Pharma, Inc.]

    • For Intranasal Use Only. • Apply approximately one-half of the ointment from the single-use tube into 1 nostril and the other half into the other nostril twice daily (morning and evening) for 5 days. • After application, close the nostrils by pressing together and releasing the sides of the nose repetitively for approximately 1 minute. This will spread the ointment throughout the nares. • Do not apply BACTROBAN nasal ointment concurrently with any other intranasal products [see Clinical Pharmacology (12.3)]. • The single-use 1-gram tube will deliver a total of approximately 0.5 grams of the ointment (approximately 0.25 grams per nostril). • Discard the tube after usage. Do not re-use.

  • Epivir (Lamivudine) Tablet, Film Coated Epivir (Lamivudine) Solution [Glaxosmithkline Llc]

    Epivir

    Epivir (Lamivudine) Tablet, Film Coated Epivir (Lamivudine) Solution [Glaxosmithkline Llc]

    2.1 Adults and Adolescents >16 years of age

    The recommended oral dose of EPIVIR in HIV-1-infected adults and adolescents >16 years of age is 300 mg daily, administered as either 150 mg twice daily or 300 mg once daily, in combination with other antiretroviral agents. If lamivudine is administered to a patient infected with HIV-1 and HBV, the dosage indicated for HIV-1 therapy should be used as part of an appropriate combination regimen [see Warnings and Precautions (5.2)].

    2.2 Pediatric Patients

    The recommended oral dose of EPIVIR Oral Solution in HIV-1-infected pediatric patients 3 months to 16 years of age is 4 mg/kg twice daily (up to a maximum of 150 mg twice a day), administered in combination with other antiretroviral agents.

    EPIVIR is also available as a scored tablet for HIV-1-infected pediatric patients who weigh ≥14 kg and for whom a solid dosage form is appropriate. Before prescribing EPIVIR Tablets, children should be assessed for the ability to swallow tablets. If a child is unable to reliably swallow EPIVIR Tablets, the oral solution formulation should be prescribed. The recommended oral dosage of EPIVIR Tablets for HIV-1-infected pediatric patients is presented in Table 1.

    Table 1. Dosing Recommendations for EPIVIR Tablets in Pediatric Patients

    Weight

    (kg) Dosage Regimen Using Scored 150-mg Tablet

    Total Daily Dose

    AM Dose PM Dose 14 to 21 ½ tablet (75 mg) ½ tablet (75 mg) 150 mg >21 to <30 ½ tablet (75 mg) 1 tablet (150 mg) 225 mg ≥30 1 tablet (150 mg) 1 tablet (150 mg) 300 mg

    2.3 Patients With Renal Impairment

    Dosing of EPIVIR is adjusted in accordance with renal function. Dosage adjustments are listed in Table 2 [see Clinical Pharmacology (12.3)].

    Table 2. Adjustment of Dosage of EPIVIR in Adults and Adolescents (≥30 kg) in Accordance With Creatinine Clearance Creatinine Clearance (mL/min) Recommended Dosage of EPIVIR ≥50        150 mg twice daily or 300 mg once daily 30-49        150 mg once daily 15-29        150 mg first dose, then 100 mg once daily 5-14        150 mg first dose, then 50 mg once daily <5          50 mg first dose, then 25 mg once daily

    No additional dosing of EPIVIR is required after routine (4-hour) hemodialysis or peritoneal dialysis.

    Although there are insufficient data to recommend a specific dose adjustment of EPIVIR in pediatric patients with renal impairment, a reduction in the dose and/or an increase in the dosing interval should be considered.

  • Mepron (Atovaquone) Suspension [Glaxosmithkline Llc]

    Mepron

    Mepron (Atovaquone) Suspension [Glaxosmithkline Llc]

    2.1 Dosing Information

    The initial dosage should be 100 mg 3 times daily (300 mg per day). The dosage should be increased gradually at weekly intervals by no more than 50 mg 3 times daily (increase in the daily dose of no more than 150 mg per day) up to a maintenance dosage of 200 mg to 400 mg 3 times daily (600 mg to 1,200 mg per day), based on individual patient response and tolerability. This information is summarized in Table 1 under Dosing in Specific Populations. In the controlled clinical trials, 400 mg 3 times daily showed limited evidence of additional improvement in seizure reduction, but an increase in adverse events and discontinuations, compared with the 300 mg 3 times daily dosage. The safety and efficacy of dosages greater than 400 mg 3 times daily (1,200 mg per day) have not been examined in controlled trials.

    POTIGA should be given orally in 3 equally divided doses daily, with or without food.

    POTIGA tablets should be swallowed whole.

    If POTIGA is discontinued, the dosage should be gradually reduced over a period of at least 3 weeks, unless safety concerns require abrupt withdrawal.

    2.2. Dosing Considerations to Mitigate the Risk of Visual Adverse Reactions

    Because POTIGA may cause retinal abnormalities with long-term use, patients who fail to show substantial clinical benefit after adequate titration should be discontinued from POTIGA. Testing of visual function should be done at baseline and every 6 months during therapy with POTIGA. Patients who cannot be monitored should usually not be treated with POTIGA. If retinal pigmentary abnormalities or vision changes are detected, POTIGA should be discontinued unless no other suitable treatment options are available and the benefits of treatment outweigh the potential risk of vision loss [see Warnings and Precautions (5.1)].

    2.3 Dosing in Specific Populations

    No adjustment in dosage is recommended in patients with mild renal or hepatic impairment (see Table 1). Dosage adjustment is recommended in geriatric and patients with moderate or severe renal or hepatic impairment (see Table 1).

    Table 1. Dosing in Specific Populations

    Specific Population

    Initial Dose

    Titration

    Maximum Dosage

    General Dosing

    General population (including patients with mild renal or hepatic impairment)

    100 mg 3 times daily

    (300 mg per day)

    Increase by no more than 50 mg 3 times daily, at weekly intervals

    400 mg 3 times daily

    (1,200 mg per day)

    Dosing in Specific Populations

    Geriatrics

    (patients ≥65 years)

    50 mg 3 times daily

    (150 mg per day)

    Increase by no more than 50 mg 3 times daily, at weekly intervals

    250 mg 3 times daily

    (750 mg per day)

    Hepatic impairment

    (patients with Child-Pugh 7-9)

    250 mg 3 times daily

    (750 mg per day)

    Hepatic impairment

    (patients with Child-Pugh >9)

    200 mg 3 times daily

    (600 mg per day)

    Renal impairment

    (patients with CrCL <50 mL per min or end-stage renal disease on dialysis)

    200 mg 3 times daily

    (600 mg per day)

  • Lanoxin
    Lanoxin (Digoxin) Tablet [Glaxosmithkline Llc]

    Lanoxin

    Lanoxin (Digoxin) Tablet [Glaxosmithkline Llc]

    General

    Recommended dosages of digoxin may require considerable modification because of individual sensitivity of the patient to the drug, the presence of associated conditions, or the use of concurrent medications. In selecting a dose of digoxin, the following factors must be considered:

    1. The body weight of the patient. Doses should be calculated based upon lean (i.e., ideal) body weight. 2. The patient’s renal function, preferably evaluated on the basis of estimated creatinine clearance. 3. The patient’s age. Infants and children require different doses of digoxin than adults. Also, advanced age may be indicative of diminished renal function even in patients with normal serum creatinine concentration (i.e., below 1.5 mg/dL). 4. Concomitant disease states, concurrent medications, or other factors likely to alter the pharmacokinetic or pharmacodynamic profile of digoxin (see PRECAUTIONS).

    Serum Digoxin Concentrations

    In general, the dose of digoxin used should be determined on clinical grounds. However, measurement of serum digoxin concentrations can be helpful to the clinician in determining the adequacy of digoxin therapy and in assigning certain probabilities to the likelihood of digoxin intoxication. About two-thirds of adults considered adequately digitalized (without evidence of toxicity) have serum digoxin concentrations ranging from 0.8 to 2.0 ng/mL (lower serum trough concentrations of 0.5 to 1 ng/mL may be appropriate in some adult patients, see Maintenance Dosing). However, digoxin may produce clinical benefits even at serum concentrations below this range. About two-thirds of adult patients with clinical toxicity have serum digoxin concentrations greater than 2.0 ng/mL. However, since one-third of patients with clinical toxicity have concentrations less than 2.0 ng/mL, values below 2.0 ng/mL do not rule out the possibility that a certain sign or symptom is related to digoxin therapy. Rarely, there are patients who are unable to tolerate digoxin at serum concentrations below 0.8 ng/mL. Consequently, the serum concentration of digoxin should always be interpreted in the overall clinical context, and an isolated measurement should not be used alone as the basis for increasing or decreasing the dose of the drug.

    To allow adequate time for equilibration of digoxin between serum and tissue, sampling of serum concentrations should be done just before the next scheduled dose of the drug. If this is not possible, sampling should be done at least 6 to 8 hours after the last dose, regardless of the route of administration or the formulation used. On a once-daily dosing schedule, the concentration of digoxin will be 10% to 25% lower when sampled at 24 versus 8 hours, depending upon the patient’s renal function. On a twice-daily dosing schedule, there will be only minor differences in serum digoxin concentrations whether sampling is done at 8 or 12 hours after a dose.

    If a discrepancy exists between the reported serum concentration and the observed clinical response, the clinician should consider the following possibilities:

    1. Analytical problems in the assay procedure. 2. Inappropriate serum sampling time. 3. Administration of a digitalis glycoside other than digoxin. 4. Conditions (described in WARNINGS and PRECAUTIONS) causing an alteration in the sensitivity of the patient to digoxin. 5. Serum digoxin concentration may decrease acutely during periods of exercise without any associated change in clinical efficacy due to increased binding of digoxin to skeletal muscle.

    Heart Failure

    Adults

    Digitalization may be accomplished by either of 2 general approaches that vary in dosage and frequency of administration, but reach the same endpoint in terms of total amount of digoxin accumulated in the body.

    1. If rapid digitalization is considered medically appropriate, it may be achieved by administering a loading dose based upon projected peak digoxin body stores. Maintenance dose can be calculated as a percentage of the loading dose. 2. More gradual digitalization may be obtained by beginning an appropriate maintenance dose, thus allowing digoxin body stores to accumulate slowly. Steady-state serum digoxin concentrations will be achieved in approximately 5 half-lives of the drug for the individual patient. Depending upon the patient’s renal function, this will take between 1 and 3 weeks.

    Rapid Digitalization With a Loading Dose

    Peak digoxin body stores of 8 to 12 mcg/kg should provide therapeutic effect with minimum risk of toxicity in most patients with heart failure and normal sinus rhythm. Because of altered digoxin distribution and elimination, projected peak body stores for patients with renal insufficiency should be conservative (i.e., 6 to 10 mcg/kg) (see PRECAUTIONS).

    The loading dose should be administered in several portions, with roughly half the total given as the first dose. Additional fractions of this planned total dose may be given at 6- to 8-hour intervals, with careful assessment of clinical response before each additional dose.

    If the patient’s clinical response necessitates a change from the calculated loading dose of digoxin, then calculation of the maintenance dose should be based upon the amount actually given.

    A single initial dose of 500 to 750 mcg (0.5 to 0.75 mg) of LANOXIN Tablets usually produces a detectable effect in 0.5 to 2 hours that becomes maximal in 2 to 6 hours. Additional doses of 125 to 375 mcg (0.125 to 0.375 mg) may be given cautiously at 6- to 8-hour intervals until clinical evidence of an adequate effect is noted. The usual amount of LANOXIN Tablets that a 70-kg patient requires to achieve 8 to 12 mcg/kg peak body stores is 750 to 1,250 mcg (0.75 to 1.25 mg).

    LANOXIN Injection is frequently used to achieve rapid digitalization, with conversion to LANOXIN Tablets for maintenance therapy. If patients are switched from intravenous to oral digoxin formulations, allowances must be made for differences in bioavailability when calculating maintenance dosages (see Table 1, CLINICAL PHARMACOLOGY).

    Maintenance Dosing

    The doses of digoxin used in controlled trials in patients with heart failure have ranged from 125 to 500 mcg (0.125 to 0.5 mg) once daily. In these studies, the digoxin dose has been generally titrated according to the patient’s age, lean body weight, and renal function. Therapy is generally initiated at a dose of 250 mcg (0.25 mg) once daily in patients under age 70 with good renal function, at a dose of 125 mcg (0.125 mg) once daily in patients over age 70 or with impaired renal function, and at a dose of 62.5 mcg (0.0625 mg) in patients with marked renal impairment. Doses may be increased every 2 weeks according to clinical response.

    In a subset of approximately 1,800 patients enrolled in the DIG trial (wherein dosing was based on an algorithm similar to that in Table 5) the mean (± SD) serum digoxin concentrations at 1 month and 12 months were 1.01 ± 0.47 ng/mL and 0.97 ± 0.43 ng/mL, respectively. There are no rigid guidelines as to the range of serum concentrations that are most efficacious. Several post hoc analyses of heart failure patients in the DIG trial suggest that the optimal trough digoxin serum level may be 0.5 ng/mL to 1 ng/mL.

    The maintenance dose should be based upon the percentage of the peak body stores lost each day through elimination. The following formula has had wide clinical use:

    Maintenance Dose = Peak Body Stores (i.e., Loading Dose) x % Daily Loss/100

    Where: % Daily Loss = 14 + Ccr/5

    (Ccr is creatinine clearance, corrected to 70 kg body weight or 1.73 m2 body surface area.)

    Table 5 provides average daily maintenance dose requirements of LANOXIN Tablets for patients with heart failure based upon lean body weight and renal function:

    Table 5. Usual Daily Maintenance Dose Requirements (mcg) of LANOXIN for Estimated Peak Body Stores of 10 mcg/kg

    Corrected Ccr

    (mL/min per 70 kg)a

    Lean Body Weight

    Number of Days

    kg

    50

    60

    70

    80

    90

    100

    Before Steady

    lb

    110

    132

    154

    176

    198

    220

    State Achievedb

    0

    62.5c

    125

    125

    125

    187.5

    187.5

    22

    10

    125

    125

    125

    187.5

    187.5

    187.5

    19

    20

    125

    125

    187.5

    187.5

    187.5

    250

    16

    30

    125

    187.5

    187.5

    187.5

    250

    250

    14

    40

    125

    187.5

    187.5

    250

    250

    250

    13

    50

    187.5

    187.5

    250

    250

    250

    250

    12

    60

    187.5

    187.5

    250

    250

    250

    375

    11

    70

    187.5

    250

    250

    250

    250

    375

    10

    80

    187.5

    250

    250

    250

    375

    375

    9

    90

    187.5

    250

    250

    250

    375

    500

    8

    100

    250

    250

    250

    375

    375

    500

    7

    a Ccr is creatinine clearance, corrected to 70 kg body weight or 1.73 m2 body surface area. For adults, if only serum creatinine concentrations (Scr) are available, a Ccr (corrected to 70 kg body weight) may be estimated in men as (140 - Age)/Scr. For women, this result should be multiplied by 0.85. Note: This equation cannot be used for estimating creatinine clearance in infants or children.

    b If no loading dose administered.

    c 62.5 mcg = 0.0625 mg.

    Example: Based on Table 5, a patient in heart failure with an estimated lean body weight of 70 kg and a Ccr of 60 mL/min should be given a dose of 250 mcg (0.25 mg) daily of LANOXIN Tablets, usually taken after the morning meal. If no loading dose is administered, steady-state serum concentrations in this patient should be anticipated at approximately 11 days.

    Infants and Children

    In general, divided daily dosing is recommended for infants and young children (under age 10). In the newborn period, renal clearance of digoxin is diminished and suitable dosage adjustments must be observed. This is especially pronounced in the premature infant. Beyond the immediate newborn period, children generally require proportionally larger doses than adults on the basis of body weight or body surface area. Children over 10 years of age require adult dosages in proportion to their body weight. Some researchers have suggested that infants and young children tolerate slightly higher serum concentrations than do adults.

    Daily maintenance doses for each age group are given in Table 6 and should provide therapeutic effects with minimum risk of toxicity in most patients with heart failure and normal sinus rhythm. These recommendations assume the presence of normal renal function:

    Table 6. Daily Maintenance Doses in Children With Normal Renal Function

    Age

    Daily Maintenance Dose (mcg/kg)

    2 to 5 Years

    10 to 15

    5 to 10 Years

    7 to 10

    Over 10 Years

    3 to 5

    In children with renal disease, digoxin must be carefully titrated based upon clinical response.

    It cannot be overemphasized that both the adult and pediatric dosage guidelines provided are based upon average patient response and substantial individual variation can be expected. Accordingly, ultimate dosage selection must be based upon clinical assessment of the patient.

    Atrial Fibrillation

    Peak digoxin body stores larger than the 8 to 12 mcg/kg required for most patients with heart failure and normal sinus rhythm have been used for control of ventricular rate in patients with atrial fibrillation. Doses of digoxin used for the treatment of chronic atrial fibrillation should be titrated to the minimum dose that achieves the desired ventricular rate control without causing undesirable side effects. Data are not available to establish the appropriate resting or exercise target rates that should be achieved.

    Dosage Adjustment When Changing Preparations

    The difference in bioavailability between LANOXIN Injection or LANOXIN Tablets must be considered when changing patients from one dosage form to the other.

  • Horizant
    Horizant (Gabapentin Enacarbil) Tablet, Extended Release [Glaxosmithkline Llc]

    Horizant

    Horizant (Gabapentin Enacarbil) Tablet, Extended Release [Glaxosmithkline Llc]

    Tablets should be swallowed whole and should not be cut, crushed, or chewed.

    Tablets should be taken with food.

    HORIZANT is not interchangeable with other gabapentin products because of differing pharmacokinetic profiles [see Warnings and Precautions (5.3)].

    2.1 Restless Legs Syndrome

    The recommended dosage for HORIZANT is 600 mg once daily at about 5 PM. A daily dose of 1,200 mg provided no additional benefit compared with the 600-mg dose, but caused an increase in adverse reactions [see Adverse Reactions (6.1)].

    If the dose is not taken at the recommended time, the next dose should be taken the following day as prescribed.

    2.2 Postherpetic Neuralgia

    The recommended dosage of HORIZANT is 600 mg twice daily. HORIZANT should be initiated at a dose of 600 mg in the morning for 3 days of therapy, then increased to 600 mg twice daily (1,200 mg/day) on day four. In the 12-week principal efficacy study, additional benefit of using doses greater than 1,200 mg a day was not demonstrated, and these higher doses resulted in an increase in adverse reactions [see Adverse Reactions (6.1)].

    If the dose is not taken at the recommended time, skip this dose, and the next dose should be taken at the time of the next scheduled dose.

    2.3 Renal Impairment

    Dosing of HORIZANT is adjusted in accordance with renal function, as represented by creatinine clearance [see Clinical Pharmacology (12.3)]. Target dose regimens are listed in Table 1 and Table 2.

    Table 1. Dosage of HORIZANT for Patients With Restless Legs Syndrome in Accordance With Creatinine Clearance

    Creatinine Clearance (mL/min)

    Target Dose Regimen

    ≥60

    600 mg per day

    30 - 59

    Start at 300 mg per day and increase to 600 mg as needed

    15 - 29

    300 mg per day

    <15

    300 mg every other day

    <15 on hemodialysis

    Not recommended

    Table 2. Dosage of HORIZANT for Patients With Postherpetic Neuralgia in Accordance With Creatinine Clearance

    Creatinine Clearance (mL/min)

    Titration

    Maintenance

    Tapering

    ≥60

    600 mg in AM for 3 days

    600 mg twice daily

    600 mg in AM for

    1 week

    30 - 59

    300 mg in AM for 3 days

    300 mg twice daily. Increase to 600 mg twice daily as neededa

    Reduce current maintenance dose to once daily in AM for 1 week

    15 - 29

    300 mg in AM on Day 1 and Day 3

    300 mg in AM. Increase to 300 mg twice daily if neededa

    If taking 300 mg twice daily, reduce to 300 mg once daily in AM for 1 week.

    If taking 300 mg once daily, no taper needed.

    <15

    None

    300 mg every other day in AM. Increase to 300 mg once daily in AM if neededa

    None

    <15 on hemodialysis

    None

    300 mg following every dialysis. Increase to 600 mg following every dialysis if neededa

    None

    aBased on tolerability and efficacy

    In patients with stable renal function, CrCl can be estimated using the equation of Cockcroft and Gault:

    for males: CrCl = (140-age)(weight)/[(72)(SCr)]

    for females: CrCl = (0.85)(140-age)(weight)/[(72)(SCr)]

    where age is in years, weight is in kilograms, and SCr is serum creatinine in mg/dL.

  • Tabloid
    Tabloid (Thioguanine) Tablet [Glaxosmithkline Llc]

    Tabloid

    Tabloid (Thioguanine) Tablet [Glaxosmithkline Llc]

     TABLOID brand Thioguanine is administered orally. The dosage which will be tolerated and effective varies according to the stage and type of neoplastic process being treated. Because the usual therapies for adult and pediatric acute nonlymphocytic leukemias involve the use of thioguanine with other agents in combination, physicians responsible for administering these therapies should be experienced in the use of cancer chemotherapy and in the chosen protocol.

    There are individuals with an inherited deficiency of the enzyme thiopurine methyltransferase (TPMT) who may be unusually sensitive to the myelosuppressive effects of thioguanine and prone to developing rapid bone marrow suppression following the initiation of treatment. Substantial dosage reductions may be required to avoid the development of life-threatening bone marrow suppression in these patients (see WARNINGS). Prescribers should be aware that some laboratories offer testing for TPMT deficiency.

    Ninety-six (59%) of 163 pediatric patients with previously untreated acute nonlymphocytic leukemia obtained complete remission with a multiple-drug protocol including thioguanine, prednisone, cytarabine, cyclophosphamide, and vincristine. Remission was maintained with daily thioguanine, 4-day pulses of cytarabine and cyclophosphamide, and a single dose of vincristine every 28 days. The median duration of remission was 11.5 months.

    Fifty-three percent of previously untreated adults with acute nonlymphocytic leukemias attained remission following use of the combination of thioguanine and cytarabine according to a protocol developed at The Memorial Sloan-Kettering Cancer Center. A median duration of remission of 8.8 months was achieved with the multiple-drug maintenance regimen which included thioguanine.

    On those occasions when single-agent chemotherapy with thioguanine may be appropriate, the usual initial dosage for pediatric patients and adults is approximately 2 mg/kg of body weight per day. If, after 4 weeks on this dosage, there is no clinical improvement and no leukocyte or platelet depression, the dosage may be cautiously increased to 3 mg/kg/day. The total daily dose may be given at one time.

    The dosage of thioguanine used does not depend on whether or not the patient is receiving ZYLOPRIM (allopurinol); this is in contradistinction to the dosage reduction which is mandatory when PURINETHOL (mercaptopurine) or IMURAN (azathioprine) is given simultaneously with allopurinol.

    Procedures for proper handling and disposal of anticancer drugs should be considered. Several guidelines on this subject have been published.1-8

    There is no general agreement that all of the procedures recommended in the guidelines are necessary or appropriate.

  • Zolpidem Tartrate Tablet, Film Coated [Teva Pharmaceuticals Usa Inc]

    Zolpidem Tartrate

    Zolpidem Tartrate Tablet, Film Coated [Teva Pharmaceuticals Usa Inc]

    2.1 Recommended Dosage

    This product is for intravenous use only.

    The recommended duration of treatment for adult and pediatric patients has not been clearly established. In clinical trials, treatment was generally continued until there was evidence of disease progression, the patient experienced unacceptable toxicity, the patient became a candidate for bone marrow transplant, or the patient no longer continued to benefit from treatment.

    Adult Dosage: The recommended adult dose of ARRANON is 1,500 mg/m² administered intravenously over 2 hours on Days 1, 3, and 5 repeated every 21 days. ARRANON is administered undiluted.

    Pediatric Dosage: The recommended pediatric dose of ARRANON is 650 mg/m² administered intravenously over 1 hour daily for 5 consecutive days repeated every 21 days. ARRANON is administered undiluted.

    2.2 Dosage Modification

    Administration of ARRANON should be discontinued for neurologic adverse reactions of NCI Common Toxicity Criteria Grade 2 or greater. Dosage may be delayed for other toxicity including hematologic toxicity. [See Boxed Warning, Warnings and Precautions (5.1, 5.2).]

    2.3 Adjustment of Dose in Special Populations

    ARRANON has not been studied in patients with renal or hepatic dysfunction [see Use in Specific Populations (8.6, 8.7)]. No dose adjustment is recommended for patients with a creatinine clearance (CLcr) ≥50 mL/min [see Clinical Pharmacology (12.3)]. There are insufficient data to support a dose recommendation for patients with a CLcr <50 mL/min.

    2.4 Prevention of Hyperuricemia

    Appropriate measures (e.g., hydration, urine alkalinization, and prophylaxis with allopurinol) must be taken to prevent hyperuricemia [see Warnings and Precautions (5.4)].

    2.5 Instructions for Handling, Preparation, and Administration

    Handling: ARRANON is a cytotoxic agent. Caution should be used during handling and preparation. Use of gloves and other protective clothing to prevent skin contact is recommended. Proper aseptic technique should be used. Guidelines for proper handling and disposal of anticancer drugs have been published.1-4

    Preparation and Administration: Do not dilute ARRANON prior to administration. The appropriate dose of ARRANON is transferred into polyvinylchloride (PVC) infusion bags or glass containers and administered as a 2-hour infusion in adult patients and as a 1-hour infusion in pediatric patients.

    Prior to administration, inspect the drug product visually for particulate matter and discoloration.

    Stability: ARRANON Injection is stable in polyvinylchloride (PVC) infusion bags and glass containers for up to 8 hours at up to 30° C.

  • Ventolin Hfa (Albuterol Sulfate) Aerosol, Metered [Glaxosmithkline Llc]

    Ventolin Hfa

    Ventolin Hfa (Albuterol Sulfate) Aerosol, Metered [Glaxosmithkline Llc]

    2.1 Bronchospasm

    For treatment of acute episodes of bronchospasm or prevention of symptoms associated with bronchospasm, the usual dosage for adults and children is 2 inhalations repeated every 4 to 6 hours; in some patients, 1 inhalation every 4 hours may be sufficient. More frequent administration or a greater number of inhalations is not recommended.

    2.2 Exercise-Induced Bronchospasm

    For prevention of exercise-induced bronchospasm, the usual dosage for adults and children aged 4 years and older is 2 inhalations 15 to 30 minutes before exercise.

    2.3 Administration Information

    VENTOLIN HFA should be administered by the orally inhaled route only.

    Priming: Priming VENTOLIN HFA is essential to ensure appropriate albuterol content in each actuation. Prime VENTOLIN HFA before using for the first time, when the inhaler has not been used for more than 2 weeks, or when the inhaler has been dropped. To prime VENTOLIN HFA, release 4 sprays into the air away from the face, shaking well before each spray.

    Cleaning: To ensure proper dosing and to prevent actuator orifice blockage, wash the actuator with warm water and let it air-dry completely at least once a week.

  • Act Anticavity Fluoride Kids Bubblegum (Sodium Fluoride) Rinse [Chattem, Inc.]

    Act Anticavity Fluoride Kids Bubblegum

    Act Anticavity Fluoride Kids Bubblegum (Sodium Fluoride) Rinse [Chattem, Inc.]

    AVANDIA may be administered at a starting dose of 4 mg either as a single daily dose or in 2 divided doses. For patients who respond inadequately following 8 to 12 weeks of treatment, as determined by reduction in fasting plasma glucose (FPG), the dose may be increased to 8 mg daily. Increases in the dose of AVANDIA should be accompanied by careful monitoring for adverse events related to fluid retention [see Boxed Warning, Warnings and Precautions (5.1)]. AVANDIA may be taken with or without food.

    The total daily dose of AVANDIA should not exceed 8 mg.

    Patients receiving AVANDIA in combination with other hypoglycemic agents may be at risk for hypoglycemia, and a reduction in the dose of the concomitant agent may be necessary.

    2.1 Specific Patient Populations

    Renal Impairment: No dosage adjustment is necessary when AVANDIA is used as monotherapy in patients with renal impairment. Since metformin is contraindicated in such patients, concomitant administration of metformin and AVANDIA is also contraindicated in patients with renal impairment.

    Hepatic Impairment: Liver enzymes should be measured prior to initiating treatment with AVANDIA. Therapy with AVANDIA should not be initiated if the patient exhibits clinical evidence of active liver disease or increased serum transaminase levels (ALT >2.5X upper limit of normal at start of therapy). After initiation of AVANDIA, liver enzymes should be monitored periodically per the clinical judgment of the healthcare professional. [See Warnings and Precautions (5.5), Clinical Pharmacology (12.3).]

    Pediatric: Data are insufficient to recommend pediatric use of AVANDIA [see Use in Specific Populations (8.4)].

  • Bupivacaine Hydrochloride Injection, Solution Bupivacaine Hydrochloride And Epinephrine (Bupivacaine Hydrochloride And Epinephrine Bitartrate) Injection, Solution [Hospira, Inc.]

    Bupivacaine Hydrochloride

    Bupivacaine Hydrochloride Injection, Solution Bupivacaine Hydrochloride And Epinephrine (Bupivacaine Hydrochloride And Epinephrine Bitartrate) Injection, Solution [Hospira, Inc.]

    SEREVENT DISKUS should be administered by the orally inhaled route only.

    More frequent administration or a greater number of inhalations (more than 1 inhalation twice daily) is not recommended as some patients are more likely to experience adverse effects. Patients using SEREVENT DISKUS should not use additional LABA for any reason. [See Warnings and Precautions (5.4, 5.6).]

    2.1 Asthma

    LABA, such as salmeterol, the active ingredient in SEREVENT DISKUS, increase the risk of asthma-related death [see Warnings and Precautions (5.1)].

    Because of this risk, use of SEREVENT DISKUS for the treatment of asthma without concomitant use of a long-term asthma control medication, such as an inhaled corticosteroid is contraindicated. Use SEREVENT DISKUS only as additional therapy for patients with asthma who are currently taking but are inadequately controlled on a long-term asthma control medication, such as an inhaled corticosteroid. Once asthma control is achieved and maintained, assess the patient at regular intervals and step down therapy (e.g., discontinue SEREVENT DISKUS) if possible without loss of asthma control and maintain the patient on a long-term asthma control medication, such as an inhaled corticosteroid. Do not use SEREVENT DISKUS for patients whose asthma is adequately controlled on low- or medium-dose inhaled corticosteroids.

    Pediatric and Adolescent Patients: Available data from controlled clinical trials suggest that LABA increase the risk of asthma-related hospitalization in pediatric and adolescent patients. For patients with asthma younger than 18 years who require addition of a LABA to an inhaled corticosteroid, a fixed-dose combination product containing both an inhaled corticosteroid and a LABA should ordinarily be used to ensure adherence with both drugs. In cases where use of a separate long-term asthma control medication (e.g., inhaled corticosteroid) and a LABA is clinically indicated, appropriate steps must be taken to ensure adherence with both treatment components. If adherence cannot be assured, a fixed-dose combination product containing both an inhaled corticosteroid and a LABA is recommended.

    For bronchodilatation and prevention of symptoms of asthma, including the symptoms of nocturnal asthma, the usual dosage for adults and children aged 4 years and older is 1 inhalation (50 mcg) twice daily, approximately 12 hours apart. If a previously effective dosage regimen fails to provide the usual response, medical advice should be sought immediately as this is often a sign of destabilization of asthma. Under these circumstances, the therapeutic regimen should be reevaluated. If symptoms arise in the period between doses, an inhaled, short-acting beta2-agonist should be taken for immediate relief.

    2.2 Exercise-Induced Bronchospasm

    Use of SEREVENT DISKUS as a single agent for the prevention of EIB may be clinically indicated in patients who do not have persistent asthma. In patients with persistent asthma, use of SEREVENT DISKUS for the prevention of EIB may be clinically indicated, but the treatment of asthma should include a long-term asthma control medication, such as an inhaled corticosteroid. One inhalation of SEREVENT DISKUS at least 30 minutes before exercise has been shown to protect patients against EIB. When used intermittently as needed for prevention of EIB, this protection may last up to 9 hours in adults and adolescents and up to 12 hours in patients aged 4 to 11 years. Additional doses of SEREVENT should not be used for 12 hours after the administration of this drug. Patients who are receiving SEREVENT DISKUS twice daily should not use additional SEREVENT for prevention of EIB.

    2.3 Chronic Obstructive Pulmonary Disease

    For maintenance treatment of bronchospasm associated with COPD (including chronic bronchitis and emphysema), the dosage for adults is 1 inhalation (50 mcg) twice daily approximately 12 hours apart.

  • Oxycodone And Acetaminophen Tablet [Amneal Pharmaceuticals, Llc]

    Oxycodone And Acetaminophen

    Oxycodone And Acetaminophen Tablet [Amneal Pharmaceuticals, Llc]

    2.1 Dosing Information

    The recommended dose of IMITREX Tablets is 25 mg, 50 mg, or 100 mg. Doses of 50 mg and 100 mg may provide a greater effect than the 25-mg dose, but doses of 100 mg may not provide a greater effect than the 50-mg dose. Higher doses may have a greater risk of adverse reactions [see Clinical Studies (14)].

    If the migraine has not resolved by 2 hours after taking IMITREX Tablets, or returns after a transient improvement, a second dose may be administered at least 2 hours after the first dose. The maximum daily dose is 200 mg in a 24-hour period.

    Use after IMITREX Injection: If the migraine returns following an initial treatment with IMITREX (sumatriptan succinate) Injection, additional single IMITREX Tablets (up to 100 mg/day) may be given with an interval of at least 2 hours between tablet doses.

    The safety of treating an average of more than 4 headaches in a 30-day period has not been established.

    2.2 Dosing in Patients With Hepatic Impairment

    If treatment is deemed advisable in the presence of mild to moderate hepatic impairment, the maximum single dose should not exceed 50 mg [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3)].

  • Flonase
    Flonase (Fluticasone Propionate) Spray, Metered [Glaxosmithkline Llc]

    Flonase

    Flonase (Fluticasone Propionate) Spray, Metered [Glaxosmithkline Llc]

    Administer FLONASE Nasal Spray by the intranasal route only. Prime FLONASE Nasal Spray before using for the first time or after a period of non-use (1 week or more) by shaking the contents well and releasing 6 sprays into the air away from the face. Shake FLONASE Nasal Spray gently before each use.

    Patients should use FLONASE Nasal Spray at regular intervals since its effectiveness depends on its regular use. Maximum effect may take several days and individual patients will experience a variable time to onset and different degree of symptom relief.

    2.1 Adults

    The recommended starting dosage in adults is 2 sprays (50 mcg of fluticasone propionate each) in each nostril once daily (total daily dose, 200 mcg). The same total daily dose, 1 spray in each nostril administered twice daily (e.g., 8 a.m. and 8 p.m.) is also effective. After the first few days, patients may be able to reduce their dose to 1 spray in each nostril once daily for maintenance therapy.

    Maximum total daily doses should not exceed 2 sprays in each nostril (total dose, 200 mcg/day). There is no evidence that exceeding the recommended dose is more effective.

    2.2 Adolescents and Children (Aged 4 Years and Older)

    The recommended starting dosage in adolescents and children, aged 4 years and older is 1 spray in each nostril once daily (total daily dose, 100 mcg). Patients not adequately responding to 1 spray in each nostril may use 2 sprays in each nostril once daily (total daily dose, 200 mcg). Once adequate control is achieved, the dosage should be decreased to 1 spray in each nostril once daily.

    The maximum total daily dosage should not exceed 2 sprays in each nostril (200 mcg/day) There is no evidence that exceeding the recommended dose is more effective.

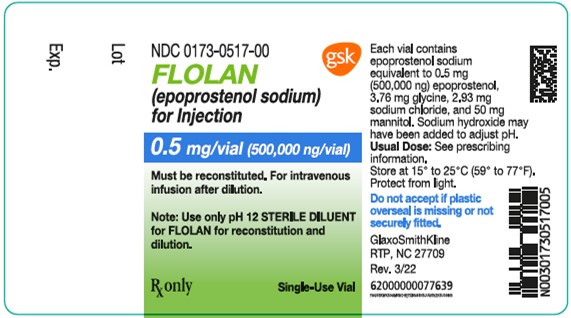
  • Flolan
    Flolan (Epoprostenol Sodium) Injection, Powder, Lyophilized, For Solution Diluent (Water) Solution [Glaxosmithkline Llc]

    Flolan

    Flolan (Epoprostenol Sodium) Injection, Powder, Lyophilized, For Solution Diluent (Water) Solution [Glaxosmithkline Llc]

    2.1 Reconstitution

    Each vial is for single use only; discard any unused diluent or unused reconstituted solution.

    Select a concentration for the solution of FLOLAN that is compatible with the infusion pump being used with respect to minimum and maximum flow rates, reservoir capacity, and the infusion pump criteria listed below [see Dosage and Administration (2.4)].

    Using aseptic technique, reconstitute FLOLAN only with STERILE DILUENT for FLOLAN or pH 12 STERILE DILUENT for FLOLAN. Table 1 gives directions for preparing several different concentrations of FLOLAN. See Table 2 for storage and administration time limits for the reconstituted FLOLAN.

    Table 1. Reconstitution and Dilution Instructions for FLOLAN Using STERILE DILUENT for FLOLAN or pH 12 STERILE DILUENT for FLOLAN.

    To make 100 mL of solution with final concentration of:

    Directions:

    3,000 ng/mL

    Dissolve contents of one 0.5‑mg vial with 5 mL of sterile diluent. Withdraw 3 mL and add to sufficient sterile diluent to make a total of 100 mL.

    5,000 ng/mL

    Dissolve contents of one 0.5‑mg vial with 5 mL of sterile diluent. Withdraw entire vial contents and add sufficient sterile diluent to make a total of 100 mL.

    10,000 ng/mL

    Dissolve contents of two 0.5‑mg vials each with 5 mL of sterile diluent. Withdraw entire vial contents and add sufficient sterile diluent to make a total of 100 mL.

    15,000 ng/mLa

    Dissolve contents of one 1.5‑mg vial with 5 mL of sterile diluent. Withdraw entire vial contents and add sufficient sterile diluent to make a total of 100 mL.

      a Higher concentrations may be prepared for patients who receive FLOLAN long‑ term. Table 2. Storage and Administration Limits for Reconstituted FLOLAN

    When Using

    STERILE DILUENT

    for FLOLAN

    When Using

    pH 12 STERILE DILUENT

    for FLOLAN

    Stability

    When used at room temperature, (15°C to 25°C; 59°F to 77°F) reconstituted solutions:

    • are stable for up to 8 hours following reconstitution or removal from refrigerated storage • may be stored for up to 40 hours refrigerated at 2°C to 8°C (36°F to 46°F) before use.

    When used with a cold pack, reconstituted solutions:

    • are stable for up to 24 hours use • may be stored refrigerated at 2°C to 8°C (36°F to 46°F) before use as long as the total time of refrigerated storage and infusion does not exceed 48 hours • Change cold packs every 12 hours.

    Freshly prepared reconstituted solutions or reconstituted solutions that have been stored at 2°C to 8°C (36°F to 46°F) for no longer than 8 days can be administered up to:

    • 72 hours at up to 25°C (77°F). • 48 hours at up to 30°C (86°F). • 24 hours at up to 35°C (95°F). • 12 hours at up to 40°C (104°F). • Reconstituted solutions can be used immediately. Refrigerate at 2°C to 8°C (36°F to 46°F) if not used immediately. • Protect from light. • Do not freeze reconstituted solutions.

    2.2 Dosage

    Initiate intravenous infusions of FLOLAN at 2 ng/kg/min. Alter the infusion by 1- to 2-ng/kg/min increments at intervals sufficient to allow assessment of clinical response. These intervals should be at least 15 minutes.

    During dose initiation, asymptomatic increases in pulmonary artery pressure coincident with increases in cardiac output may occur. In such cases, consider dose reduction, but such an increase does not imply that chronic treatment is contraindicated.

    Base changes in the chronic infusion rate on persistence, recurrence, or worsening of the patient's symptoms of pulmonary hypertension and the occurrence of adverse vasodilatory reactions. In general, expect progressive increases in dose.

    If dose-related adverse reactions occur, make dose decreases gradually in 2-ng/kg/min decrements every 15 minutes or longer until the dose-limiting effects resolve [see Adverse Reactions (6.1)]. Avoid abrupt withdrawal of FLOLAN or sudden large reductions in infusion rates [see Warnings and Precautions (5.2)].

    Following establishment of a new chronic infusion rate, measure standing and supine blood pressure for several hours.

    Taper doses of FLOLAN after initiation of cardiopulmonary bypass in patients receiving lung transplants.

    2.3 Administration

    Initiate FLOLAN in a setting with adequate personnel and equipment for physiologic monitoring and emergency care.

    Inspect parenteral drug products for particulate matter and discoloration prior to administration whenever solution and container permit. If either particulate matter or discoloration is noted, do not use.

    Administer continuous chronic infusion of FLOLAN through a central venous catheter. Temporary peripheral intravenous infusion may be used until central access is established. Do not administer bolus injections of FLOLAN.

    The ambulatory infusion pump used to administer FLOLAN should: (1) be small and lightweight, (2) be able to adjust infusion rates in 2‑ng/kg/min increments, (3) have occlusion, end-of-infusion, and low-battery alarms, (4) be accurate to ±6% of the programmed rate, and (5) be positive-pressure‑driven (continuous or pulsatile) with intervals between pulses not exceeding 3 minutes at infusion rates used to deliver FLOLAN. The reservoir should be made of polyvinyl chloride, polypropylene, or glass. Use a 60-inch microbore non-di-(2-ethylhexyl)phthalate (DEHP) extension set with proximal antisyphon valve, low priming volume (0.9 mL), and in-line 0.22-micron filter.

    To avoid interruptions in drug delivery, the patient should have access to a backup infusion pump and intravenous infusion sets.

    Do not administer or dilute reconstituted solutions of FLOLAN with other parenteral solutions or medications. Consider a multi‑lumen catheter if other intravenous therapies are routinely administered.

    Select a concentration for the solution of FLOLAN that is compatible with the infusion pump being used with respect to minimum and maximum flow rates, reservoir capacity, and the infusion pump criteria listed above. When administered chronically, prepare FLOLAN in a drug delivery reservoir appropriate for the infusion pump with a total reservoir volume of at least 100 mL, using 2 vials of Sterile Diluent for flolan or 2 vials of pH 12 STERILE DILUENT for FLOLAN.

    Generally, 3,000 ng/mL and 10,000 ng/mL are satisfactory concentrations to deliver between 2 to 16 ng/kg/min in adults. Higher infusion rates, and therefore, more concentrated solutions may be necessary with long‑term administration of FLOLAN.

    Infusion rates may be calculated using the following formula:

  • Amerge
    Amerge (Naratriptan Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    Amerge

    Amerge (Naratriptan Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    2.1 Dosing Information

    The recommended dose of AMERGE is 1 mg or 2.5 mg.

    If the migraine returns or if the patient has only partial response, the dose may be repeated once after 4 hours, for a maximum dose of 5 mg in a 24-hour period.

    The safety of treating an average of more than 4 migraine attacks in a 30‑day period has not been established.

    2.2 Dosage Adjustment in Patients with Renal Impairment

    AMERGE is contraindicated in patients with severe renal impairment (creatinine clearance: <15 mL/min) because of decreased clearance of the drug [see Contraindications (4), Use in Specific Populations (8.6), Clinical Pharmacology (12.3)].

    In patients with mild to moderate renal impairment, the maximum daily dose should not exceed 2.5 mg over a 24‑hour period and a 1-mg starting dose is recommended [see Use in Specific Populations (8.6), Clinical Pharmacology (12.3)].

    2.3 Dosage Adjustment in Patients with Hepatic Impairment

    AMERGE is contraindicated in patients with severe hepatic impairment (Child-Pugh Grade C) because of decreased clearance [see Contraindications (4), Use in Specific Populations (8.7), Clinical Pharmacology (12.3)].

    In patients with mild or moderate hepatic impairment (Child-Pugh Grade A or B), the maximum daily dose should not exceed 2.5 mg over a 24-hour period and a 1-mg starting dose is recommended [see Use in Specific Populations (8.7), Clinical Pharmacology (12.3)].

  • Innopran Xl
    Innopran Xl (Propranolol Hydrochloride) Capsule, Extended Release [Glaxosmithkline Llc]

    Innopran Xl

    Innopran Xl (Propranolol Hydrochloride) Capsule, Extended Release [Glaxosmithkline Llc]

    INNOPRAN XL should be administered once daily at bedtime (approximately 10 p.m.) and should be taken consistently either on an empty stomach or with food. The starting dose is 80 mg but dosage should be individualized and titration may be needed to a dose of 120 mg. In the clinical trial, doses of INNOPRAN XL above 120 mg had no additional effects on blood pressure (see CLINICAL PHARMACOLOGY, Pharmacodynamics and Clinical Effects). The time needed for full antihypertensive response is variable, but is usually achieved within 2 to 3 weeks.

  • Granisetron Hydrochloride Injection [Sagent Pharmaceuticals]

    Granisetron Hydrochloride

    Granisetron Hydrochloride Injection [Sagent Pharmaceuticals]

    2.1 Adults

    The usual recommended dosage for systemic and urinary tract infections for adults is 3.1 grams of TIMENTIN (3 grams ticarcillin and 100 mg clavulanic acid) given every 4 to 6 hours.

    For gynecologic infections, TIMENTIN should be administered as follows (based on ticarcillin content): Moderate infections, 200 mg/kg/day in divided doses every 6 hours; severe infections, 300 mg/kg/day in divided doses every 4 hours.

    For patients weighing less than 60 kg, the recommended dosage is 200 to 300 mg/kg/day given in divided doses every 4 to 6 hours.

    The duration of therapy depends upon the severity of infection. The usual duration is 10 to 14 days; however, in difficult and complicated infections, more prolonged therapy may be required.

    2.2 Pediatric Patients (≥3 Months of Age)

    Patients <60 kg: Mild to moderate infections, 200 mg/kg/day based on ticarcillin content in divided doses every 6 hours; severe infections, 300 mg/kg/day in divided doses every 4 hours.

    Patients ≥60 kg: Mild to moderate infections, 3.1 grams every 6 hours; severe infections, 3.1 grams every 4 hours.

    2.3 Renal Impairment

    For patients with renal insufficiency, an initial loading dose of 3.1 grams should be followed by doses based on creatinine clearance and type of dialysis as indicated in Table 1.

    Table 1. Dosage Adjustments for Renal Impairment

    Creatinine Clearance (mL/minute)a

    Dosageb

    Over 60

    3 grams every 4 hours

    30 to 60

    2 grams every 4 hours

    10 to 30

    2 grams every 8 hours

    Less than 10

    2 grams every 12 hours

    Less than 10 with hepatic dysfunction

    2 grams every 24 hours

    Patients on peritoneal dialysis

    3 grams every 12 hours

    Patients on hemodialysis

    2 grams every 12 hours supplemented with 3 grams after each dialysis

    a To calculate creatinine clearance1 from a serum creatinine value use the following formula:

    Ccr = (140–Age) (weight in kg)/72 x Scr (mg/100 mL)

    This is the calculated creatinine clearance for adult males; for females it is 15% less.

    b Based on ticarcillin content.

    2.4 Administration and Directions for Use

    TIMENTIN should be administered by intravenous infusion over a 30-minute period.

    Directions for Reconstitution and Further Dilution: 3.1‑gram Glass Vials: The 3.1‑gram vial should be reconstituted by adding approximately 13 mL of Sterile Water for Injection, USP, or Sodium Chloride Injection, USP, and shaking well. When dissolved, the concentration of ticarcillin will be approximately 200 mg/mL with a corresponding concentration of 6.7 mg/mL for clavulanic acid. The color of reconstituted solutions of TIMENTIN normally ranges from light to dark yellow, depending on concentration, duration, and temperature of storage.

    The dissolved drug should be further diluted to desired volume using the recommended solution listed under Stability [see Dosage and Administration (2.5)] to a concentration between 10 mg/mL to 100 mg/mL.

    Pharmacy Bulk Package: The container closure may be penetrated only one time utilizing a suitable sterile transfer device or dispensing set that allows measured distribution of the contents. A sterile substance that must be reconstituted prior to use may require a separate closure entry.

    Restrict use of Pharmacy Bulk Packages to an aseptic area such as a laminar flow hood.

    Reconstituted contents of the vial should be withdrawn immediately. However, if this is not possible, aliquoting operations must be completed within 4 hours of reconstitution. Discard the reconstituted stock solution 4 hours after initial entry.

    Add 76 mL of Sterile Water for Injection, USP, or Sodium Chloride Injection, USP, to the 31‑gram Pharmacy Bulk Package and shake well. For ease of reconstitution, the diluent may be added in 2 portions. Each 1 mL of the resulting concentrated stock solution contains approximately 300 mg of ticarcillin and 10 mg of clavulanic acid.

    The desired dosage should be withdrawn from the stock solution and further diluted to desired volume using the recommended solution listed under Stability [see Dosage and Administration (2.5)] to a concentration between 10 mg/mL to 100 mg/mL.

    Directions for Intravenous Infusion: After reconstitution and further dilution and prior to administration, TIMENTIN should be inspected visually for particulate matter. If particulate matter is present, the solution should be discarded.

    The solution of reconstituted drug may be administered over a 30-minute period by direct infusion or through a Y‑type intravenous infusion set. If this method of administration is used, it is advisable to temporarily discontinue the administration of any other solutions during the infusion of TIMENTIN.

    When TIMENTIN is given in combination with another antimicrobial, such as an aminoglycoside, each drug should be given separately in accordance with the recommended dosage and routes of administration for each drug [see Drug Interactions (7.1)].

    GALAXY® Container (PL 2040 Plastic): Prior to administration, TIMENTIN should be inspected visually for particulate matter. If particulate matter is present, the solution should be discarded.

    Caution: Do not use plastic containers in series connections. Such use could result in an embolism due to residual air being drawn from the primary container before administration of the fluid from the secondary container is completed.

    Preparation for Administration: See How Supplied/Storage and Handling (16) for thawing and handling instructions:

    • Suspend the container from eyelet support. • Remove protector from outlet port at bottom of container. • Attach administration set. Refer to complete directions accompanying set.

    2.5 Stability

    NOTE: TIMENTIN is incompatible with Sodium Bicarbonate.

    3.1‑gram Glass Vials: The concentrated stock solution at 200 mg/mL is stable for up to 6 hours at room temperature 21° to 24°C (70° to 75°F) or up to 72 hours under refrigeration 4°C (40°F).

    If the concentrated stock solution (200 mg/mL) is held for up to 6 hours at room temperature 21° to 24°C (70° to 75°F) or up to 72 hours under refrigeration 4°C (40°F) and further diluted to a concentration between 10 mg/mL and 100 mg/mL with any of the diluents listed below, then the following stability periods apply.

    STABILITY PERIOD

    (3.1‑gram Vials)

    Intravenous Solution

    (ticarcillin concentrations of

    10 mg/mL to 100 mg/mL)

    Room Temperature

    21° to 24°C (70° to 75°F)

    Refrigerated

    4°C (40°F)

    Dextrose Injection 5%, USP

    24 hours

    3 days

    Sodium Chloride Injection, USP

    24 hours

    7 days

    Lactated Ringer’s Injection, USP

    24 hours

    7 days

    If the concentrated stock solution (200 mg/mL) is stored for up to 6 hours at room temperature and then further diluted to a concentration between 10 mg/mL and 100 mg/mL, solutions of Sodium Chloride Injection, USP, and Lactated Ringer’s Injection, USP, may be stored frozen –18°C (0°F) for up to 30 days. Solutions prepared with Dextrose Injection 5%, USP, may be stored frozen –18°C (0°F) for up to 7 days. All thawed solutions should be used within 8 hours or discarded. Once thawed, solutions should not be refrozen.

    Unused solutions must be discarded after the time periods listed above.

    Pharmacy Bulk Package: Aliquots of the reconstituted stock solution at 300 mg/mL are stable for up to 6 hours between 21° and 24°C (70° and 75°F) or up to 72 hours under refrigeration 4°C (40°F). The reconstituted stock solution should be held under refrigeration 4°C (40°F).

    If the aliquots of the reconstituted stock solution (300 mg/mL) are held up to 6 hours between 21° and 24°C (70° and 75°F) or up to 72 hours under refrigeration 4°C (40°F) and further diluted to a concentration between 10 mg/mL and 100 mg/mL with any of the diluents listed below, then the following stability periods apply.

    STABILITY PERIOD

    (31‑gram Pharmacy Bulk Package)

    Intravenous Solution

    (ticarcillin concentrations of

    10 mg/mL to 100 mg/mL)

    Room Temperature

    21° to 24°C (70° to 75°F)

    Refrigerated

    4°C (40°F)

    Dextrose Injection 5%, USP

    24 hours

    3 days

    Sodium Chloride Injection 0.9%, USP

    24 hours

    4 days

    Lactated Ringer’s Injection, USP

    24 hours

    4 days

    Sterile Water for Injection, USP

    24 hours

    4 days

    If an aliquot of concentrated stock solution (300 mg/mL) is stored for up to 6 hours between 21° and 24°C (70° and 75°F) and then further diluted to a concentration between 10 mg/mL and 100 mg/mL, solutions of Sodium Chloride Injection, USP, Lactated Ringer’s Injection, USP, and Sterile Water for Injection, USP, may be stored frozen –18°C (0°F) for up to 30 days. Solutions prepared with Dextrose Injection 5%, USP, may be stored frozen –18°C (0°F) for up to 7 days. All thawed solutions should be used within 8 hours or discarded. Once thawed, solutions should not be refrozen.

    Unused solutions must be discarded after the time periods listed above.

    GALAXY Container (PL 2040 Plastic): Do not add supplementary medication to the container. The thawed solution is stable for 24 hours at room temperature 22°C (72°F) or for 7 days under refrigeration at 4°C (39°F).

  • Treximet (Sumatriptan And Naproxen Sodium) Tablet, Film Coated [Glaxosmithkline Llc]

    Treximet

    Treximet (Sumatriptan And Naproxen Sodium) Tablet, Film Coated [Glaxosmithkline Llc]

    TREXIMET is a fixed combination containing doses of sumatriptan (85 mg) and naproxen sodium (500 mg) within the approved dosage ranges of the individual components (25 to 100 mg of sumatriptan and 220 to 825 mg of naproxen sodium). TREXIMET contains a dose of sumatriptan higher than the lowest effective dose. Individuals may vary in response to doses of sumatriptan. The choice of the dose of sumatriptan, and of the use of a fixed combination such as in TREXIMET should therefore be made on an individual basis, weighing the possible benefit of a higher dose of sumatriptan with the potential for a greater risk of adverse events. Carefully consider the potential benefits and risks of TREXIMET and other treatment options when deciding to use TREXIMET.

    The recommended dose is 1 tablet. In controlled clinical trials, single doses of TREXIMET were effective for the acute treatment of migraine in adults (see CLINICAL TRIALS).

    The efficacy of taking a second dose has not been established. Do not take more than 2 TREXIMET tablets in 24 hours. Dosing of tablets should be at least 2 hours apart. The safety of treating an average of more than 5 migraine headaches in a 30-day period has not been established.

    TREXIMET may be administered with or without food. Tablets should not be split, crushed, or chewed.

    The combined use of TREXIMET with MAO-A inhibitors or use of TREXIMET within 2 weeks of discontinuation of MAO-A inhibitor therapy is contraindicated (see CONTRAINDICATIONS, CLINICAL PHARMACOLOGY: Drug Interactions, PRECAUTIONS: Drug Interactions).

    TREXIMET and any ergotamine-containing or ergot-type medication (like dihydroergotamine or methysergide) should not be used within 24 hours of each other. TREXIMET and other 5-HT1 agonists should not be administered within 24 hours of each other (see CONTRAINDICATIONS and PRECAUTIONS: Drug Interactions).

    TREXIMET is contraindicated in patients with hepatic impairment (see CONTRAINDICATIONS and CLINICAL PHARMACOLOGY: Special Populations).

    TREXIMET is not recommended for use in patients with creatinine clearance less than 30 mL/min (see CLINICAL PHARMACOLOGY: Special Populations and PRECAUTIONS: Renal Effects).

  • Azithromycin Tablet, Film Coated Azithromycin Powder, For Suspension [Greenstone Llc]

    Azithromycin

    Azithromycin Tablet, Film Coated Azithromycin Powder, For Suspension [Greenstone Llc]

    • Assess triglyceride levels carefully before initiating therapy. Identify other causes (e.g., diabetes mellitus, hypothyroidism, medications) of high triglyceride levels and manage as appropriate [see Indications and Usage (1)]. • Patients should be placed on an appropriate lipid-lowering diet before receiving LOVAZA, and should continue this diet during treatment with LOVAZA. In clinical studies, LOVAZA was administered with meals.

    The daily dose of LOVAZA is 4 grams per day. The daily dose may be taken as a single 4-gram dose (4 capsules) or as two 2-gram doses (2 capsules given twice daily).

    Patients should be advised to swallow LOVAZA capsules whole. Do not break open, crush, dissolve, or chew LOVAZA.

  • Arzerra (Ofatumumab) Injection, Solution [Glaxosmithkline Llc]

    Arzerra

    Arzerra (Ofatumumab) Injection, Solution [Glaxosmithkline Llc]

    2.1 Recommended Dosage Regimen

    • Dilute and administer as an intravenous infusion according to the following schedules. • Do not administer as an intravenous push or bolus or as a subcutaneous injection. • Premedicate before each infusion [see Dosage and Administration (2.4)].

    Previously Untreated CLL: The recommended dosage and schedule is:

    • 300 mg on Day 1 followed 1 week later by 1,000 mg on Day 8 (Cycle 1) followed by • 1,000 mg on Day 1 of subsequent 28-day cycles for a minimum of 3 cycles until best response or a maximum of 12 cycles.

    Refractory CLL: The recommended dosage and schedule is 12 doses administered as follows:

    • 300 mg initial dose (Dose 1), followed 1 week later by • 2,000 mg weekly for 7 doses (Doses 2 through 8), followed 4 weeks later by • 2,000 mg every 4 weeks for 4 doses (Doses 9 through 12).

    2.2 Administration

    Administer ARZERRA in an environment where facilities to adequately monitor and treat infusion reactions are available [see Warnings and Precautions (5.1)].

    Prepare all doses in 1,000 mL of 0.9% Sodium Chloride Injection, USP [see Dosage and Administration (2.5)].

    Previously Untreated CLL:

    • Cycle 1, Day 1 (300-mg dose): Initiate infusion at a rate of 3.6 mg/hour (12 mL/hour). • Cycle 1, Day 8 and Cycles 2 through 12 (1,000-mg doses): Initiate infusion at a rate of 25 mg/hour (25 mL/hour). Initiate infusion at a rate of 12 mg/hour if a Grade 3 or greater infusion-related adverse event was experienced during the previous infusion.

    In the absence of an infusion-related adverse event, the rate of infusion may be increased every 30 minutes (Table 1). Do not exceed the infusion rates in Table 1.

    Table 1. Infusion Rates for ARZERRA in Previously Untreated CLL

    Interval After

    Start of Infusion (min)

    Cycle 1, Day 1a

    (mL/hour)

    Cycle 1, Day 8b and

    Cycles 2‑12c

    (mL/hour)

    0-30

    12

    25

    31-60

    25

    50

    61-90

    50

    100

    91-120

    100

    200

    121-150

    200

    400

    151-180

    300

    400

    >180

    400

    400

    aCycle 1, Day 1 = 300 mg; median duration of infusion = 5.2 hours.

    b Cycle 1, Day 8 = 1,000 mg; median duration of infusion = 4.4 hours.

    c Cycles 2 through 12 = 1,000 mg; median durations of infusion = 4.2 to 4.4 hours.

    Refractory CLL:

    • Dose 1 (300-mg dose): Initiate infusion at a rate of 3.6 mg/hour (12 mL/hour). • Dose 2 (2,000-mg dose): Initiate infusion at a rate of 24 mg/hour (12 mL/hour). • Doses 3 through 12 (2,000-mg doses): Initiate infusion at a rate of 50 mg/hour (25 mL/hour).

    In the absence of an infusion-related adverse event, the rate of infusion may be increased every 30 minutes (Table 2). Do not exceed the infusion rates in Table 2.

    Table 2. Infusion Rates for ARZERRA in Refractory CLL

    Interval After Start of Infusion (min)

    Dose 1a

    (mL/hour)

    Dose 2b

    (mL/hour)

    Doses 3-12b

    (mL/hour)

    0-30

    12

    12

    25

    31-60

    25

    25

    50

    61-90

    50

    50

    100

    91-120

    100

    100

    200

    >120

    200

    200

    400

    aDose 1 = 300 mg; median duration of infusion = 6.8 hours.

    b Doses 2 and 3 through 12 = 2,000 mg; median duration of infusion for Dose 2 = 6.8 hours; median durations of infusion for Doses 3 through 12 = 4.2 to 4.4 hours.

    2.3 Infusion Rate Dose Modification for Infusion Reactions

    • Interrupt infusion for infusion reactions of any severity [see Warnings and Precautions (5.1)]. Treatment can be resumed at the discretion of the treating physician. The following infusion rate modifications can be used as a guide. • If the infusion reaction resolves or remains less than or equal to Grade 2, resume infusion with the following modifications according to the initial Grade of the infusion reaction. o Grade 1 or 2: Infuse at one‑half of the previous infusion rate. o Grade 3 or 4: Infuse at a rate of 12 mL/hour. • After resuming the infusion, the infusion rate may be increased according to Tables 1 and 2 above, based on patient tolerance. • Consider permanent discontinuation of ARZERRA if the severity of the infusion reaction does not resolve to less than or equal to Grade 2 despite adequate clinical intervention. • Permanently discontinue therapy for patients who develop an anaphylactic reaction to ARZERRA.

    2.4 Premedication

    Patients should receive the following premedication 30 minutes to 2 hours prior to each infusion of ARZERRA:

    Previously Untreated CLL:

    • Oral acetaminophen 1,000 mg (or equivalent) plus • Oral or intravenous antihistamine (diphenhydramine 50 mg or cetirizine 10 mg or equivalent) plus • Intravenous corticosteroid (prednisolone 50 mg or equivalent).

    If the patient did not experience a Grade 3 or greater infusion-related adverse event during the first 2 infusions of ARZERRA, the dose of corticosteroid may be reduced or omitted for subsequent infusions.

    Refractory CLL:

    • Oral acetaminophen 1,000 mg (or equivalent) plus • Oral or intravenous antihistamine (diphenhydramine 50 mg or cetirizine 10 mg or equivalent) plus • Intravenous corticosteroid (prednisolone 100 mg or equivalent).

    Do not reduce corticosteroid dose for Doses 1, 2, and 9. Corticosteroid dose may be reduced as follows:

    • Doses 3 through 8: Corticosteroid may be reduced or omitted with subsequent infusions if a Grade 3 or greater infusion reaction did not occur with the preceding dose. • Doses 10 through 12: Administer prednisolone 50 mg to 100 mg or equivalent if a Grade 3 or greater infusion reaction did not occur with Dose 9.

    2.5 Preparation and Administration

    • Do not shake product. • Inspect parenteral drug products visually for particulate matter and discoloration prior to administration. ARZERRA should be a clear to opalescent, colorless solution. The solution should not be used if discolored or cloudy, or if foreign particulate matter is present.

    Preparation of Solution:

    • 300-mg dose: Withdraw and discard 15 mL from a 1,000-mL bag of 0.9% Sodium Chloride Injection, USP. Withdraw 5 mL from each of 3 single-use 100-mg vials of ARZERRA and add to the bag. Mix diluted solution by gentle inversion. • 1,000-mg dose: Withdraw and discard 50 mL from a 1,000-mL bag of 0.9% Sodium Chloride Injection, USP. Withdraw 50 mL from 1 single-use 1,000-mg vial of ARZERRA and add to the bag. Mix diluted solution by gentle inversion. • 2,000-mg dose: Withdraw and discard 100 mL from a 1,000-mL bag of 0.9% Sodium Chloride Injection, USP. Withdraw 50 mL from each of 2 single-use 1,000-mg vials of ARZERRA and add to the bag. Mix diluted solution by gentle inversion. • Store diluted solution between 2° to 8°C (36° to 46°F). • No incompatibilities between ARZERRA and polyvinylchloride or polyolefin bags and administration sets have been observed.

    Administration Instructions:

    • Do not mix ARZERRA with, or administer as an infusion with, other medicinal products. • Administer using an infusion pump and an administration set. • Flush the intravenous line with 0.9% Sodium Chloride Injection, USP before and after each dose. • Start infusion within 12 hours of preparation. • Discard prepared solution after 24 hours.
  • Argatroban Injection, Solution [Glaxosmithkline Llc]

    Argatroban

    Argatroban Injection, Solution [Glaxosmithkline Llc]

    Argatroban Injection must be diluted 100-fold prior to infusion. Argatroban Injection should not be mixed with other drugs prior to dilution.

    2.1 Preparation for Intravenous Administration

    Argatroban Injection should be diluted in 0.9% Sodium Chloride Injection, 5% Dextrose Injection, or Lactated Ringer's Injection to a final concentration of 1 mg/mL. The contents of each 2.5-mL vial should be diluted 100-fold by mixing with 250 mL of diluent. Use 250 mg (2.5 mL) per 250 mL of diluent or 500 mg (5 mL) per 500 mL of diluent.

    The constituted solution must be mixed by repeated inversion of the diluent bag for 1 minute. Upon preparation, the solution may show slight but brief haziness due to the formation of microprecipitates that rapidly dissolve upon mixing. Use of diluent at room temperature is recommended. The final solution must be clear before use. The pH of the intravenous solution prepared as recommended is 3.2 to 7.5. Solutions prepared as recommended are stable at controlled room temperature, 20° to 25°C (68° to 77°F) (see USP) in ambient indoor light for 24 hours; therefore, light-resistant measures such as foil protection for intravenous lines are unnecessary. Solutions are physically and chemically stable for up to 96 hours when protected from light and stored at controlled room temperature, 20° to 25°C (68° to 77°F) (see USP), or at refrigerated conditions, 5° ± 3°C (41°± 5°F). Prepared solutions should not be exposed to direct sunlight. No significant potency losses have been noted following simulated delivery of the solution through intravenous tubing.

    Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever solution and container permit.

    2.2 Dosing in Patients with Heparin-Induced Thrombocytopenia

    Initial Dosage:

    Before administering argatroban, discontinue heparin therapy and obtain a baseline aPTT. The recommended initial dose of argatroban for adult patients without hepatic impairment is 2 mcg/kg/min, administered as a continuous infusion (see Table 1).

    Table 1 Recommended Doses and Infusion Rates for 2 mcg/kg/min Dose of Argatroban for Patients With HIT* and Without Hepatic Impairment (1 mg/mL Final Concentration) Body Weight (kg) Dose (mcg/min) Infusion Rate (mL/hr) * with or without thrombosis

    50

    100

    6

    60

    120

    7

    70

    140

    8

    80

    160

    10

    90

    180

    11

    100

    200

    12

    110

    220

    13

    120

    240

    14

    130

    260

    16

    140

    280

    17

    Monitoring Therapy:

    For use in HIT, therapy with Argatroban Injection is monitored using the aPTT with a target range of 1.5 to 3 times the initial baseline value (not to exceed 100 seconds). Tests of anticoagulant effects (including the aPTT) typically attain steady-state levels within 1 to 3 hours following initiation of Argatroban Injection. Check the aPTT 2 hours after initiation of therapy and after any dose change to confirm that the patient has attained the desired therapeutic range.

    Dosage Adjustment:

    After the initiation of Argatroban Injection, adjust the dose (not to exceed 10 mcg/kg/min) as necessary to obtain a steady-state aPTT in the target range [see Clinical Studies (14.1)].

    2.3 Dosing in Patients Undergoing Percutaneous Coronary Intervention

    Initial Dosage:

    Initiate an infusion of Argatroban Injection at 25 mcg/kg/min and administer a bolus of 350 mcg/kg via a large bore intravenous line over 3 to 5 minutes (see Table 2). Check an activated clotting time (ACT) 5 to 10 minutes after the bolus dose is completed. The PCI procedure may proceed if the ACT is greater than 300 seconds.

    Dosage Adjustment:

    If the ACT is less than 300 seconds, an additional intravenous bolus dose of 150 mcg/kg should be administered, the infusion dose increased to 30 mcg/kg/min, and the ACT checked 5 to 10 minutes later (see Table 2).

    If the ACT is greater than 450 seconds, decrease the infusion rate to 15 mcg/kg/min, and check the ACT 5 to 10 minutes later (Table 3).

    Continue titrating the dose until a therapeutic ACT (between 300 and 450 seconds) has been achieved; continue the same infusion rate for the duration of the PCI procedure.

    In case of dissection, impending abrupt closure, thrombus formation during the procedure, or inability to achieve or maintain an ACT over 300 seconds, additional bolus doses of 150 mcg/kg may be administered and the infusion dose increased to 40 mcg/kg/min. Check the ACT after each additional bolus or change in the rate of infusion.

    Table 2 Recommended Starting and Maintenance Doses (Within the Target ACT Range) of Argatroban Injection in Patients Undergoing PCI Without Hepatic Impairment (1 mg/mL Final Concentration) Body Weight (kg) Starting Bolus Dose (350 mcg/kg) Starting and Maintenance Continuous Infusion Dosing For ACT 300–450 seconds 25 mcg/kg/min Bolus Dose (mcg) Bolus Volume (mL) Continuous Infusion Dose (mg/min) Continuous Infusion Rate (mL/hr) NOTE: 1 mg = 1000 mcg; 1 kg = 2.2 lbs

    50

    17500

    18

    1250

    75

    60

    21000

    21

    1500

    90

    70

    24500

    25

    1750

    105

    80

    28000

    28

    2000

    120

    90

    31500

    32

    2250

    135

    100

    35000

    35

    2500

    150

    110

    38500

    39

    2750

    165

    120

    42000

    42

    3000

    180

    130

    45500

    46

    3250

    195

    140

    49000

    49

    3500

    210

    Table 3 Recommended Dose Adjustments of Argatroban Injection for Patients Outside of ACT Target Range Undergoing PCI Without Hepatic Impairment (1 mg/mL Final Concentration) Body Weight (kg) If ACT Less than 300 seconds Dosage Adjustment* 30 mcg/kg/min If ACT Greater than 450 seconds Dosage Adjustment† 15 mcg/kg/min Additional Bolus Dose (mcg) Bolus Volume (mL) Continuous Infusion Dose (mcg/min) Continuous Infusion Rate (mL/hr) Continuous Infusion Dose (mcg/min) Continuous Infusion Rate (mL/hr) NOTE: 1 mg = 1000 mcg; 1 kg = 2.2 lbs * Additional intravenous bolus dose of 150 mcg/kg should be administered if ACT less than 300 seconds. † No bolus dose is given if ACT greater than 450 seconds

    50

    7500

    8

    1500

    90

    750

    45

    60

    9000

    9

    1800

    108

    900

    54

    70

    10500

    11

    2100

    126

    1050

    63

    80

    12000

    12

    2400

    144

    1200

    72

    90

    13500

    14

    2700

    162

    1350

    81

    100

    15000

    15

    3000

    180

    1500

    90

    110

    16500

    17

    3300

    198

    1650

    99

    120

    18000

    18

    3600

    216

    1800

    108

    130

    19500

    20

    3900

    234

    1950

    117

    140

    21000

    21

    4200

    252

    2100

    126

    Monitoring Therapy:

    For use in PCI, therapy with Argatroban Injection is monitored using ACT. Obtain ACTs before dosing, 5 to 10 minutes after bolus dosing, following adjustments in the infusion rate, and at the end of the PCI procedure.

    Obtain additional ACTs every 20 to 30 minutes during a prolonged procedure.

    Continued Anticoagulation after PCI:

    If a patient requires anticoagulation after the procedure, Argatroban Injection may be continued, but at a rate of 2 mcg/kg/min and adjusted as needed to maintain the aPTT in the desired range [see Dosage and Administration (2.1)].

    2.4 Dosing in Patients With Hepatic Impairment

    Initial Dosage:

    For adult patients with HIT and moderate or severe hepatic impairment (based on Child-Pugh classification), an initial dose of 0.5 mcg/kg/min is recommended, based on the approximately 4-fold decrease in argatroban clearance relative to those with normal hepatic function. Monitor the aPTT closely, and adjust the dosage as clinically indicated.

    Monitoring Therapy:

    Achievement of steady state aPTT levels may take longer and require more dose adjustments in patients with hepatic impairment compared to patients with normal hepatic function.

    For patients with hepatic impairment undergoing PCI and who have HIT or are at risk for HIT, carefully titrate argatroban until the desired level of anticoagulation is achieved. Use of argatroban in PCI patients with clinically significant hepatic disease or AST/ALT levels ≥3 times the upper limit of normal should be avoided [see Warnings and Precautions (5.2)].

    2.5 Dosing in Pediatric Patients With Heparin-Induced Thrombocytopenia/ Heparin-Induced Thrombocytopenia and Thrombosis Syndrome

    Initial Dosage:

    Initial argatroban infusion doses are lower for seriously ill pediatric patients compared to adults with normal hepatic function [see Use in Specific Populations (8.4)].

    Monitoring Therapy:

    In general, therapy with argatroban is monitored using the aPTT. Tests of anticoagulant effects (including the aPTT) typically attain steady-state levels within one to three hours following initiation of argatroban in patients without hepatic impairment [see Warnings and Precautions (5.2)]. Dose adjustment may be required to attain the target aPTT. Check the aPTT two hours after initiation of therapy and after any dose change to confirm that the patient has attained the desired therapeutic range.

    Dosage Adjustment: [see Use in Specific Populations (8.4)].

    2.6 Conversion to Oral Anticoagulant Therapy

    Initiating Oral Anticoagulant Therapy:

    When converting patients from argatroban to oral anticoagulant therapy, consider the potential for combined effects on INR with co-administration of argatroban and warfarin. A loading dose of warfarin should not be used. Initiate therapy using the expected daily dose of warfarin. To avoid prothrombotic effects and to ensure continuous anticoagulation when initiating warfarin, it is suggested that argatroban and warfarin therapy be overlapped. There are insufficient data available to recommend the duration of the overlap.

    Co-Administration of Warfarin and Argatroban Injection at Doses up to 2 mcg/kg/min:

    Measure INR daily while Argatroban Injection and warfarin are co-administered. In general, with doses of Argatroban Injection up to 2 mcg/kg/min, Argatroban Injection can be discontinued when the INR is >4 on combined therapy. After Argatroban Injection is discontinued, repeat the INR measurement in 4 to 6 hours. If the repeat INR is below the desired therapeutic range, resume the infusion of Argatroban Injection and repeat the procedure daily until the desired therapeutic range on warfarin alone is reached.

    Co-Administration of Warfarin and Argatroban Injection at Doses Greater than 2 mcg/kg/min:

    For doses of argatroban greater than 2 mcg/kg/min, the relationship of INR between warfarin alone to the INR on warfarin plus argatroban is less predictable. In this case, in order to predict the INR on warfarin alone, temporarily reduce the dose of Argatroban Injection to a dose of 2 mcg/kg/min. Repeat the INR on Argatroban Injection and warfarin 4 to 6 hours after reduction of the Argatroban Injection dose and follow the process outlined above for administering Argatroban Injection at doses up to 2 mcg/kg/min.

  • Levitra (Vardenafil Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    Levitra

    Levitra (Vardenafil Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    2.1 General Dose Information

    For most patients, the recommended starting dose of LEVITRA is 10 mg, taken orally, as needed, approximately 60 minutes before sexual activity. The dose may be increased to a maximum recommended dose of 20 mg or decreased to 5 mg based on efficacy and side effects. The maximum recommended dosing frequency is once per day. Sexual stimulation is required for a response to treatment.

    2.2 Use with Food

    LEVITRA can be taken with or without food.

    2.3 Use in Specific Populations

    Geriatrics: A starting dose of 5 mg LEVITRA should be considered in patients ≥ 65 years of age [see Use in Specific Populations (8.5)].

    Hepatic Impairment: For patients with moderate hepatic impairment (Child-Pugh B), a starting dose of 5 mg LEVITRA is recommended. The maximum dose in patients with moderate hepatic impairment should not exceed 10 mg.

    Do not use LEVITRA in patients with severe hepatic impairment (Child-Pugh C) [see Warnings and Precautions (5.8), Use in Specific Populations (8.6) and Clinical Pharmacology (12.3)].

    Renal Impairment: Do not use LEVITRA in patients on renal dialysis [see Warnings and Precautions (5.9), Use in Specific Populations (8.7) and Clinical Pharmacology (12.3)].

    2.4 Concomitant Medications

    Nitrates: Concomitant use with nitrates and nitric oxide donors in any form is contraindicated [see Contraindications (4.1)].

    Guanylate Cyclase (GC) Stimulators, such as riociguat: Concomitant use is contraindicated [see Contraindications (4.2)].

    CYP3A4 Inhibitors: The dosage of LEVITRA may require adjustment in patients receiving potent CYP3A4 inhibitors such as ketoconazole, itraconazole, ritonavir, indinavir, saquinavir, atazanavir, and clarithromycin as well as in other patients receiving moderate CYP3A4 inhibitors such as erythromycin [see Drug Interactions (7.2)]. For ritonavir, a single dose of 2.5 mg LEVITRA should not be exceeded in a 72-hour period. For indinavir, saquinavir, atazanavir, ketoconazole 400 mg daily, itraconazole 400 mg daily, and clarithromycin, a single dose of 2.5 mg LEVITRA should not be exceeded in a 24-hour period. For ketoconazole 200 mg daily, itraconazole 200 mg daily, and erythromycin, a single dose of 5 mg LEVITRA should not be exceeded in a 24-hour period.

    Alpha-Blockers: In those patients who are stable on alpha-blocker therapy, phosphodiesterase type 5 (PDE5) inhibitors should be initiated at the lowest recommended starting dose. Concomitant treatment should be initiated only if the patient is stable on his alpha-blocker therapy. Stepwise increase in alpha-blocker dose may be associated with further lowering of blood pressure in patients taking a phosphodiesterase (PDE5) inhibitor including vardenafil. In those patients who are stable on alpha-blocker therapy, LEVITRA should be initiated at a dose of 5 mg (2.5 mg when used concomitantly with certain CYP3A4 inhibitors). [See Warnings and Precautions (5.6) and Drug Interactions (7.1).]

    A time interval between dosing should be considered when Levitra is prescribed concomitantly with alpha-blocker therapy [see Clinical Pharmacology (12.2)].

  • Staxyn (Vardenafil Hydrochloride) Tablet, Orally Disintegrating [Glaxosmithkline Llc]

    Staxyn

    Staxyn (Vardenafil Hydrochloride) Tablet, Orally Disintegrating [Glaxosmithkline Llc]

    2.1 General

    STAXYN is available in 10 mg orally disintegrating tablets. STAXYN is not interchangeable with vardenafil 10 mg film-coated tablets (LEVITRA). STAXYN provides higher systemic exposure compared to vardenafil 10 mg film-coated tablets (LEVITRA). [See Clinical Pharmacology (12.3).]

    STAXYN should be taken orally, as needed, approximately 60 minutes before sexual activity. The maximum dosing frequency is one STAXYN tablet per day. Sexual stimulation is required for a response to treatment.

    STAXYN should be placed on the tongue where it will disintegrate. The tablet should be taken without liquid. It should be taken immediately upon removal from the blister.

    Those patients who require a lower or higher dose of vardenafil need to be prescribed vardenafil film-coated tablets [see Patient Counseling Information (17.11)].

    2.2 Use with Food

    STAXYN can be taken with or without food.

    2.3 Use in Special Populations

    Hepatic Impairment:  Do not use STAXYN in  patients with moderate (Child-Pugh B) or severe (Child-Pugh C) hepatic impairment [see Warnings and Precautions (5.8) and Clinical Pharmacology (12.3)].

    Renal Impairment: Do not use STAXYN in patients on renal dialysis [see Warnings and Precautions (5.9) and Clinical Pharmacology (12.3)].

    2.4 Concomitant Medications

    Nitrates: Concomitant use with nitrates in any form is contraindicated [see Contraindications (4.1)].

    Guanylate Cyclase (GC) Stimulators, such as riociguat: Concomitant use is contraindicated [see Contraindications (4.2)].

    CYP3A4 Inhibitors: Do not use STAXYN with potent or moderate CYP3A4 inhibitors such as ketoconazole, itraconazole, ritonavir, indinavir, saquinavir, atazanavir, clarithromycin and erythromycin [see Warnings and Precautions (5.2) and Drug Interactions (7.2)]. 

    Alpha-Blockers: In those patients who are stable on alpha-blocker therapy, PDE5 inhibitors should be initiated at the lowest recommended starting dose. Stepwise increase in alpha-blocker dose may be associated with further lowering of blood pressure in patients taking a phosphodiesterase (PDE5) inhibitor including vardenafil. In patients taking alpha-blockers, do not initiate vardenafil therapy with STAXYN. Lower doses of vardenafil film-coated tablets should be used as initial therapy in these patients. [see Dosage and Administration (2.4)]. Patients taking alpha-blockers who have previously used vardenafil film-coated tablets may change to STAXYN at the advice of their healthcare provider. [See Warnings and Precautions (5.6) and Drug Interactions (7.1).]

    A time interval between dosing should be considered when STAXYN is prescribed concomitantly with alpha-blocker therapy [see Clinical Pharmacology (12.2)].

  • Avandaryl
    Avandaryl (Rosiglitazone Maleate And Glimepiride) Tablet, Film Coated [Glaxosmithkline Llc]

    Avandaryl

    Avandaryl (Rosiglitazone Maleate And Glimepiride) Tablet, Film Coated [Glaxosmithkline Llc]

    Therapy with AVANDARYL should be individualized for each patient. The risk-benefit of initiating monotherapy versus dual therapy with AVANDARYL should be considered.

    No studies have been performed specifically examining the safety and efficacy of AVANDARYL in patients previously treated with other oral hypoglycemic agents and switched to AVANDARYL. Any change in therapy of type 2 diabetes should be undertaken with care and appropriate monitoring as changes in glycemic control can occur. [See Indications and Usage (1).]

    2.1 Starting Dose

    The recommended starting dose is 4 mg/1 mg administered once daily with the first meal of the day. For adults already treated with a sulfonylurea or rosiglitazone, a starting dose of 4 mg/2 mg may be considered.

    All patients should start the rosiglitazone component of AVANDARYL at the lowest recommended dose. Further increases in the dose of rosiglitazone should be accompanied by careful monitoring for adverse events related to fluid retention [see Boxed Warning, Warnings and Precautions (5.1)].

    When switching from combination therapy of rosiglitazone plus glimepiride as separate tablets, the usual starting dose of AVANDARYL is the dose of rosiglitazone and glimepiride already being taken.

    When colesevelam is coadministered with glimepiride, maximum plasma concentration and total exposure to glimepiride is reduced. Therefore, AVANDARYL should be administered at least 4 hours prior to colesevelam.

    2.2 Dose Titration

    Dose increases should be individualized according to the glycemic response of the patient. Patients who may be more sensitive to glimepiride [see Warnings and Precautions (5.3)], including the elderly, debilitated, or malnourished, and those with renal, hepatic, or adrenal insufficiency, should be carefully titrated to avoid hypoglycemia. If hypoglycemia occurs during up-titration of the dose or while maintained on therapy, a dosage reduction of the glimepiride component of AVANDARYL may be considered. Increases in the dose of rosiglitazone should be accompanied by careful monitoring for adverse events related to fluid retention [see Boxed Warning, Warnings and Precautions (5.1)].

    To switch to AVANDARYL for adults currently treated with rosiglitazone, dose titration of the glimepiride component of AVANDARYL is recommended if patients are not adequately controlled after 1 to 2 weeks. The glimepiride component may be increased in no more than 2 mg increments. After an increase in the dosage of the glimepiride component, dose titration of AVANDARYL is recommended if patients are not adequately controlled after 1 to 2 weeks.

    To switch to AVANDARYL for adults currently treated with sulfonylurea, it may take 2 weeks to see a reduction in blood glucose and 2 to 3 months to see the full effect of the rosiglitazone component. Therefore, dose titration of the rosiglitazone component of AVANDARYL is recommended if patients are not adequately controlled after 8 to 12 weeks. Patients should be observed carefully (1 to 2 weeks) for hypoglycemia when being transferred from longer half-life sulfonylureas (e.g., chlorpropamide) to AVANDARYL due to potential overlapping of drug effect. After an increase in the dosage of the rosiglitazone component, dose titration of AVANDARYL is recommended if patients are not adequately controlled after 2 to 3 months.

    2.3 Maximum Dose

    The maximum recommended daily dose is 8 mg rosiglitazone and 4 mg glimepiride.

    2.4 Specific Patient Populations

    Elderly and Malnourished Patients and Those With Renal, Hepatic, or Adrenal Insufficiency: In elderly, debilitated, or malnourished patients, or in patients with renal, hepatic, or adrenal insufficiency, the starting dose, dose increments, and maintenance dosage of AVANDARYL should be conservative to avoid hypoglycemic reactions. [See Warnings and Precautions (5.3), Clinical Pharmacology (12.3).]

    Hepatic Impairment: Liver enzymes should be measured prior to initiating treatment with AVANDARYL. Therapy with AVANDARYL should not be initiated if the patient exhibits clinical evidence of active liver disease or increased serum transaminase levels (ALT >2.5X upper limit of normal at start of therapy). After initiation of AVANDARYL, liver enzymes should be monitored periodically per the clinical judgment of the healthcare professional. [See Warnings and Precautions (5.6), Clinical Pharmacology (12.3).]

    Pregnancy and Lactation: AVANDARYL should not be used during pregnancy or in nursing mothers.

    Pediatric Use: Safety and effectiveness of AVANDARYL in pediatric patients have not been established. AVANDARYL and its components, rosiglitazone and glimepiride, are not recommended for use in pediatric patients.

  • Avandamet (Rosiglitazone Maleate And Metformin Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    Avandamet

    Avandamet (Rosiglitazone Maleate And Metformin Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    The dosage of antidiabetic therapy with AVANDAMET should be individualized on the basis of effectiveness and tolerability. The risk-benefit of initiating monotherapy versus dual therapy with AVANDAMET should be considered.

    2.1 Starting Dose

    AVANDAMET is generally given in divided doses with meals.

    All patients should start the rosiglitazone component of AVANDAMET at the lowest recommended dose. Further increases in the dose of rosiglitazone should be accompanied by careful monitoring for adverse events related to fluid retention [see Boxed Warning, Warnings and Precautions (5.2)].

    Patients Inadequately Controlled on Diet and Exercise: If therapy with a combination tablet containing rosiglitazone and metformin is considered appropriate for a patient with type 2 diabetes mellitus inadequately controlled on diet and exercise alone, the recommended starting dose of AVANDAMET is 2 mg/500 mg administered once or twice daily. For patients with HbA1c >11% or fasting plasma glucose (FPG) >270 mg/dL, a starting dose of 2 mg/500 mg twice daily may be considered. The dose of AVANDAMET may be increased in increments of 2 mg/500 mg per day given in divided doses if patients are not adequately controlled after 4 weeks. The maximum dose of AVANDAMET is 8 mg/2,000 mg per day.

    Patients Inadequately Controlled on Rosiglitazone or Metformin Monotherapy: If therapy with a combination tablet containing rosiglitazone and metformin is considered appropriate for a patient with type 2 diabetes mellitus inadequately controlled on rosiglitazone or metformin monotherapy, then the selection of the dose of AVANDAMET should be based on the patient’s current doses of rosiglitazone and/or metformin.

    To switch to AVANDAMET for patients currently treated with metformin, the usual starting dose of AVANDAMET is 4 mg rosiglitazone (total daily dose) plus the dose of metformin already being taken (see Table 1).

    To switch to AVANDAMET for patients currently treated with rosiglitazone, the usual starting dose of AVANDAMET is 1,000 mg metformin (total daily dose) plus the dose of rosiglitazone already being taken (see Table 1).

    When switching from combination therapy of rosiglitazone plus metformin as separate tablets, the usual starting dose of AVANDAMET is the dose of rosiglitazone and metformin already being taken.

    Table 1. AVANDAMET Starting Dose for Patients Treated With Metformin and/or Rosiglitazone

    PRIOR THERAPY

    Usual AVANDAMET Starting Dose

    Total Daily Dose

    Tablet Strength

    Number of Tablets

    Metformina

    1,000 mg/day

    2 mg/500 mg

    1 tablet twice a day

    2,000 mg/day

    2 mg/1,000 mg

    1 tablet twice a day

    Rosiglitazone

    4 mg/day

    2 mg/500 mg

    1 tablet twice a day

    8 mg/day

    4 mg/500 mg

    1 tablet twice a day

    a   For patients on doses of metformin between 1,000 and 2,000 mg/day, initiation of AVANDAMET requires individualization of therapy.

    2.2 Dose Titration

    AVANDAMET is generally given in divided doses with meals, with gradual dose escalation. This reduces gastrointestinal side effects (largely due to metformin) and permits determination of the minimum effective dose for the individual patient.

    Sufficient time should be given to assess adequacy of therapeutic response. FPG should be used initially to determine the therapeutic response to AVANDAMET. If additional glycemic control is needed, the daily dose of AVANDAMET may be increased by increments of 4 mg rosiglitazone and/or 500 mg metformin.

    After an increase in metformin dosage, dose titration is recommended if patients are not adequately controlled after 1 to 2 weeks. After an increase in rosiglitazone dosage, dose titration is recommended if patients are not adequately controlled after 8 to 12 weeks.

    2.3 Maximum Dose

    The maximum recommended total daily dose of AVANDAMET is 8 mg rosiglitazone (taken as 4 mg twice daily) and 2,000 mg metformin (taken as 1,000 mg twice daily).

    2.4 Specific Patient Populations

    Renal Impairment: Any dosage adjustment should be based on a careful assessment of renal function. Generally, elderly, debilitated, and malnourished patients should not be titrated to the maximum dose of AVANDAMET. Monitoring of renal function is necessary to aid in prevention of metformin-associated lactic acidosis, particularly in the elderly [see Warnings and Precautions (5.1)].

    Hepatic Impairment: Liver enzymes should be measured prior to initiating treatment with AVANDAMET. Therapy with AVANDAMET should not be initiated if the patient exhibits clinical evidence of active liver disease or increased serum transaminase levels (ALT >2.5X upper limit of normal at start of therapy). After initiation of AVANDAMET, liver enzymes should be monitored periodically per the clinical judgment of the healthcare professional [see Warnings and Precautions (5.6), Clinical Pharmacology (12.3)].

    Geriatric: The initial and maintenance dosing of AVANDAMET should be conservative in patients with advanced age, due to the potential for decreased renal function in this population.

    Pediatric: Safety and effectiveness of AVANDAMET in pediatric patients have not been established. AVANDAMET and rosiglitazone are not recommended for use in pediatric patients.

    Pregnancy: AVANDAMET is not recommended for use in pregnancy.

  • Zantac (Ranitidine Hydrochloride) Tablet, Film Coated Zantac (Ranitidine Hydrochloride) Syrup [Glaxosmithkline Llc]

    Zantac

    Zantac (Ranitidine Hydrochloride) Tablet, Film Coated Zantac (Ranitidine Hydrochloride) Syrup [Glaxosmithkline Llc]

    Active Duodenal Ulcer:

    The current recommended adult oral dosage of ZANTAC for duodenal ulcer is 150 mg twice daily. An alternative dosage of 300 mg once daily after the evening meal or at bedtime can be used for patients in whom dosing convenience is important. The advantages of one treatment regimen compared with the other in a particular patient population have yet to be demonstrated (see Clinical Trials: Active Duodenal Ulcer). Smaller doses have been shown to be equally effective in inhibiting gastric acid secretion in US trials, and several foreign trials have shown that 100 mg twice daily is as effective as the 150-mg dose.

    Antacid should be given as needed for relief of pain (see CLINICAL PHARMACOLOGY: Pharmacokinetics).

    Maintenance of Healing of Duodenal Ulcers:

    The current recommended adult oral dosage is 150 mg at bedtime.

    Pathological Hypersecretory Conditions (such as Zollinger-Ellison syndrome):

    The current recommended adult oral dosage is 150 mg twice daily. In some patients it may be necessary to administer ZANTAC 150-mg doses more frequently. Dosages should be adjusted to individual patient needs, and should continue as long as clinically indicated. Dosages up to 6 g/day have been employed in patients with severe disease.

    Benign Gastric Ulcer:

    The current recommended adult oral dosage is 150 mg twice daily.

    Maintenance of Healing of Gastric Ulcers:

    The current recommended adult oral dosage is 150 mg at bedtime.

    GERD:

    The current recommended adult oral dosage is 150 mg twice daily.

    Erosive Esophagitis:

    The current recommended adult oral dosage is 150 mg 4 times daily.

    Maintenance of Healing of Erosive Esophagitis:

    The current recommended adult oral dosage is 150 mg twice daily.

    Pediatric Use:

    The safety and effectiveness of ZANTAC have been established in the age-group of 1 month to 16 years. There is insufficient information about the pharmacokinetics of ZANTAC in neonatal patients (aged younger than 1 month) to make dosing recommendations.

    The following 3 subsections provide dosing information for each of the pediatric indications.

    Treatment of Duodenal and Gastric Ulcers: The recommended oral dose for the treatment of active duodenal and gastric ulcers is 2 to 4 mg/kg twice daily to a maximum of 300 mg/day. This recommendation is derived from adult clinical trials and pharmacokinetic data in pediatric patients.

    Maintenance of Healing of Duodenal and Gastric Ulcers: The recommended oral dose for the maintenance of healing of duodenal and gastric ulcers is 2 to 4 mg/kg once daily to a maximum of 150 mg/day. This recommendation is derived from adult clinical trials and pharmacokinetic data in pediatric patients.

    Treatment of GERD and Erosive Esophagitis: Although limited data exist for these conditions in pediatric patients, published literature supports a dosage of 5 to 10 mg/kg/day, usually given as 2 divided doses.

    Dosage Adjustment for Patients with Impaired Renal Function:

    On the basis of experience with a group of subjects with severely impaired renal function treated with ZANTAC, the recommended dosage in patients with a creatinine clearance <50 mL/min is 150 mg every 24 hours. Should the patient's condition require, the frequency of dosing may be increased to every 12 hours or even further with caution. Hemodialysis reduces the level of circulating ranitidine. Ideally, the dosing schedule should be adjusted so that the timing of a scheduled dose coincides with the end of hemodialysis.

    Elderly patients are more likely to have decreased renal function, therefore caution should be exercised in dose selection, and it may be useful to monitor renal function (see CLINICAL PHARMACOLOGY: Pharmacokinetics: Geriatrics and PRECAUTIONS: Geriatric Use).

  • Veramyst (Fluticasone Furoate) Spray, Metered [Glaxosmithkline Llc]

    Veramyst

    Veramyst (Fluticasone Furoate) Spray, Metered [Glaxosmithkline Llc]

    Administer VERAMYST Nasal Spray by the intranasal route only. Prime VERAMYST Nasal Spray before using for the first time by shaking the contents well and releasing 6 sprays into the air away from the face. When VERAMYST Nasal Spray has not been used for more than 30 days or if the cap has been left off the bottle for 5 days or longer, prime the pump again until a fine mist appears. Shake VERAMYST Nasal Spray well before each use.

    Titrate an individual patient to the minimum effective dosage to reduce the possibility of side effects.

    2.1 Adults and Adolescents Aged 12 Years and Older

    The recommended starting dosage is 110 mcg once daily administered as 2 sprays (27.5 mcg/spray) in each nostril. When the maximum benefit has been achieved and symptoms have been controlled, reducing the dosage to 55 mcg (1 spray in each nostril) once daily may be effective in maintaining control of allergic rhinitis symptoms.

    2.2 Children Aged 2 to 11 Years

    The recommended starting dosage in children is 55 mcg once daily administered as 1 spray (27.5 mcg/spray) in each nostril. Children not adequately responding to 55 mcg may use 110 mcg (2 sprays in each nostril) once daily. Once symptoms have been controlled, dosage reduction to 55 mcg once daily is recommended.

  • Bexxar
    Bexxar (Tositumomab) Kit Bexxar Dosimetric (Tositumomab I-131) Injection Bexxar Therapeutic (Tositumomab I-131) Injection [Glaxosmithkline Llc]

    Bexxar

    Bexxar (Tositumomab) Kit Bexxar Dosimetric (Tositumomab I-131) Injection Bexxar Therapeutic (Tositumomab I-131) Injection [Glaxosmithkline Llc]

    The BEXXAR therapeutic regimen consists of 2 separate components (tositumomab and iodine I 131 tositumomab) administered in 2 separate steps (dosimetric dose and therapeutic dose) separated by 7 to 14 days.

    Parenteral drug products should be inspected for particulate matter prior to administration, whenever solution and container permit [see Description (11)].

    2.1 Overview of Dosing Schedule

    ]

    2.2 Recommended Dose

    Dosimetric dose

    1. Tositumomab 450 mg by intravenous infusion 2. I-131 tositumomab (5 mCi I-131 and 35 mg protein) by intravenous infusion

    Therapeutic dose (administered 7-14 days after dosimetric dose)

    1. Tositumomab 450 mg by intravenous infusion 2. I-131 tositumomab (35 mg) by intravenous infusion. The iodine-131 dose is calculated based on 1) assessment of dosimetry and biodistribution obtained following the dosimetric dose, and 2) platelet counts obtained within 28 days prior to dosing.   If platelet counts are 150,000 platelets/mm3 or greater:   The recommended dose (mCi) is the activity of Iodine-131 calculated to deliver 75 cGy total body irradiation   If platelet counts are 100,000 to 149,000 platelets/mm3:   The recommended dose is the activity of Iodine-131 calculated to deliver 65 cGy total body irradiation

    2.3 Preparation of Dosimetric Dose

    Tositumomab Dosimetric Dose

    1. Withdraw and discard 32 mL from a 50-mL bag 0.9% Sodium Chloride for Injection, USP. 2. Withdraw and transfer entire contents from each of the two 225-mg tositumomab vials (a total of 450 mg tositumomab in 32 mL) to remaining 18 mL in bag of 0.9% Sodium Chloride for Injection, USP to yield a final volume of 50 mL. 3. DO NOT SHAKE. Gently mix the solution by inverting/rotating the bag. The tositumomab solution is clear to opalescent, colorless to slightly yellow, and may contain white particulates. 4. Diluted tositumomab may be stored at 36°F to 46°F (2°C to 8°C) for 24 hours or at room temperature for 8 hours. Discard unused solution.

    I-131 Tositumomab Dosimetric Dose

    Required materials (not supplied):

    • Lead shielding for preparation vial and syringe pump • One sterile 30-mL preparation vial • Two lead pots at room temperature

    Method

    1. Thaw contents (approximately 60 minutes) of I-131 tositumomab dosimetric vial at room temperature with appropriate lead shielding. Thawed undiluted I-131 tositumomab may be stored up to 8 hours at 36°F to 46°F (2°C to 8°C) or at room temperature. 2. Calculate the volume required for I-131 tositumomab activity of 5.0 mCi, based on the activity concentration of dosimetric vial (refer to product specification sheet provided in dosimetric carton). 3. Withdraw and transfer the calculated volume from I-131 tositumomab vial to the shielded preparation vial. 4. Assay preparation vial to confirm activity is 5.0 mCi (±10%) using a suitable radioactivity calibration system operated in accordance with the manufacturer’s specifications and quality control for the measurement of Iodine-131. • If the preparation vial contains the calculated activity (±10%), proceed to step 5. • If the preparation vial does not contain the calculated activity (5 mCi ±10%), determine the activity concentration of the I-131 tositumomab based on the volume and the activity in the preparation vial. Add or subtract the appropriate volume of I-131 tositumomab to the preparation vial to achieve the desired activity of 5.0 mCi (±10%). Re-assay to confirm. 5. Calculate the amount of tositumomab in the shielded preparation vial, based on the volume and labeled protein concentration of the I-131 tositumomab dosimetric vial (see product specification sheet provided in dosimetric carton). If less than 35 mg, add additional tositumomab from the non-radioactive vial to the shielded vial to yield a total of 35 mg tositumomab in the shielded vial. 6. Add a sufficient quantity of 0.9% Sodium Chloride for Injection, USP to the shielded preparation vial to yield a final volume of 30 mL. Gently mix contents. 7. Withdraw the entire contents from the preparation vial into a 60-mL syringe using a large bore needle (18-gauge) and shield contents of syringe and syringe pump.   8. Assay and record the activity.

    2.4 Administration of Dosimetric Dose

    Thyroid Protective Pre-medication: Initiate thyroid protective drugs 24 hours prior to the dosimetric dose and continue daily dosing for a minimum of 14 days following the therapeutic dose. The following regimens are recommended:

    • Saturated solution of potassium iodide (SSKI) 4 drops orally 3 times daily or • Lugol’s solution 20 drops orally 3 times daily or • Potassium iodide tablets 130 mg orally once daily

    Do not administer the dosimetric dose unless the patient has received at least 3 doses of SSKI, 3 doses of Lugol’s solution, or 1 dose of 130-mg potassium iodide tablet.

    Tositumomab

    1. Premedicate with oral diphenhydramine 50 mg and oral acetaminophen 650 mg, 30 minutes prior to initiation of the dosimetric dose. 2. Administer 450 mg tositumomab in 50 mL 0.9% sodium chloride by intravenous infusion through a 0.22 micron in-line filter over 60 minutes (refer to Site Training Manual for diagram showing assembly of the infusion set components). Decrease the rate of infusion by 50% for mild to moderate infusion reactions. Discontinue for serious allergic reactions; interrupt for severe infusion reactions. If severe infusion reaction completely resolves, the infusion may be continued at 50% of the previous infusion rate.

    I-131 Tositumomab

    3. Attach the shielded syringe containing the I-131 tositumomab dose in a syringe pump to the intravenous line containing the in-line filter used in step 2 above . A change in filter can result in loss of up to 7% of the I-131 tositumomab dose. 4. Set syringe pump to deliver the entire dose of I-131 tositumomab over 20 minutes, immediately following completion of the tositumomab infusion. Decrease the rate of infusion by 50% for mild to moderate infusion reactions. Discontinue for serious allergic reactions; interrupt for severe infusion reactions. If severe infusion reaction completely resolves, the infusion may be continued at 50% of the previous infusion rate. 5. Upon completion of the I-131 tositumomab infusion, flush the IV line with 0.9% Sodium Chloride for Injection, USP. 6. Determine the combined residual activity of the syringe and infusion set components (stopcock, extension set, primary infusion set, and in-line filter set) by assaying these items in a suitable radioactivity calibration system immediately following completion of administration of all components of the dosimetric dose. 7. Calculate and record the dose delivered to the patient by subtracting the residual activity in the syringe and the infusion set components from the activity of I-131 tositumomab in the syringe prior to infusion.   8. Discard unused portion of Iodine I-131 tositumomab and infusion set components according to federal and state laws regarding radioactive and biohazardous waste.

    2.5 Assessment of Dosimetry and Biodistribution

    Additional copies of templates for recording dosimetry and calculation of the I-131 tositumomab therapeutic dose and the Site Training Manual may be obtained from the GlaxoSmithKline Wholesale Service Center (1-877-423-9927).

    Obtain total body gamma camera counts and whole body images at the following timepoints:

    1. Count 1 (Day 0) : Within 1 hour following the end of the I-131 tositumomab infusion and prior to urination, obtain total body gamma camera count and whole body images. 2. Count 2 (Day 2, 3, or 4): Obtain total body gamma camera counts and whole body images, immediately following urination. 3. Count 3 (Day 6 or 7): Obtain total body gamma camera counts and whole body images, immediately following urination.   Verify that the expected biodistribution is present.

    Assess Biodistribution: Determine total body residence time and examine whole body camera images done at Count 1 and Count 2. Examine image performed at Count 3 as needed to resolve ambiguities.

    Expected biodistribution characteristics:

    Count 1 (day of dosimetric dose)

    • Most of the activity is in the blood pool (heart and major blood vessels). Uptake in normal liver and spleen is less than in the heart.

    Count 2 (Day 2, 3, or 4) and Count 3 (Day 6 or 7)

    • Activity in the blood pool decreases significantly. Decreased accumulation of activity in normal liver and spleen. Possible uptake present in thyroid, kidney, and urinary bladder with minimal uptake in the lungs. Possible increased intensity at known lymphoma sites.

    Biodistribution is altered if any of the following is present:

    Count 1:

    • Blood pool is not visualized • Diffuse, intense tracer uptake in the liver and/or spleen or uptake suggestive of urinary obstruction • Diffuse uptake in normal lung greater than that of blood pool.

    Count 2 and Count 3:

    • Uptake is suggestive of urinary obstruction • Diffuse uptake in normal lung which is greater than that of the blood pool • Total body residence time is less than 50 hours • Total body residence time is more than 150 hours.

    2.6 Calculation of I-131 Therapeutic Dose

    The therapeutic dose may be calculated manually using the total body residence time and activity hours (refer to the Site Training Manual). The therapeutic dose may also be derived by using the GlaxoSmithKline BEXXAR therapeutic regimen Patient Management Templates (refer to the Site Training Manual). For assistance with either manual or automated calculations call the GlaxoSmithKline Wholesale Service Center at 1-877-423-9927.

    The following equation is used to calculate the activity of Iodine-131 required for delivery of the desired total body dose of radiation:

    2.7 Preparation of Therapeutic Dose

    Tositumomab

    A 450-mg dose of tositumomab should be prepared as previously described [see Dosage and Administration (2.3)].

    I-131 tositumomab

    Required materials (not supplied):

    • Lead shielding for preparation vial and syringe pump • One sterile 50-mL preparation vial • Two lead pots at room temperature.

    Method

    Thaw contents (approximately 60 minutes) of I-131 tositumomab therapeutic vial at room temperature with appropriate lead shielding. Thawed, undiluted I-131 tositumomab may be stored up to 8 hours at 36°F to 46°F (2°C to 8°C) or at room temperature. Do not freeze solutions of diluted I-131 tositumomab; store refrigerated until time of use.

    1. Calculate the volume (see activity concentration on the product specification sheet provided with the therapeutic vial) of I-131 tositumomab activity required to deliver either 75cGy or 65cGy total body irradiation [see Dosage and Administration (2.6)]. 2. Withdraw and transfer the calculated volume from I-131 tositumomab vial to the shielded preparation vial. 3. Assay preparation vial to confirm calculated activity using a suitable radioactivity calibration system operated in accordance with the manufacturer’s specifications and quality control for the measurement of Iodine-131. • If the assayed dose in the preparation vial contains the calculated activity (±10%), proceed to step 5. • If the assayed dose in the preparation vial does not contain the calculated activity (±10%), determine the activity concentration of I-131 tositumomab based on the volume and the activity in the preparation vial. Add or subtract the appropriate volume of I-131 tositumomab to the preparation vial to achieve the required I-131 tositumomab activity. Re-assay the preparation vial contents to confirm. 4. Calculate the amount of tositumomab in the shielded preparation vial, based on the volume and protein concentration of I-131 tositumomab (refer to product specification sheet for the vial in the therapeutic carton). If the amount of tositumomab in the preparation vial is less than 35 mg, add additional tositumomab from the non-radioactive 35-mg vial to the shielded preparation vial to yield a total of 35 mg tositumomab in the shielded vial. 5. Add a sufficient quantity of 0.9% Sodium Chloride for Injection, USP to the shielded preparation vial to yield a final volume of 30 mL. Gently mix contents. 6. Withdraw the entire contents from the shielded preparation vial into a 60-mL syringe using a large bore needle (18-gauge) and shield contents of syringe and syringe pump.   7. Assay and record activity.

    2.8 Administration of Therapeutic Dose

    Do not administer the therapeutic dose if biodistribution is altered [see Dosage and Administration (2.5)].

    Tositumomab

    Premedicate with oral diphenhydramine 50 mg and oral acetaminophen 650 mg 30 minutes prior to initiation of the therapeutic dose.

    Administer 450 mg tositumomab in 50 mL 0.9% sodium chloride by intravenous infusion through a 0.22 micron in-line filter over 60 minutes (refer to Site Training Manual for diagram showing assembly of the infusion set components). Decrease the rate of infusion by 50% for mild to moderate infusion reactions. Discontinue for serious allergic reactions; interrupt for severe infusion reactions. If severe infusion reaction completely resolves, the infusion may be continued at 50% of the previous infusion rate.

    I-131 Tositumomab

    Attach the shielded syringe containing the I-131 tositumomab therapeutic dose to the intravenous line containing the in-line filter used in step 2 above. A change in filter can result in loss of up to 7% of the I-131 tositumomab dose. Set syringe pump to deliver the entire dose of I-131 tositumomab over 20 minutes, immediately following completion of the tositumomab infusion. Decrease the rate of infusion by 50% for mild to moderate infusion reactions. Discontinue for serious allergic reactions; interrupt for severe infusion reactions. If severe infusion reaction completely resolves, the infusion may be continued at 50% of the previous infusion rate.

    1. Upon completion of I-131 tositumomab infusion, flush the IV line with 0.9% Sodium Chloride for Injection, USP. 2. Determine the combined residual activity of the syringe and infusion set components (stopcock, extension set, primary infusion set and in-line filter set) by assaying these items in a suitable radioactivity calibration system immediately following completion of administration of all components of the therapeutic dose. 3. Calculate and record the dose delivered to the patient by subtracting the residual activity in the syringe and the infusion set components from the activity of I-131 tositumomab in the syringe prior to infusion.   4. Discard unused portion of Iodine I-131 tositumomab and infusion set components according to federal and state laws regarding radioactive and biohazardous waste.

    2.9 Radiation Dosimetry

    Estimations of radiation-absorbed doses for I-131 tositumomab were performed using sequential whole body images and the MIRDOSE 3 software program. Patients with apparent thyroid, stomach, or intestinal imaging were selected for organ dosimetry analyses. The estimated radiation-absorbed doses to organs and marrow from a course of the BEXXAR therapeutic regimen are presented in Table 1.

    Table 1. Estimated Radiation-Absorbed Organ Doses

    The BEXXAR therapeutic regimen

    mGy/MBq

    Median

    The BEXXAR therapeutic regimen

    mGy/MBq

    Range

    Organ Regions of Interest (ROIs)

       Thyroid

    2.71

    1.4 - 6.2

       Kidneys

    1.96

    1.5 - 2.5

       Upper large intestine wall

    1.34

    0.8 - 1.7

       Lower large intestine wall

    1.30

    0.8 - 1.6

       Heart wall

    1.25

    0.5 - 1.8

       Spleen

    1.14

    0.7 - 5.4

       Testes

    0.83

    0.3 - 1.3

       Liver

    0.82

    0.6 - 1.3

       Lungs

    0.79

    0.5 - 1.1

       Marrow space

    0.65

    0.5 - 1.1

       Stomach wall

    0.40

    0.2 - 0.8

    Whole Body ROIs

       Urine bladder wall

    0.64

    0.6 - 0.9

       Bone surfaces

    0.41

    0.4 - 0.6

       Pancreas

    0.31

    0.2 - 0.4

       Gall bladder wall

    0.29

    0.2 - 0.3

       Adrenals

    0.28

    0.2 - 0.3

       Ovaries

    0.25

    0.2 - 0.3

       Small intestine

    0.23

    0.2 - 0.3

       Thymus

    0.22

    0.1 - 0.3

       Uterus

    0.20

    0.2 - 0.2

       Muscle

    0.18

    0.1 - 0.2

       Breasts

    0.16

    0.1 - 0.2

       Skin

    0.13

    0.1 - 0.2

       Brain

    0.13

    0.1 - 0.2

       Total body

    0.24

    0.2 - 0.3

  • Jalyn (Dutasteride And Tamsulosin Hydrochloride) Capsule [Glaxosmithkline Llc]

    Jalyn

    Jalyn (Dutasteride And Tamsulosin Hydrochloride) Capsule [Glaxosmithkline Llc]

    The recommended dosage of JALYN is 1 capsule (0.5 mg dutasteride and 0.4 mg tamsulosin hydrochloride) taken once daily approximately 30 minutes after the same meal each day.

    The capsules should be swallowed whole and not chewed or opened. Contact with the contents of the JALYN capsule may result in irritation of the oropharyngeal mucosa.

  • Lamictal (Lamotrigine) Tablet Lamictal (Lamotrigine) Tablet, Chewable Lamictal Odt (Lamotrigine) Tablet, Orally Disintegrating Lamictal (Lamotrigine) Kit [Glaxosmithkline Llc]

    Lamictal

    Lamictal (Lamotrigine) Tablet Lamictal (Lamotrigine) Tablet, Chewable Lamictal Odt (Lamotrigine) Tablet, Orally Disintegrating Lamictal (Lamotrigine) Kit [Glaxosmithkline Llc]

    2.1 General Dosing Considerations

    Rash

    There are suggestions, yet to be proven, that the risk of severe, potentially life-threatening rash may be increased by (1) coadministration of LAMICTAL with valproate, (2) exceeding the recommended initial dose of LAMICTAL, or (3) exceeding the recommended dose escalation for LAMICTAL. However, cases have occurred in the absence of these factors [see Boxed Warning]. Therefore, it is important that the dosing recommendations be followed closely.

    The risk of nonserious rash may be increased when the recommended initial dose and/or the rate of dose escalation for LAMICTAL is exceeded and in patients with a history of allergy or rash to other AEDs.

    LAMICTAL Starter Kits and LAMICTAL ODT® Patient Titration Kits provide LAMICTAL at doses consistent with the recommended titration schedule for the first 5 weeks of treatment, based upon concomitant medications, for patients with epilepsy (older than 12 years) and bipolar I disorder (adults) and are intended to help reduce the potential for rash. The use of LAMICTAL Starter Kits and LAMICTAL ODT Patient Titration Kits is recommended for appropriate patients who are starting or restarting LAMICTAL [see How Supplied/Storage and Handling (16)].

    It is recommended that LAMICTAL not be restarted in patients who discontinued due to rash associated with prior treatment with lamotrigine unless the potential benefits clearly outweigh the risks. If the decision is made to restart a patient who has discontinued LAMICTAL, the need to restart with the initial dosing recommendations should be assessed. The greater the interval of time since the previous dose, the greater consideration should be given to restarting with the initial dosing recommendations. If a patient has discontinued lamotrigine for a period of more than 5 half-lives, it is recommended that initial dosing recommendations and guidelines be followed. The half-life of lamotrigine is affected by other concomitant medications [see Clinical Pharmacology (12.3)].

    LAMICTAL Added to Drugs Known to Induce or Inhibit Glucuronidation

    Because lamotrigine is metabolized predominantly by glucuronic acid conjugation, drugs that are known to induce or inhibit glucuronidation may affect the apparent clearance of lamotrigine. Drugs that induce glucuronidation include carbamazepine, phenytoin, phenobarbital, primidone, rifampin, estrogen-containing oral contraceptives, and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir. Valproate inhibits glucuronidation. For dosing considerations for LAMICTAL in patients on estrogen-containing contraceptives and atazanavir/ritonavir, see below and Table 13. For dosing considerations for LAMICTAL in patients on other drugs known to induce or inhibit glucuronidation, see Tables 1, 2, 5-6, and 13.

    Target Plasma Levels for Patients with Epilepsy or Bipolar Disorder

    A therapeutic plasma concentration range has not been established for lamotrigine. Dosing of LAMICTAL should be based on therapeutic response [see Clinical Pharmacology (12.3)].

    Women Taking Estrogen-Containing Oral Contraceptives

    Starting LAMICTAL in Women Taking Estrogen-Containing Oral Contraceptives: Although estrogen-containing oral contraceptives have been shown to increase the clearance of lamotrigine [see Clinical Pharmacology (12.3)], no adjustments to the recommended dose-escalation guidelines for LAMICTAL should be necessary solely based on the use of estrogen-containing oral contraceptives. Therefore, dose escalation should follow the recommended guidelines for initiating adjunctive therapy with LAMICTAL based on the concomitant AED or other concomitant medications (see Tables 1, 5, and 7). See below for adjustments to maintenance doses of LAMICTAL in women taking estrogen-containing oral contraceptives.

    Adjustments to the Maintenance Dose of LAMICTAL in Women Taking Estrogen-Containing Oral Contraceptives:

    (1) Taking Estrogen-Containing Oral Contraceptives: In women not taking carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation [see Drug Interactions (7), Clinical Pharmacology (12.3)], the maintenance dose of LAMICTAL will in most cases need to be increased by as much as 2-fold over the recommended target maintenance dose to maintain a consistent lamotrigine plasma level.

    (2) Starting Estrogen-Containing Oral Contraceptives: In women taking a stable dose of LAMICTAL and not taking carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation [see Drug Interactions (7), Clinical Pharmacology (12.3)], the maintenance dose will in most cases need to be increased by as much as 2-fold to maintain a consistent lamotrigine plasma level. The dose increases should begin at the same time that the oral contraceptive is introduced and continue, based on clinical response, no more rapidly than 50 to 100 mg/day every week. Dose increases should not exceed the recommended rate (see Tables 1 and 5) unless lamotrigine plasma levels or clinical response support larger increases. Gradual transient increases in lamotrigine plasma levels may occur during the week of inactive hormonal preparation (pill-free week), and these increases will be greater if dose increases are made in the days before or during the week of inactive hormonal preparation. Increased lamotrigine plasma levels could result in additional adverse reactions, such as dizziness, ataxia, and diplopia. If adverse reactions attributable to LAMICTAL consistently occur during the pill-free week, dose adjustments to the overall maintenance dose may be necessary. Dose adjustments limited to the pill-free week are not recommended. For women taking LAMICTAL in addition to carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation [see Drug Interactions (7), Clinical Pharmacology (12.3)], no adjustment to the dose of LAMICTAL should be necessary.

    (3) Stopping Estrogen-Containing Oral Contraceptives: In women not taking carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation [see Drug Interactions (7), Clinical Pharmacology (12.3)], the maintenance dose of LAMICTAL will in most cases need to be decreased by as much as 50% in order to maintain a consistent lamotrigine plasma level. The decrease in dose of LAMICTAL should not exceed 25% of the total daily dose per week over a 2-week period, unless clinical response or lamotrigine plasma levels indicate otherwise [see Clinical Pharmacology (12.3)]. In women taking LAMICTAL in addition to carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation [see Drug Interactions (7), Clinical Pharmacology (12.3)], no adjustment to the dose of LAMICTAL should be necessary.

    Women and Other Hormonal Contraceptive Preparations or Hormone Replacement Therapy

    The effect of other hormonal contraceptive preparations or hormone replacement therapy on the pharmacokinetics of lamotrigine has not been systematically evaluated. It has been reported that ethinylestradiol, not progestogens, increased the clearance of lamotrigine up to 2-fold, and the progestin-only pills had no effect on lamotrigine plasma levels. Therefore, adjustments to the dosage of LAMICTAL in the presence of progestogens alone will likely not be needed.

    Patients Taking Atazanavir/Ritonavir

    While atazanavir/ritonavir does reduce the lamotrigine plasma concentration, no adjustments to the recommended dose-escalation guidelines for LAMICTAL should be necessary solely based on the use of atazanavir/ritonavir. Dose escalation should follow the recommended guidelines for initiating adjunctive therapy with LAMICTAL based on concomitant AED or other concomitant medications (see Tables 1, 2, and 5). In patients already taking maintenance doses of LAMICTAL and not taking glucuronidation inducers, the dose of LAMICTAL may need to be increased if atazanavir/ritonavir is added, or decreased if atazanavir/ritonavir is discontinued [see Clinical Pharmacology (12.3)].

    Patients with Hepatic Impairment

    Experience in patients with hepatic impairment is limited. Based on a clinical pharmacology study in 24 subjects with mild, moderate, and severe liver impairment [see Use in Specific Populations (8.6), Clinical Pharmacology (12.3)], the following general recommendations can be made. No dosage adjustment is needed in patients with mild liver impairment. Initial, escalation, and maintenance doses should generally be reduced by approximately 25% in patients with moderate and severe liver impairment without ascites and 50% in patients with severe liver impairment with ascites. Escalation and maintenance doses may be adjusted according to clinical response.

    Patients with Renal Impairment

    Initial doses of LAMICTAL should be based on patients’ concomitant medications (see Tables 1-3 and 5); reduced maintenance doses may be effective for patients with significant renal impairment [see Use in Specific Populations (8.7), Clinical Pharmacology (12.3)]. Few patients with severe renal impairment have been evaluated during chronic treatment with LAMICTAL. Because there is inadequate experience in this population, LAMICTAL should be used with caution in these patients.

    Discontinuation Strategy

    Epilepsy: For patients receiving LAMICTAL in combination with other AEDs, a re-evaluation of all AEDs in the regimen should be considered if a change in seizure control or an appearance or worsening of adverse reactions is observed.

    If a decision is made to discontinue therapy with LAMICTAL, a step-wise reduction of dose over at least 2 weeks (approximately 50% per week) is recommended unless safety concerns require a more rapid withdrawal [see Warnings and Precautions (5.8)].

    Discontinuing carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation should prolong the half-life of lamotrigine; discontinuing valproate should shorten the half-life of lamotrigine.

    Bipolar Disorder: In the controlled clinical trials, there was no increase in the incidence, type, or severity of adverse reactions following abrupt termination of LAMICTAL. In the clinical development program in adults with bipolar disorder, 2 patients experienced seizures shortly after abrupt withdrawal of LAMICTAL. Discontinuation of LAMICTAL should involve a step-wise reduction of dose over at least 2 weeks (approximately 50% per week) unless safety concerns require a more rapid withdrawal [see Warnings and Precautions (5.8)].

    2.2 Epilepsy—Adjunctive Therapy

    This section provides specific dosing recommendations for patients older than 12 years and patients aged 2 to 12 years. Within each of these age-groups, specific dosing recommendations are provided depending upon concomitant AEDs or other concomitant medications (see Table 1 for patients older than 12 years and Table 2 for patients aged 2 to 12 years). A weight-based dosing guide for patients aged 2 to 12 years on concomitant valproate is provided in Table 3.

    Patients Older than 12 Years

    Recommended dosing guidelines are summarized in Table 1.

    Table 1. Escalation Regimen for LAMICTAL in Patients Older than 12 Years with Epilepsy

    In Patients TAKING Valproatea

    In Patients NOT TAKING Carbamazepine, Phenytoin, Phenobarbital, Primidone,b or Valproatea

    In Patients TAKING Carbamazepine, Phenytoin, Phenobarbital, or Primidoneb and NOT TAKING Valproatea

    Weeks 1 and 2

    25 mg every other day

    25 mg every day

    50 mg/day

    Weeks 3 and 4

    25 mg every day

    50 mg/day

    100 mg/day

    (in 2 divided doses)

    Week 5 onward to maintenance

    Increase by 25 to 50 mg/day every 1 to 2 weeks.

    Increase by 50 mg/day every 1 to 2 weeks.

    Increase by 100 mg/day every 1 to 2 weeks.

    Usual maintenance dose

    100 to 200 mg/day with valproate alone

    225 to 375 mg/day

    (in 2 divided doses)

    300 to 500 mg/day

    (in 2 divided doses)

    100 to 400 mg/day with valproate and other drugs that induce glucuronidation

    (in 1 or 2 divided doses)

    aValproate has been shown to inhibit glucuronidation and decrease the apparent clearance of lamotrigine [see Drug Interactions (7), Clinical Pharmacology (12.3)].

    bDrugs that induce lamotrigine glucuronidation and increase clearance, other than the specified antiepileptic drugs, include estrogen-containing oral contraceptives, rifampin, and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir. Dosing recommendations for oral contraceptives and the protease inhibitor atazanavir/ritonavir can be found in General Dosing Considerations [see Dosage and Administration (2.1)]. Patients on rifampin and the protease inhibitor lopinavir/ritonavir should follow the same dosing titration/maintenance regimen used with antiepileptic drugs that induce glucuronidation and increase clearance [see Dosage and Administration (2.1), Drug Interactions (7), and Clinical Pharmacology (12.3)].

    Patients Aged 2 to 12 Years

    Recommended dosing guidelines are summarized in Table 2.

    Lower starting doses and slower dose escalations than those used in clinical trials are recommended because of the suggestion that the risk of rash may be decreased by lower starting doses and slower dose escalations. Therefore, maintenance doses will take longer to reach in clinical practice than in clinical trials. It may take several weeks to months to achieve an individualized maintenance dose. Maintenance doses in patients weighing less than 30 kg, regardless of age or concomitant AED, may need to be increased as much as 50%, based on clinical response.

    The smallest available strength of LAMICTAL chewable dispersible tablets is 2 mg, and only whole tablets should be administered. If the calculated dose cannot be achieved using whole tablets, the dose should be rounded down to the nearest whole tablet [see How Supplied/Storage and Handling (16) and Medication Guide].

    Table 2. Escalation Regimen for LAMICTAL in Patients Aged 2 to 12 Years with Epilepsy

    In Patients TAKING Valproatea

    In Patients NOT TAKING Carbamazepine, Phenytoin, Phenobarbital, Primidone,b or Valproatea

    In Patients TAKING Carbamazepine, Phenytoin, Phenobarbital, or Primidoneb and NOT TAKING Valproatea

    Weeks 1 and 2

    0.15 mg/kg/day

    in 1 or 2 divided doses, rounded down to the nearest whole tablet (see Table 3 for weight-based dosing guide)

    0.3 mg/kg/day

    in 1 or 2 divided doses, rounded down to the nearest whole tablet

    0.6 mg/kg/day

    in 2 divided doses, rounded down to the nearest whole tablet

    Weeks 3 and 4

    0.3 mg/kg/day

    in 1 or 2 divided doses, rounded down to the nearest whole tablet (see Table 3 for weight-based dosing guide)

    0.6 mg/kg/day

    in 2 divided doses, rounded down to the nearest whole tablet

    1.2 mg/kg/day

    in 2 divided doses, rounded down to the nearest whole tablet

    Week 5 onward to maintenance

    The dose should be increased every 1 to 2 weeks as follows: calculate 0.3 mg/kg/day, round this amount down to the nearest whole tablet, and add this amount to the previously administered daily dose.

    The dose should be increased every 1 to 2 weeks as follows: calculate 0.6 mg/kg/day, round this amount down to the nearest whole tablet, and add this amount to the previously administered daily dose.

    The dose should be increased every 1 to 2 weeks as follows: calculate 1.2 mg/kg/day, round this amount down to the nearest whole tablet, and add this amount to the previously administered daily dose.

    Usual maintenance dose

    1 to 5 mg/kg/day

    (maximum 200 mg/day in 1 or 2 divided doses)

    1 to 3 mg/kg/day

    with valproate alone

    4.5 to 7.5 mg/kg/day

    (maximum 300 mg/day in 2 divided doses)

    5 to 15 mg/kg/day

    (maximum 400 mg/day in 2 divided doses)

    Maintenance dose in patients less than 30 kg

    May need to be increased by as much as 50%, based on clinical response.

    May need to be increased by as much as 50%, based on clinical response.

    May need to be increased by as much as 50%, based on clinical response.

    Note: Only whole tablets should be used for dosing.

      a Valproate has been shown to inhibit glucuronidation and decrease the apparent clearance of lamotrigine [see Drug Interactions (7), Clinical Pharmacology (12.3)] .   b Drugs that induce lamotrigine glucuronidation and increase clearance, other than the specified antiepileptic drugs, include estrogen-containing oral contraceptives, rifampin, and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir. Dosing recommendations for oral contraceptives and the protease inhibitor atazanavir/ritonavir can be found in General Dosing Considerations [see Dosage and Administration (2.1)] . Patients on rifampin and the protease inhibitor lopinavir/ritonavir should follow the same dosing titration/maintenance regimen used with antiepileptic drugs that induce glucuronidation and increase clearance [see Dosage and Administration (2.1), Drug Interactions (7), and Clinical Pharmacology (12.3)] .

    Table 3. The Initial Weight-Based Dosing Guide for Patients Aged 2 to 12 Years Taking Valproate (Weeks 1 to 4) with Epilepsy

    If the patient’s weight is

    Give this daily dose, using the most appropriate combination of LAMICTAL 2- and 5-mg tablets

    Greater than

    And less than

    Weeks 1 and 2

    Weeks 3 and 4

    6.7 kg

    14 kg

    2 mg every other day

    2 mg every day

    14.1 kg

    27 kg

    2 mg every day

    4 mg every day

    27.1 kg

    34 kg

    4 mg every day

    8 mg every day

    34.1 kg

    40 kg

    5 mg every day

    10 mg every day

    Usual Adjunctive Maintenance Dose for Epilepsy

    The usual maintenance doses identified in Tables 1 and 2 are derived from dosing regimens employed in the placebo-controlled adjunctive trials in which the efficacy of LAMICTAL was established. In patients receiving multidrug regimens employing carbamazepine, phenytoin, phenobarbital, or primidone without valproate, maintenance doses of adjunctive LAMICTAL as high as 700 mg/day have been used. In patients receiving valproate alone, maintenance doses of adjunctive LAMICTAL as high as 200 mg/day have been used. The advantage of using doses above those recommended in Tables 1-4 has not been established in controlled trials.

    2.3 Epilepsy—Conversion from Adjunctive Therapy to Monotherapy

    The goal of the transition regimen is to attempt to maintain seizure control while mitigating the risk of serious rash associated with the rapid titration of LAMICTAL.

    The recommended maintenance dose of LAMICTAL as monotherapy is 500 mg/day given in 2 divided doses.

    To avoid an increased risk of rash, the recommended initial dose and subsequent dose escalations for LAMICTAL should not be exceeded [see Boxed Warning].

    Conversion from Adjunctive Therapy with Carbamazepine, Phenytoin, Phenobarbital, or Primidone to Monotherapy with LAMICTAL

    After achieving a dose of 500 mg/day of LAMICTAL using the guidelines in Table 1, the concomitant enzyme-inducing AED should be withdrawn by 20% decrements each week over a 4-week period. The regimen for the withdrawal of the concomitant AED is based on experience gained in the controlled monotherapy clinical trial.

    Conversion from Adjunctive Therapy with Valproate to Monotherapy with LAMICTAL

    The conversion regimen involves the 4 steps outlined in Table 4.

    Table 4. Conversion from Adjunctive Therapy with Valproate to Monotherapy with LAMICTAL in Patients Aged 16 Years and Older with Epilepsy

    LAMICTAL

    Valproate

    Step 1

    Achieve a dose of 200 mg/day according to guidelines in Table 1.

    Maintain established stable dose.

    Step 2

    Maintain at 200 mg/day.

    Decrease dose by decrements no greater than 500 mg/day/week to 500 mg/day and then maintain for 1 week.

    Step 3

    Increase to 300 mg/day and maintain for 1 week.

    Simultaneously decrease to 250 mg/day and maintain for 1 week.

    Step 4

    Increase by 100 mg/day every week to achieve maintenance dose of 500 mg/day.

    Discontinue.

    Conversion from Adjunctive Therapy with Antiepileptic Drugs other than Carbamazepine, Phenytoin, Phenobarbital, Primidone, or Valproate to Monotherapy with LAMICTAL

    No specific dosing guidelines can be provided for conversion to monotherapy with LAMICTAL with AEDs other than carbamazepine, phenytoin, phenobarbital, primidone, or valproate.

    2.4 Bipolar Disorder

    The goal of maintenance treatment with LAMICTAL is to delay the time to occurrence of mood episodes (depression, mania, hypomania, mixed episodes) in patients treated for acute mood episodes with standard therapy [see Indications and Usage (1)].

    Patients taking LAMICTAL for more than 16 weeks should be periodically reassessed to determine the need for maintenance treatment.

    Adults

    The target dose of LAMICTAL is 200 mg/day (100 mg/day in patients taking valproate, which decreases the apparent clearance of lamotrigine, and 400 mg/day in patients not taking valproate and taking either carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitor lopinavir/ritonavir that increase the apparent clearance of lamotrigine). In the clinical trials, doses up to 400 mg/day as monotherapy were evaluated; however, no additional benefit was seen at 400 mg/day compared with 200 mg/day [see Clinical Studies (14.2)]. Accordingly, doses above 200 mg/day are not recommended.

    Treatment with LAMICTAL is introduced, based on concurrent medications, according to the regimen outlined in Table 5. If other psychotropic medications are withdrawn following stabilization, the dose of LAMICTAL should be adjusted. In patients discontinuing valproate, the dose of LAMICTAL should be doubled over a 2-week period in equal weekly increments (see Table 6). In patients discontinuing carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation, the dose of LAMICTAL should remain constant for the first week and then should be decreased by half over a 2-week period in equal weekly decrements (see Table 6). The dose of LAMICTAL may then be further adjusted to the target dose (200 mg) as clinically indicated.

    If other drugs are subsequently introduced, the dose of LAMICTAL may need to be adjusted. In particular, the introduction of valproate requires reduction in the dose of LAMICTAL [see Drug Interactions (7), Clinical Pharmacology (12.3)].

    To avoid an increased risk of rash, the recommended initial dose and subsequent dose escalations of LAMICTAL should not be exceeded [see Boxed Warning].

    Table 5. Escalation Regimen for LAMICTAL in Adults with Bipolar Disorder

    In Patients TAKING Valproatea

    In Patients NOT TAKING Carbamazepine, Phenytoin, Phenobarbital, Primidone,b or Valproatea

    In Patients TAKING Carbamazepine, Phenytoin, Phenobarbital, or Primidoneb and NOT TAKING Valproatea

    Weeks 1 and 2

    25 mg every other day

    25 mg daily

    50 mg daily

    Weeks 3 and 4

    25 mg daily

    50 mg daily

    100 mg daily, in divided doses

    Week 5

    50 mg daily

    100 mg daily

    200 mg daily, in divided doses

    Week 6

    100 mg daily

    200 mg daily

    300 mg daily, in divided doses

    Week 7

    100 mg daily

    200 mg daily

    up to 400 mg daily, in divided doses

      a Valproate has been shown to inhibit glucuronidation and decrease the apparent clearance of lamotrigine [see Drug Interactions (7), Clinical Pharmacology (12.3)] .   b Drugs that induce lamotrigine glucuronidation and increase clearance, other than the specified antiepileptic drugs, include estrogen-containing oral contraceptives, rifampin, and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir. Dosing recommendations for oral contraceptives and the protease inhibitor atazanavir/ritonavir can be found in General Dosing Considerations [see Dosage and Administration (2.1)] . Patients on rifampin and the protease inhibitor lopinavir/ritonavir should follow the same dosing titration/maintenance regimen used with antiepileptic drugs that induce glucuronidation and increase clearance [see Dosage and Administration (2.1), Drug Interactions (7), and Clinical Pharmacology (12.3)] .

    Table 6. Dosage Adjustments to LAMICTAL in Adults with Bipolar Disorder Following Discontinuation of Psychotropic Medications

    Discontinuation of Psychotropic Drugs (excluding Valproate,a Carbamazepine, Phenytoin, Phenobarbital, or Primidoneb)

    After Discontinuation of Valproatea

    After Discontinuation of Carbamazepine, Phenytoin, Phenobarbital, or Primidoneb

    Current Dose of LAMICTAL (mg/day)

    100

    Current Dose of LAMICTAL (mg/day)

    400

    Week 1

    Maintain current dose of LAMICTAL

    150

    400

    Week 2

    Maintain current dose of LAMICTAL

    200

    300

    Week 3 onward

    Maintain current dose of LAMICTAL

    200

    200

      a Valproate has been shown to inhibit glucuronidation and decrease the apparent clearance of lamotrigine [see Drug Interactions (7), Clinical Pharmacology (12.3)] .   b Drugs that induce lamotrigine glucuronidation and increase clearance, other than the specified antiepileptic drugs, include estrogen-containing oral contraceptives, rifampin, and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir. Dosing recommendations for oral contraceptives and the protease inhibitor atazanavir/ritonavir can be found in General Dosing Considerations [see Dosage and Administration (2.1)]. Patients on rifampin and the protease inhibitor lopinavir/ritonavir should follow the same dosing titration/maintenance regimen used with antiepileptic drugs that induce glucuronidation and increase clearance [see Dosage and Administration (2.1), Drug Interactions (7), and Clinical Pharmacology (12.3)] .

    2.5 Administration of LAMICTAL Chewable Dispersible Tablets

    LAMICTAL chewable dispersible tablets may be swallowed whole, chewed, or dispersed in water or diluted fruit juice. If the tablets are chewed, consume a small amount of water or diluted fruit juice to aid in swallowing.

    To disperse LAMICTAL chewable dispersible tablets, add the tablets to a small amount of liquid (1 teaspoon, or enough to cover the medication). Approximately 1 minute later, when the tablets are completely dispersed, swirl the solution and consume the entire quantity immediately. No attempt should be made to administer partial quantities of the dispersed tablets.

    2.6 Administration of LAMICTAL ODT Orally Disintegrating Tablets

    LAMICTAL ODT orally disintegrating tablets should be placed onto the tongue and moved around in the mouth. The tablet will disintegrate rapidly, can be swallowed with or without water, and can be taken with or without food.

  • Lamictal Xr (Lamotrigine) Tablet, Film Coated, Extended Release Lamictal Xr (Lamotrigine) Kit [Glaxosmithkline Llc]

    Lamictal Xr

    Lamictal Xr (Lamotrigine) Tablet, Film Coated, Extended Release Lamictal Xr (Lamotrigine) Kit [Glaxosmithkline Llc]

    LAMICTAL XR extended-release tablets are taken once daily, with or without food. Tablets must be swallowed whole and must not be chewed, crushed, or divided.

    2.1 General Dosing Considerations

    Rash

    There are suggestions, yet to be proven, that the risk of severe, potentially life-threatening rash may be increased by (1) coadministration of LAMICTAL XR with valproate, (2) exceeding the recommended initial dose of LAMICTAL XR, or (3) exceeding the recommended dose escalation for LAMICTAL XR. However, cases have occurred in the absence of these factors [see Boxed Warning]. Therefore, it is important that the dosing recommendations be followed closely.

    The risk of nonserious rash may be increased when the recommended initial dose and/or the rate of dose escalation for LAMICTAL XR is exceeded and in patients with a history of allergy or rash to other AEDs.

    LAMICTAL XR Patient Titration Kits provide LAMICTAL XR at doses consistent with the recommended titration schedule for the first 5 weeks of treatment, based upon concomitant medications, for patients with partial-onset seizures and are intended to help reduce the potential for rash. The use of LAMICTAL XR Patient Titration Kits is recommended for appropriate patients who are starting or restarting LAMICTAL XR [see How Supplied/Storage and Handling (16)].

    It is recommended that LAMICTAL XR not be restarted in patients who discontinued due to rash associated with prior treatment with lamotrigine unless the potential benefits clearly outweigh the risks. If the decision is made to restart a patient who has discontinued LAMICTAL XR, the need to restart with the initial dosing recommendations should be assessed. The greater the interval of time since the previous dose, the greater consideration should be given to restarting with the initial dosing recommendations. If a patient has discontinued lamotrigine for a period of more than 5 half-lives, it is recommended that initial dosing recommendations and guidelines be followed. The half-life of lamotrigine is affected by other concomitant medications [see Clinical Pharmacology (12.3)].

    LAMICTAL XR Added to Drugs Known to Induce or Inhibit Glucuronidation

    Because lamotrigine is metabolized predominantly by glucuronic acid conjugation, drugs that are known to induce or inhibit glucuronidation may affect the apparent clearance of lamotrigine. Drugs that induce glucuronidation include carbamazepine, phenytoin, phenobarbital, primidone, rifampin, estrogen-containing oral contraceptives, and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir. Valproate inhibits glucuronidation. For dosing considerations for LAMICTAL XR in patients on estrogen-containing contraceptives and atazanavir/ritonavir, see below and Table 5. For dosing considerations for LAMICTAL XR in patients on other drugs known to induce or inhibit glucuronidation, see Table 1 and Table 5.

    Target Plasma Levels

    A therapeutic plasma concentration range has not been established for lamotrigine. Dosing of LAMICTAL XR should be based on therapeutic response [see Clinical Pharmacology (12.3)].

    Women Taking Estrogen-Containing Oral Contraceptives

    Starting LAMICTAL XR in Women Taking Estrogen-Containing Oral Contraceptives: Although estrogen-containing oral contraceptives have been shown to increase the clearance of lamotrigine [see Clinical Pharmacology (12.3)], no adjustments to the recommended dose-escalation guidelines for LAMICTAL XR should be necessary solely based on the use of estrogen-containing oral contraceptives. Therefore, dose escalation should follow the recommended guidelines for initiating adjunctive therapy with LAMICTAL XR based on the concomitant AED or other concomitant medications (see Table 1). See below for adjustments to maintenance doses of LAMICTAL XR in women taking estrogen-containing oral contraceptives.

    Adjustments to the Maintenance Dose of LAMICTAL XR in Women Taking Estrogen-Containing Oral Contraceptives:

    (1) Taking Estrogen-Containing Oral Contraceptives: In women not taking carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation [see Drug Interactions (7), Clinical Pharmacology (12.3)], the maintenance dose of LAMICTAL XR will in most cases need to be increased by as much as 2-fold over the recommended target maintenance dose to maintain a consistent lamotrigine plasma level.

    (2) Starting Estrogen-Containing Oral Contraceptives: In women taking a stable dose of LAMICTAL XR and not taking carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation [see Drug Interactions (7), Clinical Pharmacology (12.3)], the maintenance dose will in most cases need to be increased by as much as 2-fold to maintain a consistent lamotrigine plasma level. The dose increases should begin at the same time that the oral contraceptive is introduced and continue, based on clinical response, no more rapidly than 50 to 100 mg/day every week. Dose increases should not exceed the recommended rate (see Table 1) unless lamotrigine plasma levels or clinical response support larger increases. Gradual transient increases in lamotrigine plasma levels may occur during the week of inactive hormonal preparation (pill-free week), and these increases will be greater if dose increases are made in the days before or during the week of inactive hormonal preparation. Increased lamotrigine plasma levels could result in additional adverse reactions, such as dizziness, ataxia, and diplopia. If adverse reactions attributable to LAMICTAL XR consistently occur during the pill-free week, dose adjustments to the overall maintenance dose may be necessary. Dose adjustments limited to the pill-free week are not recommended. For women taking LAMICTAL XR in addition to carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation [see Drug Interactions (7), Clinical Pharmacology (12.3)], no adjustment to the dose of LAMICTAL XR should be necessary.

    (3) Stopping Estrogen-Containing Oral Contraceptives: In women not taking carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation [see Drug Interactions (7), Clinical Pharmacology (12.3)], the maintenance dose of LAMICTAL XR will in most cases need to be decreased by as much as 50% in order to maintain a consistent lamotrigine plasma level. The decrease in dose of LAMICTAL XR should not exceed 25% of the total daily dose per week over a 2-week period, unless clinical response or lamotrigine plasma levels indicate otherwise [see Clinical Pharmacology (12.3)]. In women taking LAMICTAL XR in addition to carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation [see Drug Interactions (7), Clinical Pharmacology (12.3)], no adjustment to the dose of LAMICTAL XR should be necessary.

    Women and Other Hormonal Contraceptive Preparations or Hormone Replacement Therapy

    The effect of other hormonal contraceptive preparations or hormone replacement therapy on the pharmacokinetics of lamotrigine has not been systematically evaluated. It has been reported that ethinylestradiol, not progestogens, increased the clearance of lamotrigine up to 2-fold, and the progestin-only pills had no effect on lamotrigine plasma levels. Therefore, adjustments to the dosage of LAMICTAL XR in the presence of progestogens alone will likely not be needed.

    Patients Taking Atazanavir/Ritonavir

    While atazanavir/ritonavir does reduce the lamotrigine plasma concentration, no adjustments to the recommended dose-escalation guidelines for LAMICTAL XR should be necessary solely based on the use of atazanavir/ritonavir. Dose escalation should follow the recommended guidelines for initiating adjunctive therapy with LAMICTAL XR based on concomitant AED or other concomitant medications (see Tables 1 and 5). In patients already taking maintenance doses of LAMICTAL XR and not taking glucuronidation inducers, the dose of LAMICTAL XR may need to be increased if atazanavir/ritonavir is added, or decreased if atazanavir/ritonavir is discontinued [see Clinical Pharmacology (12.3)].

    Patients with Hepatic Impairment

    Experience in patients with hepatic impairment is limited. Based on a clinical pharmacology study in 24 subjects with mild, moderate, and severe liver impairment [see Use in Specific Populations (8.6), Clinical Pharmacology (12.3)], the following general recommendations can be made. No dosage adjustment is needed in patients with mild liver impairment. Initial, escalation, and maintenance doses should generally be reduced by approximately 25% in patients with moderate and severe liver impairment without ascites and 50% in patients with severe liver impairment with ascites. Escalation and maintenance doses may be adjusted according to clinical response.

    Patients with Renal Impairment

    Initial doses of LAMICTAL XR should be based on patients’ concomitant medications (see Table 1); reduced maintenance doses may be effective for patients with significant renal impairment [see Use in Specific Populations (8.7), Clinical Pharmacology (12.3)]. Few patients with severe renal impairment have been evaluated during chronic treatment with immediate-release lamotrigine. Because there is inadequate experience in this population, LAMICTAL XR should be used with caution in these patients.

    Discontinuation Strategy

    For patients receiving LAMICTAL XR in combination with other AEDs, a re-evaluation of all AEDs in the regimen should be considered if a change in seizure control or an appearance or worsening of adverse reactions is observed.

    If a decision is made to discontinue therapy with LAMICTAL XR, a step-wise reduction of dose over at least 2 weeks (approximately 50% per week) is recommended unless safety concerns require a more rapid withdrawal [see Warnings and Precautions (5.8)].

    Discontinuing carbamazepine, phenytoin, phenobarbital, primidone, or other drugs such as rifampin and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir that induce lamotrigine glucuronidation should prolong the half-life of lamotrigine; discontinuing valproate should shorten the half-life of lamotrigine.

    2.2 Adjunctive Therapy for Primary Generalized Tonic-Clonic and Partial-Onset Seizures

    This section provides specific dosing recommendations for patients aged 13 years and older. Specific dosing recommendations are provided depending upon concomitant AEDs or other concomitant medications.

    Table 1. Escalation Regimen for LAMICTAL XR in Patients Aged 13 Years and Older

    In Patients TAKING Valproatea

    In Patients NOT TAKING Carbamazepine, Phenytoin, Phenobarbital, Primidone,b or Valproatea

    In Patients TAKING Carbamazepine, Phenytoin, Phenobarbital, or Primidoneb and NOT TAKING Valproatea

    Weeks 1 and 2

    25 mg every other day

    25 mg every day

    50 mg every day

    Weeks 3 and 4

    25 mg every day

    50 mg every day

    100 mg every day

    Week 5

    50 mg every day

    100 mg every day

    200 mg every day

    Week 6

    100 mg every day

    150 mg every day

    300 mg every day

    Week 7

    150 mg every day

    200 mg every day

    400 mg every day

    Maintenance range (week 8 and onward)

    200 to 250 mg every dayc

    300 to 400 mg every dayc

    400 to 600 mg every dayc

    aValproate has been shown to inhibit glucuronidation and decrease the apparent clearance of lamotrigine [see Drug Interactions (7), Clinical Pharmacology (12.3)].

    b Drugs that induce lamotrigine glucuronidation and increase clearance, other than the specified antiepileptic drugs, include estrogen-containing oral contraceptives, rifampin, and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir. Dosing recommendations for oral contraceptives and the protease inhibitor atazanavir/ritonavir can be found in General Dosing Considerations [see Dosage and Administration (2.1)]. Patients on rifampin and the protease inhibitor lopinavir/ritonavir should follow the same dosing titration/maintenance regimen used with antiepileptic drugs that induce glucuronidation and increase clearance [see Dosage and Administration (2.1), Drug Interactions (7), and Clinical Pharmacology (12.3)].

    cDose increases at week 8 or later should not exceed 100 mg daily at weekly intervals.

    2.3 Conversion from Adjunctive Therapy to Monotherapy

    The goal of the transition regimen is to attempt to maintain seizure control while mitigating the risk of serious rash associated with the rapid titration of LAMICTAL XR.

    To avoid an increased risk of rash, the recommended maintenance dosage range of LAMICTAL XR as monotherapy is 250 to 300 mg given once daily.

    The recommended initial dose and subsequent dose escalations for LAMICTAL XR should not be exceeded [see Boxed Warning].

    Conversion from Adjunctive Therapy with Carbamazepine, Phenytoin, Phenobarbital, or Primidone to Monotherapy with LAMICTAL XR

    After achieving a dose of 500 mg/day of LAMICTAL XR using the guidelines in Table 1, the concomitant enzyme-inducing AED should be withdrawn by 20% decrements each week over a 4-week period. Two weeks after completion of withdrawal of the enzyme-inducing AED, the dosage of LAMICTAL XR may be decreased no faster than 100 mg/day each week to achieve the monotherapy maintenance dosage range of 250 to 300 mg/day.

    The regimen for the withdrawal of the concomitant AED is based on experience gained in the controlled monotherapy clinical trial using immediate-release lamotrigine.

    Conversion from Adjunctive Therapy with Valproate to Monotherapy with LAMICTAL XR

    The conversion regimen involves the 4 steps outlined in Table 2.

    Table 2. Conversion from Adjunctive Therapy with Valproate to Monotherapy with LAMICTAL XR in Patients Aged 13 Years and Older with Epilepsy

    LAMICTAL XR

    Valproate

    Step 1

    Achieve a dose of 150 mg/day according to guidelines in Table 1.

    Maintain established stable dose.

    Step 2

    Maintain at 150 mg/day.

    Decrease dose by decrements no greater than 500 mg/day/week to 500 mg/day and then maintain for 1 week.

    Step 3

    Increase to 200 mg/day.

    Simultaneously decrease to 250 mg/day and maintain for 1 week.

    Step 4

    Increase to 250 or 300 mg/day.

    Discontinue.

    Conversion from Adjunctive Therapy with Antiepileptic Drugs other than Carbamazepine, Phenytoin, Phenobarbital, Primidone, or Valproate to Monotherapy with LAMICTAL XR

    After achieving a dosage of 250 to 300 mg/day of LAMICTAL XR using the guidelines in Table 1, the concomitant AED should be withdrawn by 20% decrements each week over a 4-week period. No adjustment to the monotherapy dose of LAMICTAL XR is needed.

    2.4 Conversion from Immediate-Release Lamotrigine Tablets to LAMICTAL XR

    Patients may be converted directly from immediate-release lamotrigine to LAMICTAL XR extended-release tablets. The initial dose of LAMICTAL XR should match the total daily dose of immediate-release lamotrigine. However, some subjects on concomitant enzyme-inducing agents may have lower plasma levels of lamotrigine on conversion and should be monitored [see Clinical Pharmacology (12.3)].

    Following conversion to LAMICTAL XR, all patients (but especially those on drugs that induce lamotrigine glucuronidation) should be closely monitored for seizure control [see Drug Interactions (7)]. Depending on the therapeutic response after conversion, the total daily dose may need to be adjusted within the recommended dosing instructions (see Table 1).

  • Rodan And Fields Redefi...
    Rodan And Fields Redefine Age Shield Hand Shield Balm Spf30 (Octisalate, Avobenzone, Homosalate, Octocrylene) Emulsion [Rodan And Fields]

    Rodan And Fields Redefine Age Shield Hand Shield Balm Spf30

    Rodan And Fields Redefine Age Shield Hand Shield Balm Spf30 (Octisalate, Avobenzone, Homosalate, Octocrylene) Emulsion [Rodan And Fields]

    The usual dose of DYAZIDE is one or two capsules given once daily, with appropriate monitoring of serum potassium and of the clinical effect (see WARNINGS, Hyperkalemia).

  • Terazosin Hydrochloride Anhydrous Capsule [Mylan Pharmaceuticals Inc.]

    Terazosin Hydrochloride Anhydrous

    Terazosin Hydrochloride Anhydrous Capsule [Mylan Pharmaceuticals Inc.]

    2.1 Patient Selection

    Confirm the presence of BRAF V600E mutation in tumor specimens prior to initiation of treatment with TAFINLAR as a single agent [see Warnings and Precautions (5.2)]. Confirm the presence of BRAF V600E or V600K mutation in tumor specimens prior to initiation of treatment with TAFINLAR in combination with trametinib. Information on FDA-approved tests for the detection of BRAF V600 mutations in melanoma is available at: http://www.fda.gov/CompanionDiagnostics.

    2.2 Recommended Dosing

    The recommended dosage regimens of TAFINLAR are:

    • 150 mg orally taken twice daily, approximately 12 hours apart, as a single agent • 150 mg orally taken twice daily, approximately 12 hours apart, in combination with trametinib 2 mg orally taken once daily

    Continue treatment until disease progression or unacceptable toxicity occurs. Take TAFINLAR as a single agent, or TAFINLAR in combination with trametinib, at least 1 hour before or 2 hours after a meal[see Clinical Pharmacology (12.3)]. Do not take a missed dose of TAFINLAR within 6 hours of the next dose of TAFINLAR. Do not open, crush, or break TAFINLAR capsule.

    When administered in combination with trametinib, take the once-daily dose of trametinib at the same time each day with either the morning dose or the evening dose of TAFINLAR.

    2.3 Dose Modifications

    For New Primary Cutaneous Malignancies: No dose modifications are required.

    For New Primary Non-Cutaneous Malignancies: Permanently discontinue TAFINLAR in patients who develop RAS mutation-positive non-cutaneous malignancies. If used in combination with trametinib, no dose modifications are required for trametinib in patients who develop non-cutaneous malignancies.

    Table 1. Recommended Dose Reductions   Dose Reductions for TAFINLAR When Administered as a Single Agent or in Combination With Trametinib   First Dose Reduction   100 mg orally twice daily   Second Dose Reduction   75 mg orally twice daily   Third Dose Reduction   50 mg orally twice daily   Subsequent Modification   Permanently discontinue TAFINLAR if unable to tolerate 50 mg orally twice daily   Dose Reductions for Trametinib When Administered in Combination With TAFINLAR   First Dose Reduction   1.5 mg orally once daily   Second Dose Reduction   1 mg orally once daily   Subsequent Modification   Permanently discontinue if unable to tolerate trametinib 1 mg orally once daily Table 2. Recommended Dose Modifications for TAFINLAR as a Single Agent and for TAFINLAR and Trametinib Administered in Combination

    Severity of Adverse

    Reactiona

    TAFINLARb

    Trametinib

    (When Used in Combination)b,c

    Febrile drug reaction

    • Fever of 101.3°F to 104°F

    Withhold TAFINLAR until fever resolves. Then resume at same or lower dose level.

    Do not modify the dose of trametinib.

    • Fever higher than 104°F • Fever complicated by rigors, hypotension, dehydration, or renal failure • Withhold TAFINLAR until fever resolves. Then resume at a lower dose level.

    Or

    • Permanently discontinue TAFINLAR.

    Withhold trametinib until fever resolves. Then resume trametinib at same or lower dose level.

    Cutaneous

    • Intolerable Grade 2 skin toxicity • Grade 3 or 4 skin toxicity

    Withhold TAFINLAR for up to 3 weeks.

    • If improved, resume at a lower dose level. • If not improved, permanently discontinue.

    Withhold trametinib for up to 3 weeks.

    • If improved, resume at a lower dose level. • If not improved, permanently discontinue.

    Cardiac

    • Asymptomatic, absolute decrease in LVEF of 10% or greater from baseline and is below institutional lower limits of normal (LLN) from pretreatment value

    Do not modify the dose of TAFINLAR.

    Withhold trametinib for up to 4 weeks.

    • If improved to normal LVEF value, resume at a lower dose level. • If not improved to normal LVEF value, permanently discontinue. • Symptomatic congestive heart failure • Absolute decrease in LVEF of greater than 20% from baseline that is below LLN

    Withhold TAFINLAR, if improved, then resume at the same dose.

    Permanently discontinue trametinib.

    Venous Thromboembolism

    • Uncomplicated DVT or PE

    Do not modify the dose of TAFINLAR.

    Withhold trametinib for up to 3 weeks.

    • If improved to Grade 0-1, resume at a lower dose level. • If not improved, permanently discontinue. • Life Threatening PE

    Permanently discontinue TAFINLAR.

    Permanently discontinue trametinib.

    Ocular Toxicities

    • Grade 2-3 retinal pigment epithelial detachments (RPED)

    Do not modify the dose of TAFINLAR.

    Withhold trametinib for up to 3 weeks.

    • If improved to Grade 0-1, resume at a lower dose level. • If not improved, permanently discontinue. • Retinal vein occlusion

    Do not modify the dose of TAFINLAR.

    Permanently discontinue trametinib.

    • Uveitis and Iritis

    Withhold TAFINLAR for up to 6 weeks.

    • If improved to Grade 0-1, then resume at the same dose. • If not improved, permanently discontinue.

    Do not modify the dose of trametinib.

    Pulmonary

    • Interstitial lung disease/pneumonitis

    Do not modify the dose of TAFINLAR.

    Permanently discontinue trametinib.

    Other

    • Intolerable Grade 2 adverse reactions • Any Grade 3 adverse reaction

    Withhold TAFINLAR.

    • If improved to Grade 0-1, resume at a lower dose level. • If not improved, permanently discontinue.

    Withhold trametinib for up to 3 weeks.

    • If improved to Grade 0-1, resume at a lower dose level. • If not improved, permanently discontinue. • First occurrence of any Grade 4 adverse reaction • Withhold TAFINLAR until adverse reaction improves to Grade 0-1. Then resume at a lower dose level.

    Or

    • Permanently discontinue TAFINLAR. • Withhold trametinib until adverse reaction improves to Grade 0-1. Then resume at a lower dose level.

    Or

    • Permanently discontinue trametinib. • Recurrent Grade 4 adverse reaction

    Permanently discontinue TAFINLAR.

    Permanently discontinue trametinib.

    aNational Cancer Institute Common Terminology Criteria for Adverse Events (CTCAE) version 4.0.

    bSee Table 1 for recommended dose reductions of TAFINLAR and trametinib.

    cRefer to Full Prescribing Information for trametinib.

  • Valtrex
    Valtrex (Valacyclovir Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    Valtrex

    Valtrex (Valacyclovir Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    • VALTREX may be given without regard to meals. • Valacyclovir oral suspension (25 mg/mL or 50 mg/mL) may be prepared extemporaneously from 500-mg VALTREX Caplets for use in pediatric patients for whom a solid dosage form is not appropriate [see Dosage and Administration (2.3)].

    2.1 Adult Dosing Recommendations

    Cold Sores (Herpes Labialis): The recommended dosage of VALTREX for treatment of cold sores is 2 grams twice daily for 1 day taken 12 hours apart. Therapy should be initiated at the earliest symptom of a cold sore (e.g., tingling, itching, or burning).

    Genital Herpes: Initial Episode: The recommended dosage of VALTREX for treatment of initial genital herpes is 1 gram twice daily for 10 days. Therapy was most effective when administered within 48 hours of the onset of signs and symptoms.

    Recurrent Episodes: The recommended dosage of VALTREX for treatment of recurrent genital herpes is 500 mg twice daily for 3 days. Initiate treatment at the first sign or symptom of an episode.

    Suppressive Therapy: The recommended dosage of VALTREX for chronic suppressive therapy of recurrent genital herpes is 1 gram once daily in patients with normal immune function. In patients with a history of 9 or fewer recurrences per year, an alternative dose is 500 mg once daily.

    In HIV─1─infected patients with a CD4+ cell count greater than or equal to 100 cells/mm3, the recommended dosage of VALTREX for chronic suppressive therapy of recurrent genital herpes is 500 mg twice daily.

    Reduction of Transmission: The recommended dosage of VALTREX for reduction of transmission of genital herpes in patients with a history of 9 or fewer recurrences per year is 500 mg once daily for the source partner.

    Herpes Zoster: The recommended dosage of VALTREX for treatment of herpes zoster is 1 gram 3 times daily for 7 days. Therapy should be initiated at the earliest sign or symptom of herpes zoster and is most effective when started within 48 hours of the onset of rash.

    2.2 Pediatric Dosing Recommendations

    Cold Sores (Herpes Labialis): The recommended dosage of VALTREX for the treatment of cold sores in pediatric patients aged greater than or equal to 12 years is 2 grams twice daily for 1 day taken 12 hours apart. Therapy should be initiated at the earliest symptom of a cold sore (e.g., tingling, itching, or burning).

    Chickenpox: The recommended dosage of VALTREX for treatment of chickenpox in immunocompetent pediatric patients aged 2 to less than 18 years is 20 mg/kg administered 3 times daily for 5 days. The total dose should not exceed 1 gram 3 times daily. Therapy should be initiated at the earliest sign or symptom [see Use in Specific Populations (8.4), Clinical Pharmacology (12.3), Clinical Studies (14.4)].

    2.3 Extemporaneous Preparation of Oral Suspension

    Ingredients and Preparation per USP─NF: VALTREX Caplets 500 mg, cherry flavor, and Suspension Structured Vehicle USP─NF (SSV). Valacyclovir oral suspension (25 mg/mL or 50 mg/mL) should be prepared in lots of 100 mL.

    Prepare Suspension at Time of Dispensing as Follows:

    • Prepare SSV according to the USP-NF. • Using a pestle and mortar, grind the required number of VALTREX 500 mg Caplets until a fine powder is produced (5 VALTREX Caplets for 25 mg/mL suspension; 10 VALTREX Caplets for 50 mg/mL suspension). • Gradually add approximately 5-mL aliquots of SSV to the mortar and triturate the powder until a paste has been produced. Ensure that the powder has been adequately wetted. • Continue to add approximately 5-mL aliquots of SSV to the mortar, mixing thoroughly between additions, until a concentrated suspension is produced, to a minimum total quantity of 20 mL SSV and a maximum total quantity of 40 mL SSV for both the 25-mg/mL and 50─mg/mL suspensions. • Transfer the mixture to a suitable 100-mL measuring flask. • Transfer the cherry flavor* to the mortar and dissolve in approximately 5 mL of SSV. Once dissolved, add to the measuring flask. • Rinse the mortar at least 3 times with approximately 5-mL aliquots of SSV, transferring the rinsing to the measuring flask between additions. • Make the suspension to volume (100 mL) with SSV and shake thoroughly to mix. • Transfer the suspension to an amber glass medicine bottle with a child─resistant closure. • The prepared suspension should be labeled with the following information “Shake well before using. Store suspension between 2° to 8°C (36° to 46°F) in a refrigerator. Discard after 28 days.”

    *The amount of cherry flavor added is as instructed by the suppliers of the cherry flavor.

    2.4 Patients With Renal Impairment

    Dosage recommendations for adult patients with reduced renal function are provided in Table 1 [see Use in Specific Populations (8.5, 8.6), Clinical Pharmacology (12.3)]. Data are not available for the use of VALTREX in pediatric patients with a creatinine clearance less than 50 mL/min/1.73 m2.

    Table 1. VALTREX Dosage Recommendations for Adults With Renal Impairment

    Indications

    Normal Dosage

    Regimen

    (Creatinine Clearance ≥50 mL/min)

    Creatinine Clearance (mL/min)

    30-49

    10-29

    <10

    Cold sores (Herpes labialis)


    Do not exceed 1 day of treatment.

    Two 2 gram doses taken 12 hours apart

    Two 1 gram doses taken 12 hours apart

    Two 500 mg doses taken 12 hours apart

    500 mg single dose

    Genital herpes:

     Initial episode

    1 gram every 12 hours

    no reduction

    1 gram every 24 hours

    500 mg every 24 hours

    Genital herpes:

     Recurrent episode

    500 mg every 12 hours

    no reduction

    500 mg every 24 hours

    500 mg every 24 hours

    Genital herpes:

     Suppressive therapy

       Immunocompetent patients


    1 gram every 24 hours

    no reduction

    500 mg every 24 hours

    500 mg every 24 hours

       Alternate dose for immunocompetent patients with less than or equal to 9 recurrences/year

    500 mg every 24 hours

    no reduction

    500 mg every 48 hours

    500 mg every 48 hours

       HIV─1─infected patients

    500 mg every 12 hours

    no reduction

    500 mg every 24 hours

    500 mg every 24 hours

    Herpes zoster

    1 gram every 8 hours

    1 gram every 12 hours

    1 gram every 24 hours

    500 mg every 24 hours

    Hemodialysis: Patients requiring hemodialysis should receive the recommended dose of VALTREX after hemodialysis. During hemodialysis, the half─life of acyclovir after administration of VALTREX is approximately 4 hours. About one-third of acyclovir in the body is removed by dialysis during a 4─hour hemodialysis session.

    Peritoneal Dialysis: There is no information specific to administration of VALTREX in patients receiving peritoneal dialysis. The effect of chronic ambulatory peritoneal dialysis (CAPD) and continuous arteriovenous hemofiltration/dialysis (CAVHD) on acyclovir pharmacokinetics has been studied. The removal of acyclovir after CAPD and CAVHD is less pronounced than with hemodialysis, and the pharmacokinetic parameters closely resemble those observed in patients with end─stage renal disease (ESRD) not receiving hemodialysis. Therefore, supplemental doses of VALTREX should not be required following CAPD or CAVHD.

  • Malarone
    Malarone (Atovaquone And Proguanil Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    Malarone

    Malarone (Atovaquone And Proguanil Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    The daily dose should be taken at the same time each day with food or a milky drink. In the event of vomiting within 1 hour after dosing, a repeat dose should be taken.

    MALARONE may be crushed and mixed with condensed milk just prior to administration to patients who may have difficulty swallowing tablets.

    2.1 Prevention of Malaria

    Start prophylactic treatment with MALARONE 1 or 2 days before entering a malaria‑endemic area and continue daily during the stay and for 7 days after return.

    Adults: One MALARONE Tablet (adult strength = 250 mg atovaquone/100 mg proguanil hydrochloride) per day.

    Pediatric Patients: The dosage for prevention of malaria in pediatric patients is based upon body weight (Table 1).

    Table 1. Dosage for Prevention of Malaria in Pediatric Patients

    Weight

    (kg)

    Atovaquone/

    Proguanil HCl

    Total Daily Dose

    Dosage Regimen

    11-20

    62.5 mg/25 mg

    1 MALARONE Pediatric Tablet daily

    21-30

    125 mg/50 mg

    2 MALARONE Pediatric Tablets as a single daily dose

    31-40

    187.5 mg/75 mg

    3 MALARONE Pediatric Tablets as a single daily dose

    >40

    250 mg/100 mg

    1 MALARONE Tablet (adult strength) as a single daily dose

    2.2 Treatment of Acute Malaria

    Adults: Four MALARONE Tablets (adult strength; total daily dose 1 g atovaquone/400 mg proguanil hydrochloride) as a single daily dose for 3 consecutive days.

    Pediatric Patients: The dosage for treatment of acute malaria in pediatric patients is based upon body weight (Table 2).

    Table 2. Dosage for Treatment of Acute Malaria in Pediatric Patients

    Weight

    (kg)

    Atovaquone/

    Proguanil HCl

    Total Daily Dose

    Dosage Regimen

    5-8

    125 mg/50 mg

    2 MALARONE Pediatric Tablets daily for 3 consecutive days

    9-10

    187.5 mg/75 mg

    3 MALARONE Pediatric Tablets daily for 3 consecutive days

    11-20

    250 mg/100 mg

    1 MALARONE Tablet (adult strength) daily for 3 consecutive days

    21-30

    500 mg/200 mg

    2 MALARONE Tablets (adult strength) as a single daily dose for 3 consecutive days

    31-40

    750 mg/300 mg

    3 MALARONE Tablets (adult strength) as a single daily dose for 3 consecutive days

    >40

    1 g/400 mg

    4 MALARONE Tablets (adult strength) as a single daily dose for 3 consecutive days

    2.3 Renal Impairment

    Do not use MALARONE for malaria prophylaxis in patients with severe renal impairment (creatinine clearance <30 mL/min) [see Contraindications (4.2)]. Use with caution for the treatment of malaria in patients with severe renal impairment, only if the benefits of the 3-day treatment regimen outweigh the potential risks associated with increased drug exposure. No dosage adjustments are needed in patients with mild (creatinine clearance 50 to 80 mL/min) or moderate (creatinine clearance 30 to 50 mL/min) renal impairment. [See Clinical Pharmacology (12.3).]

  • Altabax (Retapamulin) Ointment [Glaxosmithkline Llc]

    Altabax

    Altabax (Retapamulin) Ointment [Glaxosmithkline Llc]

    A thin layer of ALTABAX should be applied to the affected area (up to 100 cm2 in total area in adults or 2% total body surface area in pediatric patients aged 9 months or older) twice daily for 5 days. The treated area may be covered with a sterile bandage or gauze dressing if desired [see Patient Counseling Information (17)].

  • Relenza (Zanamivir) Powder [Glaxosmithkline Llc]

    Relenza

    Relenza (Zanamivir) Powder [Glaxosmithkline Llc]

    2.1 Dosing Considerations

    • RELENZA is for administration to the respiratory tract by oral inhalation only, using the DISKHALER ® device provided [see Warnings and Precautions (5.6)]. • The 10-mg dose is provided by 2 inhalations (one 5-mg blister per inhalation). • Patients should be instructed in the use of the delivery system. Instructions should include a demonstration whenever possible. If RELENZA is prescribed for children, it should be used only under adult supervision and instruction, and the supervising adult should first be instructed by a healthcare professional [see Patient Counseling Information (17)]. • Patients scheduled to use an inhaled bronchodilator at the same time as RELENZA should use their bronchodilator before taking RELENZA [see Patient Counseling Information (17)].

    2.2 Treatment of Influenza

    • The recommended dose of RELENZA for treatment of influenza in adults and pediatric patients aged 7 years and older is 10 mg twice daily (approximately 12 hours apart) for 5 days. • Two doses should be taken on the first day of treatment whenever possible provided there is at least 2 hours between doses. • On subsequent days, doses should be about 12 hours apart (e.g., morning and evening) at approximately the same time each day. • The safety and efficacy of repeated treatment courses have not been studied.

    2.3 Prophylaxis of Influenza

    Household Setting:

    • The recommended dose of RELENZA for prophylaxis of influenza in adults and pediatric patients aged 5 years and older in a household setting is 10 mg once daily for 10 days. • The dose should be administered at approximately the same time each day. • There are no data on the effectiveness of prophylaxis with RELENZA in a household setting when initiated more than 1.5 days after the onset of signs or symptoms in the index case.

    Community Outbreaks:

    • The recommended dose of RELENZA for prophylaxis of influenza in adults and adolescents in a community setting is 10 mg once daily for 28 days. • The dose should be administered at approximately the same time each day. • There are no data on the effectiveness of prophylaxis with RELENZA in a community outbreak when initiated more than 5 days after the outbreak was identified in the community. • The safety and effectiveness of prophylaxis with RELENZA have not been evaluated for longer than 28 days’ duration.
  • Advair Hfa
    Advair Hfa (Fluticasone Propionate And Salmeterol Xinafoate) Aerosol, Metered [Glaxosmithkline Llc]

    Advair Hfa

    Advair Hfa (Fluticasone Propionate And Salmeterol Xinafoate) Aerosol, Metered [Glaxosmithkline Llc]

    ADVAIR HFA should be administered as 2 inhalations twice daily by the orally inhaled route only. After inhalation, the patient should rinse his/her mouth with water without swallowing to help reduce the risk of oropharyngeal candidiasis.

    More frequent administration or a greater number of inhalations (more than 2 inhalations twice daily) of the prescribed strength of ADVAIR HFA is not recommended as some patients are more likely to experience adverse effects with higher doses of salmeterol. Patients using ADVAIR HFA should not use additional LABA for any reason. [See Warnings and Precautions (5.3, 5.12).]

    If asthma symptoms arise in the period between doses, an inhaled, short-acting beta2-agonist should be taken for immediate relief.

    For patients aged 12 years and older, the dosage is 2 inhalations twice daily, approximately 12 hours apart.

    The recommended starting dosages for ADVAIR HFA for patients aged 12 years and older are based upon patients’ asthma severity.

    The maximum recommended dosage is 2 inhalations of ADVAIR HFA 230/21 twice daily.

    Improvement in asthma control following inhaled administration of ADVAIR HFA can occur within 30 minutes of beginning treatment, although maximum benefit may not be achieved for 1 week or longer after starting treatment. Individual patients will experience a variable time to onset and degree of symptom relief.

    For patients who do not respond adequately to the starting dosage after 2 weeks of therapy, replacing the current strength of ADVAIR HFA with a higher strength may provide additional improvement in asthma control.

    If a previously effective dosage regimen fails to provide adequate improvement in asthma control, the therapeutic regimen should be reevaluated and additional therapeutic options (e.g., replacing the current strength of ADVAIR HFA with a higher strength, adding additional inhaled corticosteroid, initiating oral corticosteroids) should be considered.

    Prime ADVAIR HFA before using for the first time by releasing 4 sprays into the air away from the face, shaking well for 5 seconds before each spray. In cases where the inhaler has not been used for more than 4 weeks or when it has been dropped, prime the inhaler again by releasing 2 sprays into the air away from the face, shaking well for 5 seconds before each spray.

  • Hycamtin
    Hycamtin (Topotecan Hydrochloride) Capsule [Glaxosmithkline Llc]

    Hycamtin

    Hycamtin (Topotecan Hydrochloride) Capsule [Glaxosmithkline Llc]

    2.1 Recommended Dosing

    The recommended dose of HYCAMTIN capsules is 2.3 mg/m2/day orally once daily for 5 consecutive days repeated every 21 days. Round the dose to the nearest 0.25 mg, and prescribe the minimum number of 1-mg and 0.25-mg capsules. Prescribe the same number of capsules for each of the 5 dosing days.

    Take HYCAMTIN capsules with or without food. Swallow capsules whole. Do not chew, crush, or divide the capsules. Do not prescribe a replacement dose for emesis.

    Diarrhea:

    Do not administer HYCAMTIN capsules to patients with Grade 3 or 4 diarrhea. After recovery to Grade 1 or less, reduce the dose of HYCAMTIN by 0.4 mg/m2/day for subsequent courses [see Warnings and Precautions (5.2)].

    2.2 Dose Modification Guidelines

    Hematologic Toxicities:

      Do not administer subsequent courses of HYCAMTIN capsules until neutrophils recover to greater than 1,000 cells/mm3, platelets recover to greater than 100,000 cells/mm3, hemoglobin levels recover to greater than or equal to 9.0 g/dL (with transfusion if necessary). • Dose reduce HYCAMTIN capsules by 0.4 mg/m2/day for:   neutrophil counts of less than 500 cells/mm3 associated with fever or infection or lasting for 7 days or more;   neutrophil counts of 500 to 1,000 cells/mm3 lasting beyond day 21 of the treatment course;   platelet counts less than 25,000 cells/mm3.   Renal Impairment:   The recommended starting doses of HYCAMTIN capsules in patients with moderate and severe renal impairment are as follows: Table 1. Dose Reduction Guidelines for Renal Impairment   Degree of Renal Impairment   Creatinine Clearancea   (mL/min)   Dose   (mg/m2)/day   Moderate   30 – 49   1.5 b   Severe   <30   0.6 b

    aCalculated with the Cockroft-Gault method using ideal body weight.

    bDose can be increased after the first course by 0.4 mg/m2/day if no severe hematologic or gastrointestinal toxicities occur.

  • Potiga (Ezogabine) Tablet, Film Coated [Glaxosmithkline Llc]

    Potiga

    Potiga (Ezogabine) Tablet, Film Coated [Glaxosmithkline Llc]

    Verify dose using body surface area prior to dispensing. Recommended dosage should generally not exceed 4 mg intravenously [see Overdosage (10)].

    2.1 Ovarian Cancer

    Recommended Dose and Schedule

    The recommended dose of HYCAMTIN is 1.5 mg/m2 by intravenous infusion over 30 minutes daily for 5 consecutive days, starting on Day 1 of a 21‑day course.

    2.2 Small Cell Lung Cancer

    Recommended Dose and Schedule

    The recommended dose of HYCAMTIN is 1.5 mg/m2 by intravenous infusion over 30 minutes daily for 5 consecutive days, starting on Day 1 of a 21-day course.

    2.3 Cervical Cancer

    Recommended Dose and Schedule

    The recommended dose of HYCAMTIN is 0.75 mg/m2 by intravenous infusion over 30 minutes daily on Days 1, 2, and 3 in combination with cisplatin 50 mg/m2 on Day 1, repeated every 21 days.

    2.4 Dose Modifications

    Hematologic Toxicities

    For single-agent use, dose reduce HYCAMTIN to 1.25 mg/m2 for:

    • neutrophil counts of less than 500 cells/mm 3, or administer granulocyte-colony stimulating factor (G-CSF) starting no sooner than 24 hours following the last dose of HYCAMTIN. • platelet counts less than 25,000 cells/mm 3 during previous cycle.

    For combination use with cisplatin, dose reduce HYCAMTIN to 0.60 mg/m2 (and further to 0.45 mg/m2 if necessary) for:

    • febrile neutropenia (defined as neutrophil counts less than 1,000 cells/mm 3 with temperature of greater than or equal to 38.0°C (100.4°F), or administer G‑CSF starting no sooner than 24 hours following the last dose of HYCAMTIN. • platelet counts less than 25,000 cells/mm 3 during previous cycle.

    Renal Impairment

    For single-agent use, dose reduce HYCAMTIN to 0.75 mg/m2 in patients with moderate renal impairment (creatinine clearance [Clcr] = 20 to 39 mL/min). Insufficient data are available in patients with severe renal impairment (Clcr less than 20 mL/min) to provide a dosage recommendation for HYCAMTIN [see Use in Specific Populations (8.6), Clinical Pharmacology (12.3)].

    2.5 Preparation and Intravenous Administration

    HYCAMTIN is a cytotoxic drug. Follow applicable special handling and disposable procedures.1

    Preparation and Administration

    Reconstitute each 4-mg vial of HYCAMTIN with 4 mL Sterile Water for Injection, USP. Dilute the appropriate volume of the reconstituted solution in either 0.9% Sodium Chloride Intravenous Infusion, USP or 5% Dextrose in Water Injection, USP prior to administration.

    Stability

    Unopened vials of HYCAMTIN are stable until the date indicated on the package when stored between 20°C and 25°C (68°F and 77°F) [see USP] and protected from light in the original carton. Because the vials contain no preservative, contents should be used immediately after reconstitution.

    Reconstituted vials of HYCAMTIN diluted for infusion are stable at approximately 20°C to 25°C (68°F to 77°F) and ambient lighting conditions for 24 hours.

  • Tanzeum (Albiglutide) Injection, Powder, Lyophilized, For Solution [Glaxosmithkline Llc]

    Tanzeum

    Tanzeum (Albiglutide) Injection, Powder, Lyophilized, For Solution [Glaxosmithkline Llc]

    2.1 Dosage

    The recommended dosage of TANZEUM is 30 mg once weekly given as a subcutaneous injection in the abdomen, thigh, or upper arm region. The dosage may be increased to 50 mg once weekly if the glycemic response is inadequate.

    TANZEUM may be administered at any time of day without regard to meals. Instruct patients to administer TANZEUM once a week on the same day each week. The day of weekly administration may be changed if necessary as long as the last dose was administered 4 or more days before.

    If a dose is missed, instruct patients to administer as soon as possible within 3 days after the missed dose. Thereafter, patients can resume dosing on their usual day of administration. If it is more than 3 days after the missed dose, instruct patients to wait until their next regularly scheduled weekly dose.

    2.2 Concomitant Use with an Insulin Secretagogue (e.g., Sulfonylurea) or with Insulin

    When initiating TANZEUM, consider reducing the dosage of concomitantly administered insulin secretagogues (e.g., sulfonylureas) or insulin to reduce the risk of hypoglycemia [see Warnings and Precautions (5.3)].

    2.3 Dosage in Patients with Renal Impairment

    No dose adjustment is needed in patients with mild, moderate, or severe renal impairment (eGFR 15 to 89 mL/min/1.73 m2). Use caution when initiating or escalating doses of TANZEUM in patients with renal impairment. Monitor renal function in patients with renal impairment reporting severe adverse gastrointestinal reactions [see Warnings and Precautions (5.5), Use in Specific Populations (8.6)].

    2.4 Reconstitution of the Lyophilized Powder

    The lyophilized powder contained within the Pen must be reconstituted prior to administration. See Patient Instructions for Use for complete administration instructions with illustrations. The instructions may also be found at www.TANZEUM.com. Instruct patients as follows:

    Pen Reconstitution

    • Hold the Pen body with the clear cartridge pointing up to see the [1] in the number window. • To reconstitute the lyophilized powder with the diluent in the Pen, twist the clear cartridge on the Pen in the direction of the arrow until the Pen is felt/heard to “click” into place and the [2] is seen in the number window. This mixes the diluent with the lyophilized powder. • Slowly and gently rock the Pen side-to-side 5 times to mix the reconstituted solution of TANZEUM. Advise the patient to not shake the Pen hard to avoid foaming. • Wait 15 minutes for the 30-mg Pen and 30 minutes for the 50-mg Pen to ensure that the reconstituted solution is mixed.

    Preparing Pen for Injection

    • Slowly and gently rock the Pen side-to-side 5 additional times to mix the reconstituted solution. • Visually inspect the reconstituted solution in the viewing window for particulate matter. The reconstituted solution will be yellow in color. After reconstitution, use TANZEUM within 8 hours. • Holding the Pen upright, attach the needle to the Pen. Gently tap the clear cartridge to bring large bubbles to the top.

    See Dosage and Administration (2.5) for important administration instructions, including the injection procedure.

    Alternate Method of Reconstitution (Healthcare Professional Use Only)

    The Patient Instructions for Use provide directions for the patient to wait 15 minutes for the 30-mg Pen and 30 minutes for the 50-mg Pen after the lyophilized powder and diluent are mixed to ensure reconstitution.

    Healthcare professionals may utilize the following alternate method of reconstitution. Because this method relies on appropriate swirling and visual inspection of the solution, it should only be performed by healthcare professionals.

    • Follow Step A (Inspect Your Pen and Mix Your Medication) in the Instructions for Use. Make sure you have: • Inspected the Pen for [1] in the number window and expiration date. • Twisted the clear cartridge until [2] appears in the number window and a “click” is heard. This combines the medicine powder and liquid in the clear cartridge. • Hold the Pen with the clear cartridge pointing up and maintain this orientation throughout the reconstitution. • Gently swirl the Pen in small circular motions for at least one minute. Avoid shaking as this can result in foaming, which may affect the dose. • Inspect the solution, and if needed, continue to gently swirl the Pen until all the powder is dissolved and you see a clear yellow solution that is free of particles. A small amount of foam, on top of the solution at the end of reconstitution, is normal. • For 30-mg Pen: Complete dissolution usually occurs within 2 minutes but may take up to 5 minutes, as confirmed by visual inspection for a clear yellow solution free of particles.  • For 50-mg Pen: Complete dissolution usually occurs within 7 minutes but may take up to 10 minutes. • After reconstitution, continue to follow the steps in the Instructions for Use, starting at Step B: Attach the Needle.

    2.5 Important Administration Instructions

    Instruct patients as follows:

    • The pen should be used within 8 hours of reconstitution prior to attaching the needle. • After attaching the supplied needle, remove air bubbles by slowly twisting the Pen until you see the [3] in the number window. At the same time, the injection button will be automatically released from the bottom of the Pen. • Use immediately after the needle is attached and primed. The product can clog the needle if allowed to dry in the primed needle. • After subcutaneously inserting the needle into the skin in the abdomen, thigh, or upper arm region, press the injection button. Hold the injection button until you hear a “click” and then hold the button for 5 additional seconds to deliver the full dose.

    When using TANZEUM with insulin, instruct patients to administer as separate injections and to never mix the products. It is acceptable to inject TANZEUM and insulin in the same body region but the injections should not be adjacent to each other.

    When injecting in the same body region, advise patients to use a different injection site each week. TANZEUM must not be administered intravenously or intramuscularly.

  • Incruse Ellipta (Umeclidinium) Aerosol, Powder [Glaxosmithkline Llc]

    Incruse Ellipta

    Incruse Ellipta (Umeclidinium) Aerosol, Powder [Glaxosmithkline Llc]

    INCRUSE ELLIPTA (umeclidinium 62.5 mcg) should be administered as 1 inhalation once daily by the orally inhaled route only.

    INCRUSE ELLIPTA should be taken at the same time every day. Do not use INCRUSE ELLIPTA more than 1 time every 24 hours.

    No dosage adjustment is required for geriatric patients, patients with renal impairment, or patients with moderate hepatic impairment [see Clinical Pharmacology (12.3)].

  • Wellbutrin (Bupropion Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    Wellbutrin

    Wellbutrin (Bupropion Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    2.1 General Instructions for Use

    To minimize the risk of seizure, increase the dose gradually [see Warnings and Precautions (5.3)]. Increases in dose should not exceed 100 mg per day in a 3‑day period. WELLBUTRIN Tablets should be swallowed whole and not crushed, divided, or chewed. WELLBUTRIN may be taken with or without food.

    The recommended starting dose is 200 mg per day, given as 100 mg twice daily. After 3 days of dosing, the dose may be increased to 300 mg per day, given as 100 mg 3 times daily, with at least 6 hours between successive doses. Dosing above 300 mg per day may be accomplished using the 75- or 100-mg tablets.

    A maximum of 450 mg per day, given in divided doses of not more than 150 mg each, may be considered for patients who show no clinical improvement after several weeks of treatment at 300 mg per day. Administer the 100‑mg tablet 4 times daily to not exceed the limit of 150 mg in a single dose.

    It is generally agreed that acute episodes of depression require several months or longer of antidepressant drug treatment beyond the response in the acute episode. It is unknown whether the dose of WELLBUTRIN needed for maintenance treatment is identical to the dose that provided an initial response. Periodically reassess the need for maintenance treatment and the appropriate dose for such treatment.

    2.2 Dose Adjustment in Patients with Hepatic Impairment

    In patients with moderate to severe hepatic impairment (Child-Pugh score: 7 to 15), the maximum dose of WELLBUTRIN is 75 mg per day. In patients with mild hepatic impairment (Child-Pugh score: 5 to 6), consider reducing the dose and/or frequency of dosing [see Use in Specific Populations (8.7), Clinical Pharmacology (12.3)].

    2.3 Dose Adjustment in Patients with Renal Impairment

    Consider reducing the dose and/or frequency of WELLBUTRIN in patients with renal impairment (Glomerular Filtration Rate <90 mL/min) [see Use in Specific Populations (8.6), Clinical Pharmacology (12.3)].

    2.4 Switching a Patient to or from a Monoamine Oxidase Inhibitor (MAOI) Antidepressant

    At least 14 days should elapse between discontinuation of an MAOI intended to treat depression and initiation of therapy with WELLBUTRIN. Conversely, at least 14 days should be allowed after stopping WELLBUTRIN before starting an MAOI antidepressant [see Contraindications (4), Drug Interactions (7.6)].

    2.5 Use of WELLBUTRIN with Reversible MAOIs Such as Linezolid or Methylene Blue

    Do not start WELLBUTRIN in a patient who is being treated with a reversible MAOI such as linezolid or intravenous methylene blue. Drug interactions can increase the risk of hypertensive reactions. In a patient who requires more urgent treatment of a psychiatric condition, non-pharmacological interventions, including hospitalization, should be considered [see Contraindications (4), Drug Interactions (7.6)].

    In some cases, a patient already receiving therapy with WELLBUTRIN may require urgent treatment with linezolid or intravenous methylene blue. If acceptable alternatives to linezolid or intravenous methylene blue treatment are not available and the potential benefits of linezolid or intravenous methylene blue treatment are judged to outweigh the risks of hypertensive reactions in a particular patient, WELLBUTRIN should be stopped promptly, and linezolid or intravenous methylene blue can be administered. The patient should be monitored for 2 weeks or until 24 hours after the last dose of linezolid or intravenous methylene blue, whichever comes first. Therapy with WELLBUTRIN may be resumed 24 hours after the last dose of linezolid or intravenous methylene blue.

    The risk of administering methylene blue by non-intravenous routes (such as oral tablets or by local injection) or in intravenous doses much lower than 1 mg/kg with WELLBUTRIN is unclear. The clinician should, nevertheless, be aware of the possibility of a drug interaction with such use [see Contraindications (4), Drug Interactions (7.6)].

  • Wellbutrin Sr
    Wellbutrin Sr (Bupropion Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    Wellbutrin Sr

    Wellbutrin Sr (Bupropion Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    2.1 General Instructions for Use

    To minimize the risk of seizure, increase the dose gradually [see Warnings and Precautions (5.3)]. WELLBUTRIN SR Tablets should be swallowed whole and not crushed, divided, or chewed. WELLBUTRIN SR may be taken with or without food.

    The usual adult target dose for WELLBUTRIN SR is 300 mg per day, given as 150 mg twice daily. Initiate dosing with 150 mg per day given as a single daily dose in the morning. After 3 days of dosing, the dose may be increased to the 300-mg-per-day target dose, given as 150 mg twice daily. There should be an interval of at least 8 hours between successive doses. A maximum of 400 mg per day, given as 200 mg twice daily, may be considered for patients in whom no clinical improvement is noted after several weeks of treatment at 300 mg per day. To avoid high peak concentrations of bupropion and/or its metabolites, do not exceed 200 mg in any single dose.

    It is generally agreed that acute episodes of depression require several months or longer of antidepressant drug treatment beyond the response in the acute episode. It is unknown whether the dose of WELLBUTRIN SR needed for maintenance treatment is identical to the dose that provided an initial response. Periodically reassess the need for maintenance treatment and the appropriate dose for such treatment.

    2.2 Dose Adjustment in Patients with Hepatic Impairment

    In patients with moderate to severe hepatic impairment (Child-Pugh score: 7 to 15), the maximum dose of WELLBUTRIN SR is 100 mg per day or 150 mg every other day. In patients with mild hepatic impairment (Child-Pugh score: 5 to 6), consider reducing the dose and/or frequency of dosing [see Use in Specific Populations (8.7), Clinical Pharmacology (12.3)].

    2.3 Dose Adjustment in Patients with Renal Impairment

    Consider reducing the dose and/or frequency of WELLBUTRIN SR in patients with renal impairment (Glomerular Filtration Rate <90 mL/min) [see Use in Specific Populations (8.6), Clinical Pharmacology (12.3)].

    2.4 Switching a Patient to or from a Monoamine Oxidase Inhibitor (MAOI) Antidepressant

    At least 14 days should elapse between discontinuation of an MAOI intended to treat depression and initiation of therapy with WELLBUTRIN SR. Conversely, at least 14 days should be allowed after stopping WELLBUTRIN SR before starting an MAOI antidepressant [see Contraindications (4), Drug Interactions (7.6)].

    2.5 Use of WELLBUTRIN SR with Reversible MAOIs Such as Linezolid or Methylene Blue

    Do not start WELLBUTRIN SR in a patient who is being treated with a reversible MAOI such as linezolid or intravenous methylene blue. Drug interactions can increase the risk of hypertensive reactions. In a patient who requires more urgent treatment of a psychiatric condition, non-pharmacological interventions, including hospitalization, should be considered [see Contraindications (4), Drug Interactions (7.6)].

    In some cases, a patient already receiving therapy with WELLBUTRIN SR may require urgent treatment with linezolid or intravenous methylene blue. If acceptable alternatives to linezolid or intravenous methylene blue treatment are not available and the potential benefits of linezolid or intravenous methylene blue treatment are judged to outweigh the risks of hypertensive reactions in a particular patient, WELLBUTRIN SR should be stopped promptly, and linezolid or intravenous methylene blue can be administered. The patient should be monitored for 2 weeks or until 24 hours after the last dose of linezolid or intravenous methylene blue, whichever comes first. Therapy with WELLBUTRIN SR may be resumed 24 hours after the last dose of linezolid or intravenous methylene blue.

    The risk of administering methylene blue by non-intravenous routes (such as oral tablets or by local injection) or in intravenous doses much lower than 1 mg/kg with WELLBUTRIN SR is unclear. The clinician should, nevertheless, be aware of the possibility of a drug interaction with such use [see Contraindications (4), Drug Interactions (7.6)].

  • Rythmol
    Rythmol (Propafenone Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    Rythmol

    Rythmol (Propafenone Hydrochloride) Tablet, Film Coated [Glaxosmithkline Llc]

    The dose of RYTHMOL must be individually titrated on the basis of response and tolerance. Initiate therapy with RYTHMOL 150 mg given every 8 hours (450 mg/day). Dosage may be increased at a minimum of 3 to 4 day intervals to 225 mg every 8 hours (675 mg/day). If additional therapeutic effect is needed, the dose of RYTHMOL may be increased to 300 mg every 8 hours (900 mg/day). The usefulness and safety of dosages exceeding 900 mg per day have not been established.

    In patients with hepatic impairment or those with significant widening of the QRS complex or second- or third-degree AV block, consider reducing the dose.

    As with other antiarrhythmic agents, in the elderly or in ventricular arrhythmia patients with marked previous myocardial damage, the dose of RYTHMOL should be increased more gradually during the initial phase of treatment.

    The combination of CYP3A4 inhibition and either CYP2D6 deficiency or CYP2D6 inhibition with the simultaneous administration of propafenone may significantly increase the concentration of propafenone and thereby increase the risk of proarrhythmia and other adverse events. Therefore, avoid simultaneous use of RYTHMOL with both a CYP2D6 inhibitor and a CYP3A4 inhibitor [see Warnings and Precautions (5.4), Drug Interactions (7.1)].

  • Rythmol Sr
    Rythmol Sr (Propafenone Hydrochloride) Capsule, Extended Release [Glaxosmithkline Llc]

    Rythmol Sr

    Rythmol Sr (Propafenone Hydrochloride) Capsule, Extended Release [Glaxosmithkline Llc]

    RYTHMOL SR can be taken with or without food. Do not crush or further divide the contents of the capsule.

    The dose of RYTHMOL SR must be individually titrated on the basis of response and tolerance. Initiate therapy with RYTHMOL SR 225 mg given every 12 hours. Dosage may be increased at a minimum of 5-day intervals to 325 mg given every 12 hours. If additional therapeutic effect is needed, the dose of RYTHMOL SR may be increased to 425 mg given every 12 hours.

    In patients with hepatic impairment or those with significant widening of the QRS complex or second-or third-degree AV block, consider reducing the dose.

    The combination of CYP3A4 inhibition and either CYP2D6 deficiency or CYP2D6 inhibition with the simultaneous administration of propafenone may significantly increase the concentration of propafenone and thereby increase the risk of proarrhythmia and other adverse events. Therefore, avoid simultaneous use of RYTHMOL SR with both a CYP2D6 inhibitor and a CYP3A4 inhibitor [see Warnings and Precautions (5.4), Drug Interactions (7.1)].